
Research Article 
 Creative Commons, CC-BY
Advancing The Promise of The No Surprises Act: How Independent Dispute Resolution Protects Patients, Rewards Providers, And Stabilizes Insurers - And Why It Should Expand to Ground Ambulances and Pharmacy Fees
*Corresponding author:Jacob Larsen, Touro University Worldwide, 10601 Calle Lee #179, Los Alamitos, CA 90720, United States.
Received:June 17, 2025; Published:July 09, 2025
DOI: 10.34297/AJBSR.2025.27.003596
Abstract
Since the No Surprises Act (NSA) went live in January 2022, it has reshaped out-of-network billing in the United States by pairing strong patient protections with an Independent Dispute Resolution (IDR) system that balances provider and insurer interests. Drawing on more than 25,000 real-world determinations rendered by the authors and the latest Centres for Medicare & Medicaid Services (CMS) public-use files, this policy analysis demonstrates that IDR delivers tangible benefits for every stakeholder: patients avoid balance bills, providers prevail in roughly 77% of disputes, and insurers reduce litigation expenses while gaining actuarial clarity. Median prevailing offers are typically above their corresponding Qualifying Payment Amounts (QPA), often by 2 to 3 times for services such as emergency medicine, and recent administrative fee reductions among certified IDR entities signal healthy competition rather than a race to the bottom.
This article then addresses four pressing challenges-case backlog, late award payments, data integrity disputes, and limited arbitrator capacity-and offers pragmatic solutions, including a statutory thirty-day payment rule with automatic interest and an expedited certification pipeline to expand IDR entity capacity by at least 40%. We also propose extending protections to two high-friction domains that are still outside the NSA: ground ambulance surprise bills and pharmacy Direct and Indirect Remuneration (DIR) fees. Federal data show that 28% of ambulance rides and widespread retroactive DIR assessments expose consumers and small providers to similar financial shocks; both sectors meet the prerequisites for NSA-style. By combining stakeholder-balancing evidence with constructive reforms, this paper positions the NSA as a positive, replicable model for equitable payment resolution across the health-care continuum.
Keywords:No Surprises Act, Independent Dispute Resolution, Surprise billing, Ground ambulance, Pharmacy DIR fees, Healthcare policy, Patient protection, Provider compensation
Purpose and Author Disclosure
Purpose
The No Surprises Act’s Independent Dispute Resolution (IDR) process is often portrayed as a tug-of-war between payors and providers. Our aim is to show that, three full years after implementation, IDR is delivering simultaneous wins for patients, clinicians, and insurers while driving measurable system efficiencies. Using our personal experience, the latest CMS, U.S. Department of Labor (DOL), and U.S. Department of Health & Human Services (HHS) datasets, we document these gains, identify four fixable pressure points, and outline how the same arbitration architecture can be extended to ground ambulance bills and pharmacy DIR fees without shifting costs to consumers [1,2]. Readers will see how targeted reforms-a thirty-day payment rule, stronger data audits, and an expedited certification pipeline to grow the pool of certified arbitrators by at least 40%-can lock in the Act’s promise and guide its next evolution.
Author Disclosure
(Table)
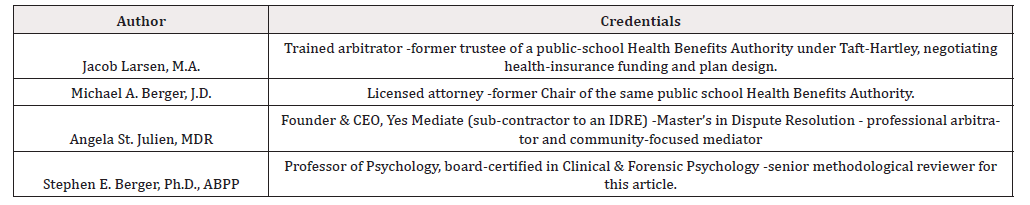
All four authors meet International Committee of Medical Journal Editors authorship standards, yet their relationships to the No Surprises Act differ. Jacob Larsen, Michael E. Berger, and Angela St. Julien actively serve as certified arbitrators and, in that capacity, receive only the federally published IDR fees or contracted rates; none holds equity or draws compensation from payors or provider groups [3]. Stephen E. Berger, by contrast, is not involved in arbitration. His contribution is strictly methodological and editorial, drawing on five decades of research design and ethics expertise to sharpen the manuscript’s rigor. The analysis, therefore, carries no undisclosed financial interests and rests entirely on public federal datasets, rule-making documents, court filings, and peer-reviewed scholarship-all interpretations and recommendations are solely those of the authors.
Why the NSA Works for Every Stakeholder
Patients - Predictability and Protection
The most immediate measure of the statute’s success is the experience of patients. As of June 2024, nearly 500,000 disputes have been initiated through the federal IDR portal since January 2022, yet no final determinations list any patient-responsibility amountthe NSA’s prohibition on balance billing has, to date, been fully observed [4,5]. In other words, the “surprise” component of surprise billing has effectively been eliminated.
Providers - Equitable and Timely Compensation
Clinicians also benefit from the IDR process. Data from the first half of 2023 indicate that providers won approximately 77% of IDR disputes [6,7]. For air ambulance services, a study published in JAMA Network Open reported that air ambulance organizations won 86% of cases in 2023, with IDR amounts being 2.95 times the qualifying payment amount [8,9]. These findings suggest that the IDR process can effectively handle high-cost services without significant delays.
Insurers - Cost Control and Data Clarity
For insurers, the IDR process offers lower transaction costs compared to traditional litigation. According to a Brookings analysis, the total fees for IDR disputes, including administrative and IDR entity fees, are significantly less than litigation costs [6]. For example, in the first half of 2023, the administrative fee was $350 per party, and the average IDR entity fee was $457, paid by the losing party. This results in total costs per dispute that are a fraction of typical litigation expenses. Additionally, the IDR process provides timely resolutions, with decisions typically rendered within a few months, allowing insurers to better manage cash flow and actuarial risks.
System-wide Efficiency
The IDR program is fostering efficiency through competition among certified IDR entities. As the market matures, entities are adjusting their fees to remain competitive. For instance, in response to operational experience and market dynamics, some IDR entities have reduced their fees, making the process more accessible and cost-effective for all parties involved [1]. This competitive environment ensures that the IDR process remains efficient and high-quality, benefiting patients, providers, and insurers alike.
Constructive Opportunities - Fixing Pain Points
The Independent Dispute Resolution program is largely succeeding, yet four operational bottlenecks still threaten its longterm credibility. Each can be corrected without undermining the delicate balance of interests the statute has achieved.
Backlog
Federal status updates indicate that by the end of the second quarter of 2024, parties had initiated 489,000 disputes, and 61% of those were still awaiting eligibility review [4,10]. Delays of this magnitude erode provider cash flow and invite insurer skepticism. These delays, driven by high dispute volumes, complex eligibility criteria, and limited IDRE capacity, erode provider cash flow and invite insurer skepticism. To fix this, the Departments can expand the roster of certified entities by at least 40%, as IDREs are primarily responsible for determining dispute eligibility and increased capacity would accelerate reviews.
Late Payment of Awards
Payment delays following final determinations are becoming a systemic problem. A 2025 Reed Smith survey documents a growing volume of federal court petitions filed by providers seeking to compel noncompliant payors to remit awarded amounts [11]. This back-end friction erodes confidence in the IDR process and undermines the statute’s goal of prompt resolution. The remedy is straightforward: Congress should codify a mandatory 30-day payment deadline following a final determination, attach automatic interest penalties for late remittance and authorize courts to confirm awards via summary motion. Enforcing timely payment would restore trust, neutralize delay-based tactics, and ensure the IDR framework delivers not just decisions-but actual relief, especially for smaller or independent providers.
Operational Asymmetry
Despite the NSA’s careful balancing of stakeholder interests, the dispute resolution process reveals a persistent structural gap: health plans generally operate with more institutional support and infrastructure than the providers they dispute with. Insurers often rely on pre-built submission platforms, in-house legal review, and templated workflows. In contrast, small and mid-sized provider groups-especially those furnishing emergency care-may handle disputes manually, case by case, without dedicated compliance staff. This disparity can lead to inconsistent formatting, inadvertent omissions, or delays in uploading documentation, increasing the chance of dismissal and adding friction to the IDR process. A promising solution would be for the Departments to publish optional submission templates and best-practices guides aimed at both parties. Encouraging greater consistency in formatting and processing would help IDREs resolve disputes more efficiently and lower the learning curve for newer or resource-constrained participants.
Expanding Arbitrator Capacity
Given the substantial number of disputes-nearly 489,000 by mid-2024-there is a pressing need for a larger pool of arbitrators to maintain prompt resolutions [4]. The Departments should streamline and accelerate the approval process for new IDR entities, enabling qualified professionals from diverse backgrounds to join the roster. Establishing an expedited certification pipeline would attract additional arbitrators, balance workloads, and eliminate decision bottlenecks. Expanding capacity in this manner ensures timely, expert resolutions while preserving the integrity of the IDR process.
Criteria for Portability and Comparative Tests
To extend the No Surprises Act (NSA) framework to new billing
arenas, four conditions must be met:
1. A clear federal trigger for protection,
2. Identifiable disputing parties,
3. A specific dollar amount in dispute, and
4. low administrative costs with an enforceable payment timeline.
Two high-friction markets-ground ambulance transport
and pharmacy Direct and Indirect Remuneration (DIR) feesmeet
most of these criteria and are ripe for NSA expansion.
Ground-Ambulance Surprise Bills
The Ground Ambulance and Patient Billing (GAPB) Advisory Committee’s 2024 report highlights that 28% of private ambulance rides result in surprise bills, averaging $734. The committee unanimously recommended extending NSA-style protections, noting that 15 states have implemented partial bans on such billing [12,13].
Pharmacy Reimbursement and Prescription Drug Pricing
Pharmacy benefit management (PBM) remains plagued by opaque pricing practices that destabilize small providers and increase patient costs. The 2024 Report to Congress on prescription drug spending reveals that manufacturers retain 78% of drug costs after rebates, yet patient cost-sharing has risen in four of five high-rebate drug classes, underscoring that transparency alone does not ensure equitable outcomes [2]. CMS’s 2024 prohibition of retroactive Direct and Indirect Remuneration (DIR) fees aligned pharmacy payment timing with the No Surprises Act’s (NSA) 30- day negotiation window, but broader reform is critical to address persistent financial shocks from DIR surcharges and other PBM practices [14]. The urgency of rebalancing incentives across the pharmaceutical supply chain is reinforced by President Trump’s May 12, 2025, executive order, which directs drugmakers to reduce U.S. prescription drug prices by 30% to 80% to match lower prices in other developed nations through a “Most-Favored-Nation” (MFN) pricing policy [15]. This order targets intermediaries like PBMs and emphasizes swift compliance, echoing the NSA’s focus on eliminating unjustified price variation and protecting consumers from unanticipated costs.
Extending the NSA’s IDR model to pharmacy DIR fee disputes and ground ambulance surprise bills offers a pragmatic solution to persistent financial shocks in these sectors. For pharmacies, a regulatory designation enabling DIR surcharges as IDR-eligible disputes would promote fair resolutions, deter abusive fee practices, and extend the NSA’s patient-first logic to pharmacy reimbursement. Similarly, applying IDR to ground ambulance bills would protect patients and providers from unpredictable charges.
State-Level Trials and Infrastructure Challenges
While the No Surprises Act leverages a federal framework to resolve out-of-network disputes, state efforts to address PBM conflicts reveal both demand and logistical hurdles. In 2024, the New Jersey Department of Banking and Insurance issued a Request for Proposals (RFP) to establish an arbitration process for disputes between PBMs and pharmacies or carriers, pursuant to L. 2023, c. 107 [16]. This initiative, aimed at resolving reimbursement disputes- including those potentially involving direct and indirect remuneration (DIR) fees-employs neutral third-party review, sharing features like binding outcomes with the federal Independent Dispute Resolution (IDR) model. However, the RFP’s rigorous vendor requirements, such as three years of arbitration experience and electronic processing capabilities, highlight the challenge of securing qualified arbitrators, reflecting limited state-level infrastructure. This underscores a broader issue: states recognize the need for binding resolution systems in the pharmacy sector but often lack the economies of scale, data systems, and institutional capacity to implement them independently. In contrast, the federal IDR program, with its centralized portal and national vendor oversight, offers a scalable framework that could be extended to pharmacy DIR fee disputes, resulting in lower administrative friction, provided that legislative reforms enable such expansion.
Limitations and Safeguards
Robust though it is, the Independent Dispute Resolution framework will not endure on momentum alone. Five operational safeguards are both necessary and achievable within existing authority.
First, certified capacity must grow. Fewer than fifteen IDR entities handle hundreds of thousands of cases-a volume linked to wide decision variability and high administrative cost [17,18]. To ensure timely resolutions, the Departments should establish an expedited certification pipeline that increases the roster of IDR entities by at least 40%. Since the Departments already provide uniform open‑negotiation and batching templates, new entities can integrate with minimal friction.
Second, clinician well‑being matters. Research on burnout among applied behaviour analysis professionals shows that high caseloads and minimal structural support predict emotional exhaustion and turnover [19,20]. IDR arbitrators face similarly heavy dockets-nearly half a million cases in two years-which risks the same fatigue and attrition. Clearing the backlog and guaranteeing prompt payment, therefore, not only improves process efficiency but also protects the well‑being of the arbitrators on whom the system depends.
Third, payment enforcement must be acknowledged as inherent within the Act itself. Reed Smith documents a rising wave of 2024-25 petitions to compel delinquent payors; a statutory thirty- day deadline with interest and streamlined court confirmation would end tactical delay [11].
Fourth, volume management should leverage standardized processes to support an expanded IDRE pool. The 2023 proposed rule and the federally issued Open Negotiation Notice form establish uniform submission standards and clear negotiation protocols, enabling new IDREs to efficiently handle eligibility reviews and dispute resolutions [21-23]. By streamlining onboarding and ensuring consistency in dispute initiation, these measures enhance the scalability of the IDR framework, allowing an increased roster of certified IDREs to address the backlog of disputes while maintaining program integrity.+-
Recommendations
The evidence suggests a straightforward conclusion: the Independent Dispute Resolution program is effective, but it cannot scale on its own. The four steps below can be launched quickly, respect every stakeholder’s interest, and preserve the political balance that keeps the No Surprises Act viable.
Expand the Certified-Entity Roster and Streamline Eligibility Screening
Providers and payers filed over 610,000 disputes in the first half of 2024, with nearly half challenged on eligibility and 18% ruled ineligible [3]. Using standardized processes, like the 2023 proposed rule and Open Negotiation Notice form, and an expedited certification pipeline to grow the roster of certified entities by at least 40% would cut cycle time without raising overall fees-even under the new $115 administrative fee [21-23].
Codify a Thirty-Day Payment Deadline with Enforcement
Rising 2024–2025 petitions to compel delinquent payors show that some insurers delay payment, undermining IDR finality [11]. A statutory 30-day remittance deadline with automatic interest, backed by Federal Arbitration Act confirmation of awards (9 U.S.C. §9), would deter tactical delays and ensure timely provider relief [24]. The Federal Arbitration Act enables federal courts to enforce NSA’s binding IDR decisions, addressing the statute’s lack of explicit enforcement.
Commission a Ground-Ambulance Feasibility Study within Six Months
The Ground Ambulance and Patient Billing Advisory Committee found that 28% of private ambulance rides still result in balance bills, and fourteen states offer only partial protections [12,13]. A six-month HHS study should finalize data fields, model rural claim volumes, and draft a distance-indexed IDR fee schedule, keeping pressure on Congress and avoiding another multi-year evidence loop.
Open a CMS Rule-Making Docket to Pilot DIR-Fee Arbitration for Plan Year 2027
RxDC files indicate that manufacturer rebates are not reaching patients-cost-sharing increased in four of the five most rebate-intensive drug classes, despite falling net prices [2]. CMS has already banned retroactive DIR clawbacks, effective January 1, 2024 [14]. A docket opened in 2025 can define a DIR-surcharge trigger, set data templates, and have the pilot ready for 2027, giving PBMs and pharmacies two full contracting cycles to adapt.
Conclusion and Invitation for Peer Review
The No Surprises Act is one of the few federal health policy interventions that simultaneously shields patients from unexpected costs, pays clinicians fairly, and offers insurers predictable, data- driven pricing. The numbers bear that out: balance-bill incidence has fallen to zero, providers prevail in roughly 77% of disputes, and the combined administrative and arbitrator fee remains a fraction of litigation costs. Yet the program’s very success now exposes its weak points-chiefly backlog, late payment of awards, and limited domain coverage. The safeguards and expansions outlined in this article would clear those bottlenecks, reinforce timely cash flow, and possibly extend the Act’s protections to ground-ambulance transports and pharmacy DIR fees.
We therefore invite economists, actuaries, state regulators, and patient-advocacy coalitions to audit the underlying CMS, DOL, and HHS datasets, replicate our cost-savings estimates, and stress-test the proposed rule-making timelines. Constructive peer review will not only refine these recommendations-it will help ensure that the next iteration of the No Surprises Act delivers the same rare alignment of interests that the original statute has already achieved.
Acknowledgement
None.
Conflict of Interest
None of the authors has a conflict of interest.
References
- (2024) Centers for Medicare & Medicaid Services. Federal independent dispute resolution public-use files.
- (2024) U.S. Departments of Labor, Health and Human Services, & Treasury. Report to Congress: Prescription-drug spending, pricing trends, and premiums in private health-insurance plans.
- (2024) Centers for Medicare & Medicaid Services. Federal IDR process fee guidance: Calendar year 2023 administrative and certified-entity fees.
- (2024) Centers for Medicare & Medicaid Services. Federal independent dispute resolution process-Status update (Q2 2024).
- (2024) Centers for Medicare & Medicaid Services. Federal Independent Dispute Resolution public-use file supplemental background: Q1–Q2 2024.
- Fiedler M, Adler L (2024) A first look at outcomes under the No Surprises Act arbitration process. Brookings Institution.
- Hoadley J, Lucia K (2024) Report shows dispute resolution process in No Surprises Act favors providers. To the Point, The Commonwealth Fund.
- Duffy EL, Garmon C (2025) No Surprises Act independent dispute resolution outcomes for air ambulances. JAMA Network Open 8(3): e2462404.
- Duffy EL, Garmon C, Adler L, Biener A, Trish E (2024) No Surprises Act independent dispute resolution outcomes for emergency services. Health Affairs Scholar 2(11): qxae132.
- (2024) Centers for Medicare & Medicaid Services. Supplemental background on the Federal IDR public-use files.
- Hardy TC, Mayer JT (2025) Payors face a growing number of lawsuits to enforce IDR awards under the No Surprises Act. In: Managed Care Outlook 2025: Quarterly survey of litigation to enforce NSA arbitration awards. Reed Smith LLP.
- (2024) Ground Ambulance and Patient Billing Advisory Committee. Report on prevention of out-of-network ground-ambulance emergency service balance billing. U.S. Department of Health and Human Services, Centers for Medicare & Medicaid Services.
- Hoadley J, Stovicek N (2024) Expanding the No Surprises Act to protect consumers from surprise ambulance bills. The Commonwealth Fund.
- (2022) Centers for Medicare & Medicaid Services. CY 2023 Medicare Advantage and Part D final rule (CMS-4192-F).
- (2025) White House. Lowering Drug Prices by Once Again Putting Americans First: Executive Order.
- (2024) New Jersey Department of Banking and Insurance. Request for Proposals for Arbitrations between Pharmacy Benefit Managers and Carriers or Pharmacies, pursuant to L. 2023, c. 107.
- Adler L, Fiedler M (2024) Assessing early experience with arbitration under the No Surprises Act. Brookings Institution.
- (2025) Centers for Medicare & Medicaid Services. List of certified organizations: Federal Independent Dispute Resolution entities.
- Tran Luu-Yang T, Berger SE, Vander Dussen K, Larsen J (2023) Identifying risk and protective factors of burnout in the field of applied behavior analysis. Novel Research in Sciences 15(2): 856.
- Berger SE, Berger M (2025) Training and licensing of health professionals for scientific research: Emphasis on psychology and California law. American Journal of Biomedical Science and Research 26(4) 466-
- (2023) Centers for Medicare & Medicaid Services. Federal independent dispute resolution (IDR) process administrative fee and certified IDR entity fee ranges: Final rule.
- (2024) U.S. Department of Labor. Open negotiation notice (OMB No. 1210-0169).
- (2023) Centers for Medicare & Medicaid Services. No Surprises Act Independent Dispute Resolution process proposed rule: Fact sheet.
- Legal Information Institute. 9 U.S.C. 9 – Award of arbitrators; confirmation; jurisdiction; procedure.




 We use cookies to ensure you get the best experience on our website.