
Review Article 
 Creative Commons, CC-BY
Testosterone and Prevention: Effects of Testosterone and Testosterone Treatment on Inflammatory Processes
*Corresponding author:Aksam Yassin, Hamad Medical Corporation, Aisha Al Attiyya Hospital, Andrology & Men’s Health Unit, Qatar.
Received:September 10, 2025; Published:September 17, 2025
DOI: 10.34297/AJBSR.2025.28.003700
Abstract
Keywords:Testosterone; C-reactive protein; Tumor necrosis factor-alpha; Interleukin-6; Interleukin-1 beta; Chronic inflammatory diseases, Crohn’s disease, Ulcerating Colitis
Introduction
The role of testosterone in the pathophysiology of inflammation is of critical clinical importance; however, no universal mechanism( s) has been advanced to explain the complex and interwoven pathways of androgens in the attenuation of the inflammatory processes. Because anti–tumor necrosis factor therapy is the mainstay for the treatment of moderate-to-severe inflammatory bowel disease; including Crohn’s disease and ulcerative colitis, and because testosterone therapy in hypogonadal men with chronic inflammatory conditions reduce tumor necrosis factor-alpha (TNF-_), IL-1_, and IL-6, we suggest that testosterone therapy attenuates the inflammatory process and reduces the burden of disease by mechanisms inhibiting inflammatory cytokine expression and function. Mechanistically, androgens regulate the expression and function of inflammatory cytokines, including TNF-_, IL-1_, IL-6, and CRP (C-reactive protein). Here, we suggest that testosterone regulates multiple and overlapping cellular and molecular pathways involv ing a host of immune cells and biochemical factors that converge to contribute to attenuation of the inflammatory process.
Review
Testosterone and inflammation are closely linked, and research has shown their relationship is more complex than just “higher testosterone= less inflammation.” Here’s a structured overview:
Testosterone as an Immune Modulator
a. Testosterone is considered immunosuppressive compared to
estrogens.
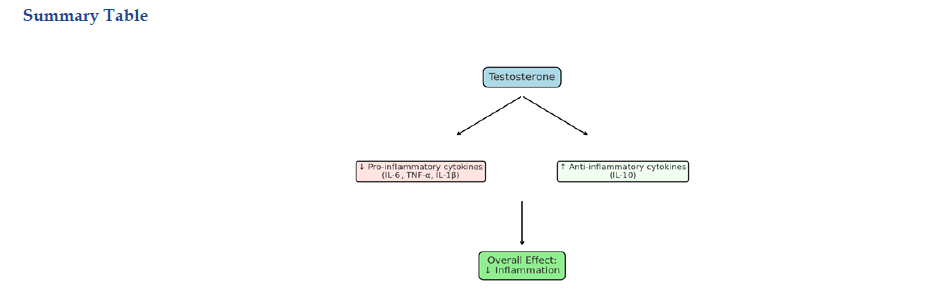
b. It can downregulate pro-inflammatory cytokines such as IL-6,
TNF-α, and IL-1β.
c. It can also increase anti-inflammatory cytokines like IL-10.
This partly explains why autoimmune diseases (which involve overactive immunity) are more common in women than men [1].
Low Testosterone and Inflammation
a. Men with low testosterone (hypogonadism) often show higher
levels of C-Reactive Protein (CRP), IL-6, and TNF-α.
b. Chronic low testosterone is associated with metabolic syndrome,
obesity, diabetes, and cardiovascular disease-all conditions
linked to systemic inflammation.
Testosterone Replacement Therapy (TTH) and Inflammation
a. Some studies suggest TTH can reduce markers of inflammation
(e.g., lowering CRP, IL-6).
b. Other studies show mixed results, depending on dose, patient
health, and underlying conditions.
c. In men with obesity or metabolic syndrome, TTH often improves
inflammatory profiles.
Mechanisms Behind Testosterone’s Anti-Inflammatory Effects
a. Androgen Receptor (AR) signaling in immune cells can suppress
inflammatory gene expression.
b. Testosterone inhibits NF-κB, a major transcription factor driving
inflammation.
c. Indirect effect: testosterone increases muscle mass, insulin
sensitivity, and fat distribution, which themselves reduce
chronic inflammation.
Clinical Relevance
a. Chronic low testosterone →more inflammation →higher risk
of heart disease, type 2 diabetes, prostate inflammations etc.
b. TTH →may reduce inflammation in hypogonadal men but
should be carefully monitored.
c. In acute illness, testosterone sometimes decreases temporarily
(protective adaptation)
Scientific Studies & Reviews
1) Malkin, et al., [2] (hypogonadal men; randomized crossover
study)
2) Testosterone replacement reduced TNF-α (≈–3.1 vs +1.3pg/
mL; P =0.01), tended to lower IL-1β (P ≈0.08), and raised IL-10
(an anti-inflammatory cytokine; P=0.01) compared to placebo.
3) Androgen therapy in older type 2 diabetic men (2006) TTH
(150mg testosterone enanthate biweekly for a year) markedly
suppressed spontaneous ex vivo production of IL-1β, IL-6,
TNF-α by antigen-presenting cells. Notably, these anti-inflammatory
effects persisted even 3 months after TTH withdrawal
[3].
4) Lifespan and cytokine relationships in older men in older
men, low testosterone levels correlated with pro-inflammatory
states. Supplementation appeared to reduce inflammatory
markers like sIL-6R, suggesting an inverse relationship between
T and inflammation [4,5].
5) Young men and systemic inflammation
A cross-sectional study found that young men with low testosterone
had significantly higher levels of TNF- α, MIP1 α, and MIP1β,
indicating that testosterone deficiency can be associated with lowgrade
systemic inflammation even in younger populations,
6) Adiposity-linked hypogonadism
In overweight men, increased CRP and IL-6 levels (markers of
inflammation) were associated with lower testosterone, independent
of other hormonal changes.
7) Population Data from US Males
A large cross-sectional study found inverse associations between
both total and free testosterone and CRP levels-higher T generally
meant lower CRP, supporting anti-inflammatory effects
8) Mechanistic insights: NF-κB inhibition
Reviews highlight that testosterone can suppress multiple
pro-inflammatory cytokines (TNF-α, IL-6, IFN-γ, IL-2), likely via
pathways such as inhibiting NF-κB signaling.
9) Wikipedia summary
An overview emphasizes that testosterone deficiency aligns
with higher inflammatory biomarkers (CRP, IL-1β, IL-6, TNF-α) and
that TTH has been shown to significantly reduce these markers
10) Cardiovascular implications
Low testosterone is linked to increased risk of atherosclerosis
in part by promoting a pro-inflammatory environment-T helps reduce
TNF-α, IL-1β, IL-6 (Table 1).
Context Observation
a. Hypogonadal men +TTH ↓TNF- α, IL-1β; ↑ IL-10; anti-inflammatory
shift
b. Older diabetic men Suppressed APC-related cytokine production
(IL-1β, IL-6, TNF-α) →persists post-withdrawal [6].
c. Aging men & general population Inverse correlation: higher T,
lower inflammatory markers
d. Young healthy men Low T linked with elevated TNF-α, MIP1
α/β
e. Obesity-associated hypogonadism Elevated CRP, IL-6 with
lower T
Mechanistic insights Testosterone suppresses cytokines via NF-
κB pathway
Thoughts or Facts
a. Strong evidence supports that testosterone has anti-inflammatory
effects, particularly by lowering pro-inflammatory cytokines
and raising anti-inflammatory ones.
b. This relationship is observed across ages, health statuses, and
intervention types-from cross-sectional studies to controlled
trials.
c. Mechanistically, pathways like NF-κB inhibition are key mediators.
d. These insights have significant implications for conditions like
cardiovascular disease, metabolic syndrome, and age-related
inflammation [7].
Testosterone May Ease Inflammatory Bowel Disease in Hypogonadal Men
Series of case reports in our cohort showed that after normalization of Testosterone (T) levels improved Crohn’s disease in hypogonadal men in a prospective, observational registry study and we reported this at the Men’s Health World Congress 2015 [8]. The study included 71 hypogonadal men with Crohn’s disease and two with Ulcerating colitis. The patients received treatment with parenteral testosterone undecanoate on day 1, after six weeks, and every 12 weeks thereafter for up to 75 months. Twelve hypogonadal men of similar age with Crohn’s disease who did not receive testosterone served as an untreated control group. T levels at baseline were 9.37 and 10.75nmol/L in the T group and control group, respectively. During treatment, T increased to 15.72nmol/L and declined slightly in the control group. The Crohn’s Disease Activity Index improved from 231 to 75 in the testosterone-treated group but worsened from 196 to 210 in the control arm (scores below and above 150 are considered to reflect inactive and active disease, respectively). High-sensitivity C-reactive protein levels, a marker of systemic inflammation, decreased in the testosterone-treated men but increased in the control group. The Aging Males’ Symptoms Scale (AMS) score improved in the testosterone-treated men but remained unchanged in the control group. We concluded “The mechanism of this improvement may be through anti-inflammatory and immunosuppressive effects of testosterone,” [9].
The Connection Between Testosterone and Inflammatory Diseases
Understanding the connection between testosterone and inflammatory diseases is crucial for developing effective treatments and managing symptoms. This article delves into how testosterone levels influence inflammatory diseases, supported by scientific studies and clinical evidence, and explores the broader implications for patient care.
a. Inflammatory diseases are linked with low testosterone levels,
suggesting a hormonal component in its pathogenesis.
b. Scientific studies indicate that testosterone therapy can significantly
improve inflammatory diseases symptoms and reduce
inflammation.
c. Hormonal fluctuations, particularly in testosterone, correlate
with the severity of inflammatory diseases symptoms.
d. Testosterone replacement therapy has shown sustained improvements
in inflammatory diseases conditions in hypogonadal
men.
e. Further research is needed to fully understand the molecular
pathways and potential for new treatment approaches involving
testosterone.
Exploring the Link Between Testosterone and Inflammatory Diseases
Overview of Inflammatory Diseases and Testosterone
Inflammatory diseases, a prevalent inflammatory skin condition, may have a deeper connection with hormonal balances than previously understood. Testosterone, a vital sex hormone, has been linked to the pathogenesis of inflammatory diseases. This connection suggests that hormonal imbalances could play a significant role in the onset and severity of inflammatory diseases.
Scientific Studies Supporting the Connection
Recent scientific endeavors have shed light on how testosterone levels impact inflammatory diseases. Studies indicate that low testosterone in men could exacerbate inflammatory diseases symptoms, leading to more severe skin manifestations. This correlation has been supported by clinical trials where testosterone therapy led to improvements in inflammatory diseases conditions [10].
Long-Term Effects of Testosterone on Inflammatory Diseases
Understanding the long-term effects of testosterone on inflammatory diseases is crucial for developing effective treatments. Continuous research has shown that testosterone therapy not only helps in reducing inflammatory diseases severity but also maintains these benefits over time [11]. This sustained improvement highlights the potential of hormone-based therapies in managing inflammatory diseases effectively.
The Role of Hormones in Inflammatory Diseases Pathogenesis
Overview of Inflammatory Diseases and Testosterone
Understanding the intricate dance between hormones and inflammatory diseases begins with recognizing the roles of testosterone and other sex hormones. Testosterone imbalance has been identified as a significant factor in the etiology of inflammatory diseases, particularly in males. This connection suggests that hormonal therapies might be tailored to manage inflammatory diseases severity effectively.
Scientific Studies Supporting the Connection
Recent studies have highlighted the potential role of hormones in the pathogenesis of inflammatory diseases. For instance, the 2D:4D digit ratio, an indicator of prenatal sex hormone balance, has been linked to inflammatory diseases in several studies. This finding underscores the importance of hormonal balance in the development and management of inflammatory diseases.
Long-Term Effects of Testosterone on Inflammatory Diseases
Long-term hormonal fluctuations can significantly impact inflammatory diseases symptoms. Lower testosterone levels in men have been associated with increased inflammatory diseases severity. Conversely, higher testosterone levels tend to correlate with fewer symptoms and flares. This observation supports the potential for testosterone replacement therapy as a management strategy for inflammatory diseases in men experiencing hypogonadism.
Clinical Evidence of Testosterone Therapy on Inflammatory Diseases
Case Studies and Clinical Trials
In exploring the therapeutic potential of testosterone in inflammatory diseases management, several case studies and clinical trials have provided insightful data. For instance, a study by Saad, et al. [12] highlighted significant improvements in the Inflammatory diseases Area and Severity Index (PASI) and Physician Global Assessment for Inflammatory diseases scores among hypogonadal men undergoing testosterone therapy. These benefits were not only considerable but also sustained over time, suggesting a long-term efficacy of this treatment approach.
Improvements in Inflammatory Diseases Symptoms
Testosterone therapy has shown promising results in reducing the severity and area of inflammatory diseases lesions. This is particularly evident in the reduction of C-reactive protein levels, an indicator of inflammation, which significantly declined upon treatment. Such findings underscore the potential of testosterone to attenuate inflammatory responses in inflammatory diseases, akin to its effects in other chronic inflammatory conditions.
Sustainability of Treatment Effects
The long-term benefits of testosterone therapy in inflammatory diseases management are noteworthy. Continuous improvements in inflammatory diseases symptoms and overall skin health over extended periods highlight the sustainability of testosterone therapy effects. This enduring impact encourages further investigation into testosterone as a viable long-term treatment option for inflammatory diseases.
Understanding Hormonal Fluctuations and Inflammatory Diseases Symptoms
Effects of Low Testosterone in Men
You may have noticed that your inflammatory diseases symptoms fluctuate with changes in your hormone levels. Particularly, low testosterone in men has been linked to an increase in the severity of inflammatory diseases. This is because testosterone can modulate the immune system and influence skin inflammation. Managing your hormone levels could be a key strategy in controlling inflammatory diseases flare-ups.
Correlation with Inflammatory Diseases Severity
The severity of inflammatory diseases can indeed correlate with hormonal changes. Studies suggest that during periods when hormones such as estrogen in women and testosterone in men are low, inflammatory diseases symptoms become more pronounced. Conversely, higher levels of these hormones are associated with reduced symptoms. This pattern highlights the potential benefits of hormone therapy in managing inflammatory diseases.
Testosterone Replacement Therapy Outcomes
Considering Testosterone Replacement Therapy (TTH) might
be a viable option for men experiencing worsened inflammatory
diseases symptoms due to low testosterone levels. Here are some
outcomes you might expect from TTH:
a) Improvement in skin condition: Many patients report a reduction
in inflammatory diseases severity.
b) Regulation of immune response: TTH can help modulate the
immune system, potentially reducing inflammatory disease
flare-ups.
c) Enhanced overall well-being: Besides improving inflammatory
diseases, TTH can also boost energy levels and mood.
d) Regulate metabolism of fats and its distribution
e) Preventive role or favourable effects on Prostate, LUTS, Liver,
kidney, Sugar metabolism and blood formation.
It is crucial to consult with a healthcare provider to understand the benefits and risks associated with testosterone replacement therapy and its impact on your inflammatory diseases.
Hormonal Interactions During Different Life Stages
Testosterone Variations
As you navigate through different stages of life, your body experiences significant hormonal changes that can influence the severity and frequency of inflammatory diseases symptoms. Testosterone levels fluctuate naturally with age, and these variations can be particularly impactful.
Inflammatory Diseases Flare-ups and Hormone Levels
Understanding how hormone levels correlate with inflammatory diseases flare-ups is crucial. Generally, higher levels of testosterone in men tend to be associated with fewer inflammatory diseases symptoms. Conversely, lower levels can lead to more frequent and severe flare-ups.
Investigating the Molecular Pathways in Inflammatory Diseases and Testosterone Deficiency
Common Pathways with Other Diseases
In your quest to understand the intricate relationship between inflammatory diseases and testosterone deficiency, it is crucial to recognize the common molecular pathways these conditions share with other diseases. For instance, both conditions exhibit significant inflammatory responses like those seen in atherosclerosis [13]. This overlap suggests potential targets for therapeutic intervention that could address multiple conditions simultaneously.
Role of Inflammatory Markers
The role of inflammatory markers in inflammatory diseases and testosterone deficiency cannot be overstated. Elevated levels of C-reactive protein and specific cytokines, such as IL-17A, are commonly observed in inflammatory diseases patients. These markers not only indicate the presence of inflammation but also help in assessing the severity of the condition. Understanding these markers can guide the development of targeted therapies that reduce inflammation and alleviate symptoms.
Potential for New Treatment Approaches
Exploring new treatment approaches for inflammatory diseases and testosterone deficiency involves a deep dive into their molecular interactions. Recent studies suggest that testosterone therapy may not only improve inflammatory diseases symptoms but also modulate the immune response, leading to sustained improvements. This opens up exciting possibilities for treatments that could offer long-term relief to patients suffering from both conditions.
Implications of Testosterone Inflammatory Diseases Research for Clinical Practice as Guidelines for Managing Low Testosterone and Inflammatory Diseases
You may find it crucial to integrate the latest research findings
into your clinical practice. Managing low testosterone in conjunction
with inflammatory diseases requires a nuanced approach. Consider
the following steps:
1) Assess testosterone levels routinely in psoriatic patients.
2) Evaluate the need for Testosterone Replacement Therapy
(TTH).
3) Monitor the patient’s response to TTH and adjust treatment
plans accordingly [14,15].
Patient Outcomes and Quality of Life
Improving patient outcomes and enhancing quality of life are paramount. Research indicates that testosterone therapy can significantly alleviate inflammatory diseases symptoms and reduce inflammation markers like C-reactive protein. This suggests a dual benefit of managing hormonal levels and controlling psoriatic symptoms, potentially leading to a higher quality of life for patients.
Future Directions in Treatment and Research
The field of inflammatory diseases and testosterone research is ripe for exploration. Future studies should focus on long-term effects of testosterone therapy and its implications on inflammatory diseases pathogenesis. This could pave the way for innovative treatment strategies that incorporate hormonal therapy as a standard approach for managing inflammatory diseases in hypogonadal men.
Research Gaps and Future Studies
The complex relationship between testosterone and inflammatory diseases during different life stages is still not fully understood. There are significant gaps in research, particularly in how hormonal treatments can be effectively integrated into inflammatory diseases management. Future studies will be essential in filling these gaps and providing more targeted treatments.
Conclusion
The connection between testosterone and inflammatory diseases is a complex interplay of hormonal imbalances and inflammatory processes. Research has consistently shown that low testosterone levels are associated with increased severity of inflammations and that testosterone replacement therapy can significantly improve the symptoms in men with testosterone deficiency. However, the exact mechanisms by which testosterone influences inflammation in certain diseases such as inflammatory diseases or colitis … remain not fully understood, and further studies are needed to explore this relationship in depth. Understanding these dynamics is crucial for developing more effective treatments and management strategies for patients suffering from both conditions.
Acknowledgements
None.
Conflict of Interest
None.
References
- Jimenez Balderas FJ, Tapia Serrano R, Fonseca ME, Arellano J, Beltran A, et al. (2001) High frequency of association of rheumatic/autoimmune diseases and untreated male hypogonadism with severe testicular dysfunction. Arthritis Res 3(6): 362-367.
- Malkin CJ, Pugh PJ, Jones RD, Kapoor D, Channer KS, et al. (2004) The effect of testosterone replacement on endogenous inflammatory cytokines and lipid profiles in hypogonadal men. J Clin Endocrinol Metab 89(7): 3313-3318.
- Yassin A, Abdallah H, Kamkoum H, Alzubaidi RT, Albudairat A (2025) Intramuscular Testosterone and the Gel in the Current Treatment Era. Biomed J Sci & Tech Res 61(4): 53877-53882.
- Nakhai Pour HR, Grobbee DE, Emmelot Vonk MH, Bots ML, Verhaar HJ, et al. (2007) Oral testosterone supplementation and chronic low-grade inflammation in elderly men: A 26-week randomized, placebo-controlled trial. Am Heart J 154(6): 1228.
- Yassin A, Kamkoum H, Alzubaidi RT (2025) Is There a Need for Testosterone Therapy in Older Men? J Advances Med Sci 2: 1-3.
- Yassin A, Kamkoum H, Alzubaidi RT, Abdallah H, Assad O (2025) How Long Should We Treat with Testosterone: Stopping Testosterone Therapy (TTh) Wat is Next? Effects of Withdrawal and resumption of TTh. Ann Rev Resear 12: 555843.
- Yassin A, Albaba B, Kamkoum H, Alzubaidi RT, Al Qudimat AR (2025) Testosterone Prevention Role in Men’s Health: Cardiovascular Dieseases. Cardiol Res Cardio vasc Med 10: 280.
- Yassin A, Kamkoum H, Alzubaidi RT, Ansari AA (2025) Testosterone Prevention Role in Men’s Health: Diabetes Mellitus. J Diabetes Treat 10: 10141.
- Yassin A, Alzubaidi RT, Kamkoum H, Akkad MSE, Mahdi (2025) Effect of Testosterone Therapy (TTh) on Liver Function and Steatosis. Gastroint Hepatol Dig Dis 8(1): 1-8.
- Gordon C, Wallace DJ, Shinada S, Kalunian KC, Forbess L, et al. (2008) Testosterone patches in the management of patients with mild/moderate systemic lupus erythematosus. Rheumatology 47(3): 334-338.
- Yassin A, Alzubaidi RT, Kamkoum H, Alzubaidi RT, Ramadan A (2025) Recent Update on Advancements in Testosterone Therapy (TTh). J Urol Ren Dis 10: 1413.
- Nasser M, Haider A, Saad F, Kurtz W, Doros G, et al. (2015) Testosterone therapy in men with Crohn’s disease improves the clinical course of the disease: Data from long-term observational registry study. Horm Mol Biol Clin Investig 22(3): 111-117.
- Yang YM, Lv XY, Huang WD, Xu ZR, Wu LJ (2005) Study of androgen and atherosclerosis in old-age male. J Zhejiang Univ Sci B 6(9): 931-935.
- Hall GM, Larbre JP, Spector TD, Perry LA, Da Silva JA (1996) A randomized trial of testosterone therapy in males with rheumatoid arthritis. Br J Rheumatol 35(6): 568-573.
- Yassin A, Alzubaidi RT, Kamkoum H, Albudairat A, Abdallah H, et al. (2025) Testosterone and Prevention: Effects on Renal Function. J Urol Ren Dis 09: 1427.




 We use cookies to ensure you get the best experience on our website.