
Research Article 
 Creative Commons, CC-BY
The Av Node-Fulcrum Unit. A Quantum Approach to the Cardiac Cycle
*Corresponding author:Jorge Carlos Trainini, Perón Hospital, National University of Avellaneda, Argentina.
Received:September 28, 2026; Published:October 09, 2026
DOI: 10.34297/AJBSR.2026.32.004166
Abstract
Objective: In the present investigation, the anatomical and histological relationship of the Cardiac Fulcrum with the atrioventricular node in hearts of the human, bovine, porcine and anuran species was analyzed, as well as the possible functionality between both structures and the actions derived from said electromechanical unit.
Material and methods: The methods used in this research to explain consisted of:
1) The use of 96 hearts from a morgue, slaughterhouse and breeding grounds: a) 17 human hearts (three at 8, 16, and 23 weeks of gestation, respectively; four infants at 30 days, 36 days, 10 weeks, and 27 weeks; one 4-year-old child; one 10-year-old child; and eight adults with an average weight of 300 g); b) 59 two-year-old bovine hearts weighing between 1300 and 1900 g (average 1650 g); c) 10 porcine hearts (400 g); 10 de anuros (Rhinella arenarum)
2) Histological and histochemical analysis of the anatomical samples.
3) Immunostaining technique for neurofilaments.
4) The endo- and epicardial electrical activation of the left ventricle was studied in 5 humans using three-dimensional electroanatomical mapping.
Results: We observed that in all the species studied (human, bovine, and porcine), the fulcrum has a central area and two poles. It is in close contact with the atrioventricular node. The fulcrum and the atrioventricular node regulate and modulate the body’s afferent information before converting it into the depolarization wave.
Conclusion: During this investigation, in both human and other species’ hearts, histological analysis revealed that the fulcrum (the beginning and end of the continuous myocardium) is adjacent to the AV node, defining a space rich in plexuses with interconnected neurofilaments between both structures. The structural relationship between myocardial stimulation and its mechanical product was analyzed, based on the assumption that this electromechanical unit is undergoing a continuous process of self-organization in which time plays a fundamental role as a fourth dimension added to the three spatial dimensions. The mechanical consequence of the initiation of stimulation in the anatomical and functional unit between the AV node and the cardiac fulcrum, and the continuity of myocardial activation up to the anisotropic zone at the contiguity between the descending and ascending segments, is what generates myocardial torsion through the sequential opposition of movements. Each heartbeat is then a result of a reading of fluctuations in an external and internal environment, which enters through the autonomic system to the AV node in sync with the Fulcrum that generates rhythmic feedback with coupling and decoupling similar to a self-organizing process.
Keywords:Cardiac fulcrum - AV node - Self-organizing system
Introduction
Addressing the organizational unity of the heart through an interconnected approach that integrates current physics and science in its entirety with biology is a crucial, yet complex, step, given the positivist and newtonian tendencies still prevalent in medical knowledge. This approach is not without the “heretical” risks with which traditional medicine often categorizes such initiatives. We know that when a science confronts unresolved problems, it often faces the irreducible. To prevent this knowledge from falling into disrepute, this research has advanced the understanding of cardiac function by incorporating current science based on quantum physics while remaining grounded in the epistemology of scientific reasoning. In this respect, the 20th century has been comparable to the 17th in terms of modern science. This strategy is not a simple step, but it is the one that can bring us closer to medical science evolving toward horizons being explored by other disciplines.
When beginning an investigation, it is necessary to have a certain orientation regarding what should be analyzed. A shift in the research concept also occurs when the problem is examined from a different angle, from a new perspective on the reality of the problem. Peter Medawar stated: “Scientific research begins with a possible world or a fragment of it” [1]. Therefore, imagination is only a narrow margin in science, where there must be a confrontation between what could be and what is, between the possible and the real. Scientific progress is usually achieved by unifying concepts that were previously separate, generally because they arise from different disciplines. For example, the unification of thermodynamics and mechanics through statistical mechanics. This alchemy also occurs between optics and electromagnetism, thanks to Maxwell’s theory of magnetic fields, and through chemistry and atomic physics, which are unified in quantum mechanics [2]. If there is no convergence between different disciplines, the increase in entropy tends to hinder scientific development. The information transmitted thus becomes the cornerstone of the evolution of the systems.
We must consider that interpretations that differ from the cultural reality we experience imply an intellectual debate, which, if conducted honestly, leads to progress in knowledge. In the last century, quantum physics has blurred the boundary between observer and observed, making the observation of the world far less objective. Another advance has been the understanding, through the observation of living beings, that there is an opposition between the mechanistic interpretation and the properties that determine their behavior. In this regard, information theory introduced the concept of a program to describe the information contained within an organism.
We have reached this point in the investigation after an extensive exploration of the reality of the helical heart [3,4], which allowed us to understand the following absolutely correlated topics: phylogenetic aspects of the circulatory system; spatial anatomical location of the cardiac chambers; the cardiac system; the continuous myocardium; architecture of the cardiac apex; why is the heart helical?; the twists of the myocardium; the Cardiac Fulcrum: support of the myocardium; anatomical-physiological relationship between the Cardiac Fulcrum and the AV Node; the friction mechanism in cardiac movements: function of hyaluronic acid; cardiac modeling; propagation of the stimulus and torsion of the heart; interpretation of myocardial activation in relation to the Cardiac Fulcrum and the torsion mechanism; mechanical analysis of diastolic filling; electrophysiological research on cardiac suction; negative intraventricular pressure and suction mechanism: clinical and experimental research; biventricular complementarity; contributions of the helical heart organization to heart failure with preserved ejection fraction; intraventricular vortex.
Only after investigating these topics did, we find that implexion (from the Greek implexus), that is, the entanglement between the anatomy and physiology of the heart and quantum physics, was possible without violating the principles governing biological epismetology in research. In view of the structure found in the continuous myocardium with its helical conformation (Figure 1), the following questions arose, some quite unsettling: Does the relationship between the cardiac fulcrum and the AV node constitute an electromechanical unit open to stimuli from outside the organism? Why does the myocardium originate and terminate at the same point, the cardiac fulcrum, after a double-helix path? Are we witnessing, with this myocardial anatomy, a self-organizing process with the accumulation of negentropic internal information? Does this electromechanical unit behave as an attractor of the cardiac stimulus based on the circular nature of the myocardium, unique in myology? Does the myocardium have a fourth dimension, time? Does myocardial activation combined with time constitute an inseparable activation-time equation?
In order to remain within the bounds of scientific reasoning, we have sought answers to the questions posed, focusing on the concept that the study of the heart’s properties would inevitably lead to a better understanding of its function. In this research, we analyzed the anatomical and histological relationship between the cardiac fulcrum and the atrioventricular node in human, bovine, porcine, and anuran hearts, as well as the possible functionality between these two structures and the actions derived from this electromechanical unit- a situation we will investigate in detail given its importance (Figure 2).
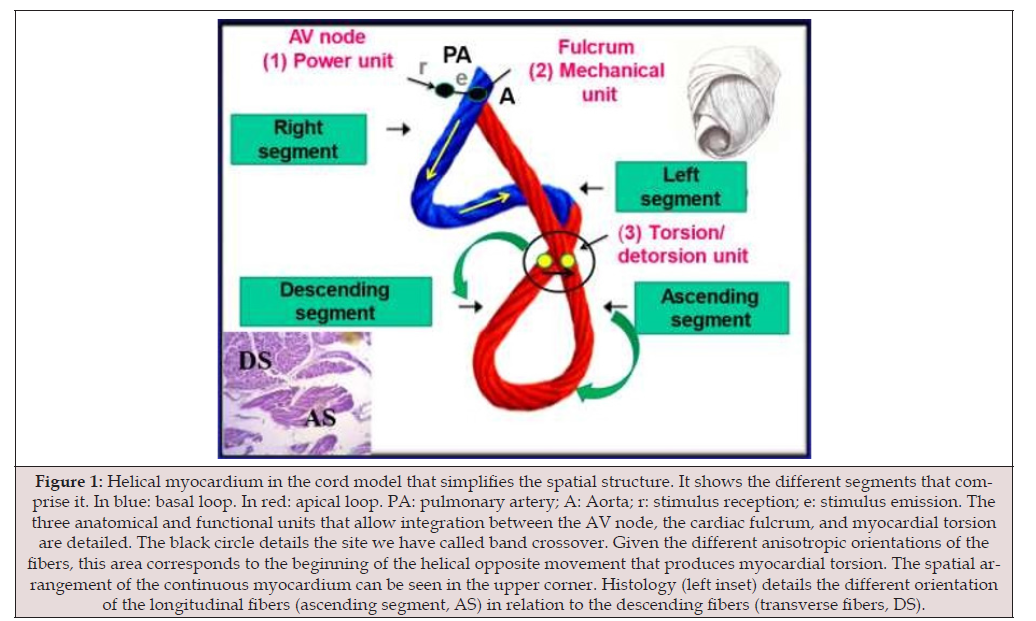
Figure 1:Helical myocardium in the cord model that simplifies the spatial structure. It shows the different segments that comprise it. In blue: basal loop. In red: apical loop. PA: pulmonary artery; A: Aorta; r: stimulus reception; e: stimulus emission. The three anatomical and functional units that allow integration between the AV node, the cardiac fulcrum, and myocardial torsion are detailed. The black circle details the site we have called band crossover. Given the different anisotropic orientations of the fibers, this area corresponds to the beginning of the helical opposite movement that produces myocardial torsion. The spatial arrangement of the continuous myocardium can be seen in the upper corner. Histology (left inset) details the different orientation of the longitudinal fibers (ascending segment, AS) in relation to the descending fibers (transverse fibers, DS).
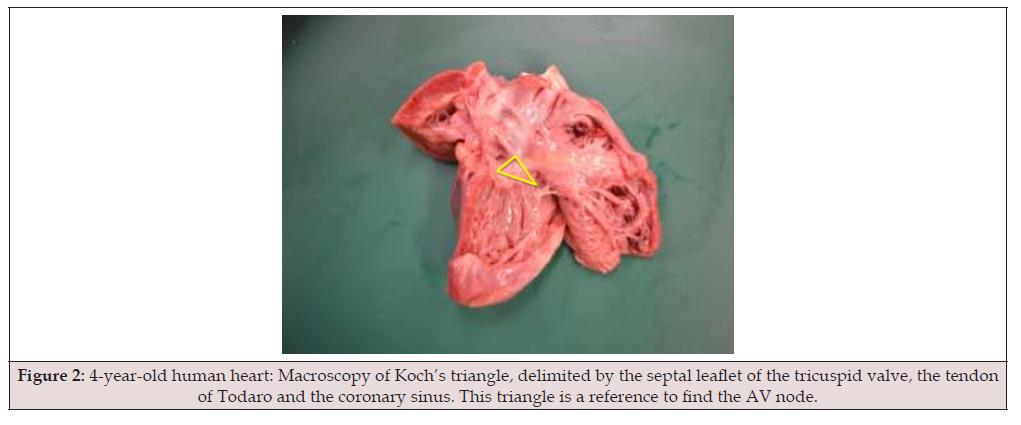
Figure 2:4-year-old human heart: Macroscopy of Koch’s triangle, delimited by the septal leaflet of the tricuspid valve, the tendon of Todaro and the coronary sinus. This triangle is a reference to find the AV node.
The fulcrum [3,4], located at the atrioventricular junction at the insertion of the interventricular septum, below the aorta and pulmonary artery, is adjacent to the AV node of Aschoff-Tawara, which lies to its right (Figures 3-6). The AV node is located at the atrioventricular junction, at the base of the muscular septum, below the origin of the great vessels, adjacent to the cardiac fulcrum, situated between it and the insertion of the septal leaflet of the tricuspid valve. It constitutes a cluster of cells (specialized myocytes) that R.F. Rushmer defines as a spherical or bulbous end composed of bundles of fibers [5-7] for the purpose of transmitting electrical impulses to the myocardial mass. Continuing along its length, it transforms subtly into the bundle of His, which is short in length, sometimes even nonexistent. In humans it measures approximately 5 mm in length, 3 mm in width and 1 mm in thickness and is irrigated by a branch of the coronary arteries, generally coming from the right in 90% of cases and from the circumflex in the remaining minority [8,9].
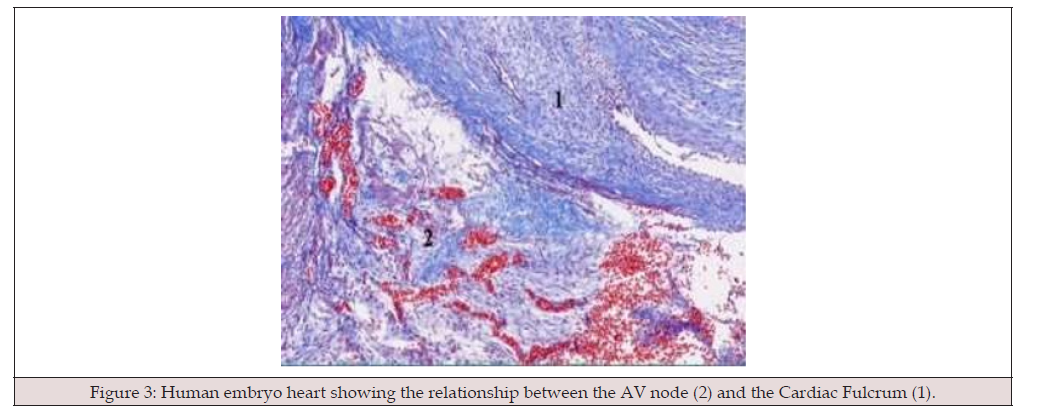
Figure 3:Human embryo heart showing the relationship between the AV node (2) and the Cardiac Fulcrum (1).
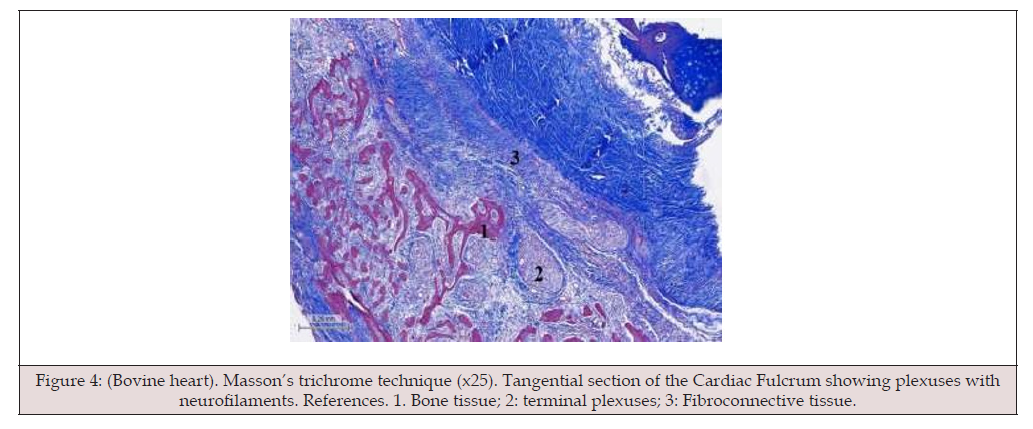
Figure 4:(Bovine heart). Masson’s trichrome technique (x25). Tangential section of the Cardiac Fulcrum showing plexuses with neurofilaments. References. 1. Bone tissue; 2: terminal plexuses; 3: Fibroconnective tissue.
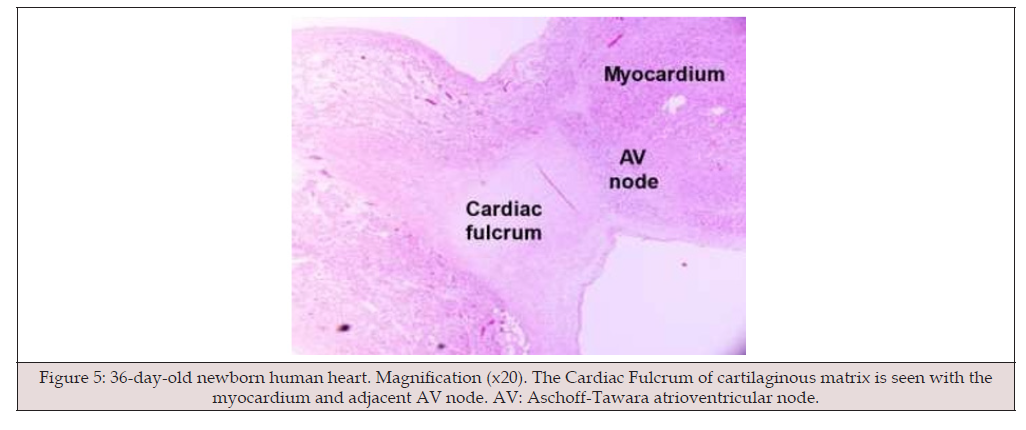
Figure 5:36-day-old newborn human heart. Magnification (x20). The Cardiac Fulcrum of cartilaginous matrix is seen with the myocardium and adjacent AV node. AV: Aschoff-Tawara atrioventricular node.
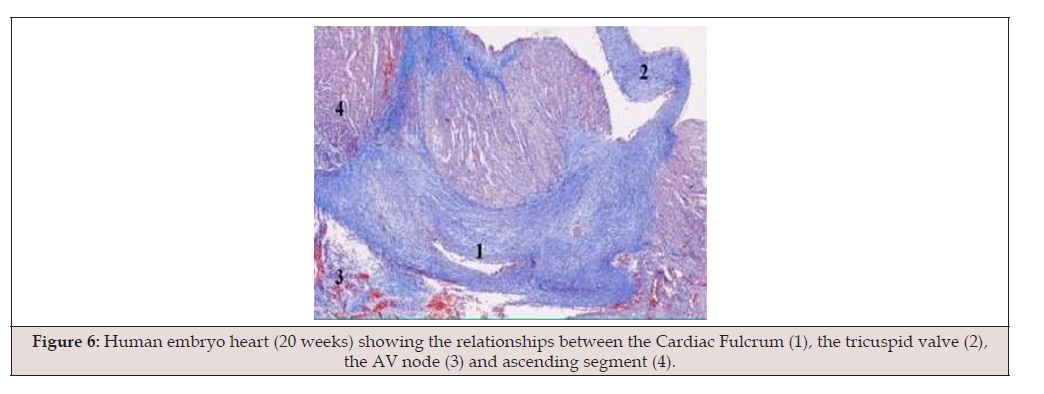
Figure 6:Human embryo heart (20 weeks) showing the relationships between the Cardiac Fulcrum (1), the tricuspid valve (2), the AV node (3) and ascending segment (4).
We must point out that when we encounter new, not yet fully resolved concepts, we leave them within the realm of hypothesis. In short, we believe this approach can help us advance our understanding of cardiac physiology and its therapeutic possibilities, given that living systems must be understood as open systems subject to a constant flow of energy, matter, and information.
Material and Methods
In this study, 96 hearts were used, obtained from the morgue,
slaughterhouses and breeding grounds:
a) 59 two-year-old bovine hearts weighing between 1300 and
1900 g (average 1650 g);
b) 17 human hearts (three at 8, 16, and 23 weeks of gestation,
respectively; four infants at 30 days, 36 days, 10 weeks, and 27
weeks of age; one 4-year-old child; one 10-year-old child; and
eight adults with an average weight of 300 g);
c) 10 porcine hearts (400 g);
d) 10 anuran hearts (Rhinella arenarum).
Anatomical, histological, and histochemical studies were performed. The hearts were fixed in 10% buffered formalin. Histology was performed using hematoxylin and eosin staining, Masson’s trichrome staining, and four-micron sections; 10% formalin was used as buffer. Immunostaining (S100 neurofilaments) was also performed [10]. Endocardial and epicardial electrical activation of the left ventricle was studied in five humans using three-dimensional electro anatomical mapping.
The single, continuous, helical myocardium was unfolded by anatomical dissection according to techniques published in our previous work (Figure 7) [11,12]. A fundamental concept is at the beginning of the unfolding process, since any attempt to disregard the axes along which the myocardium folds helically during dissection will result in a rupture of the cardiac mass. The junction between the origin and termination of the cardiac muscle at the Cardiac Fulcrum constitutes a meeting point between the right and ascending segments, the origin and termination of the myocardium. Thus, both ends are located in the same place, with the origin of the myocardial fibers in a plane anterior to their termination. Samples were taken from the AV node and the His bundle in Koch’s triangle (Figure 2).
Results
We attempt to explain cardiac function according to its helical spatial structure, rather than simply reiterating knowledge based on its apparent composition as a solid, uniform organ. The myocardium is actually composed of a single, continuous longitudinal muscle folded upon itself to form a double helix that delimits the two ventricular chambers (Figures 1, Figure 7). From a genetic perspective, the structure, through its one-dimensional form, determines two-dimensional cellular production, which then transitions to three-dimensionality in organs, acquiring a fourdimensional behavior. This extra dimension can be interpreted as time (Einstein’s spacetime), which will be duly explained, as there is a possible horizon defined by time in each cardiac cycle. The evolution of a dynamic system, such as cardiac activity, implies giving significance to the time of its cycle. In its dynamics, it returns to its initial state. It must be understood that there is a reconstruction within the self-organizing phenomenon in the cardiac system. The principle of unitarity in quantum mechanics is the fundamental reason why information in systems is not lost.
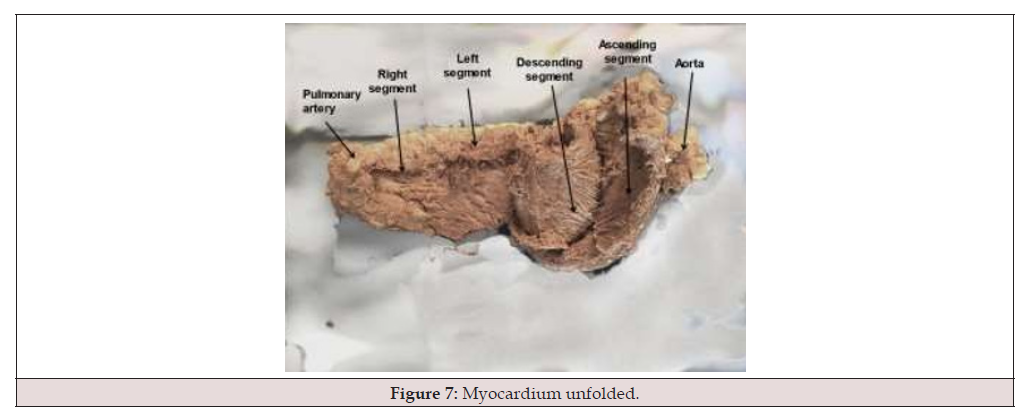
Figure 7:Myocardium unfolded.
Just as the structure of the human body is supported by the insertion of its muscles, upon which forces act to coordinate movement and enable work, the same is true of the heart. It is logical to assume that its helical shape and the remarkable physiological characteristics of the myocardium necessitate a point of support to fulfill its function as a pump, both expelling (torsion) and suctioning (detorsion). The heart is roughly the size of a human fist and weighs an average of 270 grams. It pumps a volume of blood ranging from 4 to 6 liters per minute at a speed of 200 cm/s; it consumes only 10 watts, operates continuously for 80 years without maintenance and almost silently, producing 100,000 beats per day. Its task is equivalent to extracting 1 ton of water daily from a depth of 1 m with a mechanical efficiency (work/energy ratio) of 50%, a feat not achieved by man-made machines, which reach only 30%. Its effectiveness allows it to expel 70% of the left ventricular contents with only a 12% shortening of its contractile unit, the sarcomere [3,4]. Without myocardial support at the Cardiac Fulcrum, this shortening would not be possible.
Regarding the histological constitution of the fulcrum [3,4], it should be clarified that the differences between vertebrates pertain more to a problem of regulation than of structure. Selective pressure from changes in behavior or ecological niche have led to molecular changes. Thus, the conformation of the cardiac fulcrum is dictated by the dynamic need to provide the necessary support for the function it must perform in relation to the heart’s function and power in different mammalian species. Hence, its different histological constitution in different species.
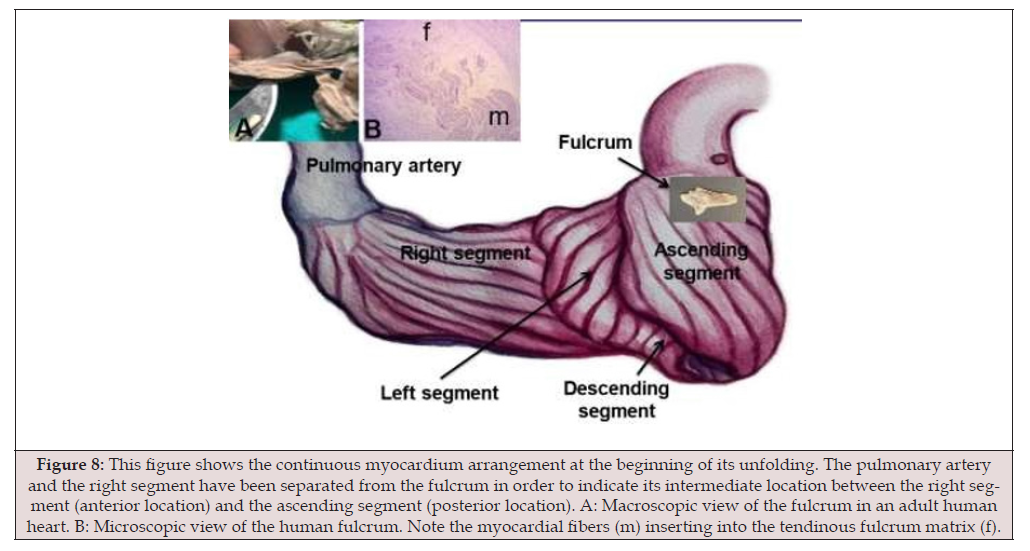
Figure 8:This figure shows the continuous myocardium arrangement at the beginning of its unfolding. The pulmonary artery and the right segment have been separated from the fulcrum in order to indicate its intermediate location between the right segment (anterior location) and the ascending segment (posterior location). A: Macroscopic view of the fulcrum in an adult human heart. B: Microscopic view of the human fulcrum. Note the myocardial fibers (m) inserting into the tendinous fulcrum matrix (f).
Unfolding the heart, layer by layer of muscle, allows us to visualize its true internal architecture, and among these findings, we glimpse the cardiac fulcrum, which emerges from its hidden position to the surface (Figure 8). The heart must be unfolded from its helical conformation to be understood. The heart is organized through a series of successive integrations. The crucial question is: how does the heart function with this double-helix arrangement of its muscle layers?
Relationship of the Cardiac Fulcrum to the AV Node
This research reveals an important topic for understanding cardiac electrophysiology and, consequently, cardiac mechanics. These findings will influence therapeutics, such as pacemaker stimulation and cardiac resynchronization therapy [8,9,13]. Histological analysis revealed that the heart’s support structure, which we have named the Cardiac Fulcrum [3,4,8,9], is adjacent to the AV node, forming a cellular cluster rich in neurofilament plexuses (Figures 9-13). This proximity between the two structures was found in all specimens studied. The key finding of this research is that neurofilaments are also located in the Cardiac Fulcrum, in contact with the myocardial muscle fibers that insert into it.
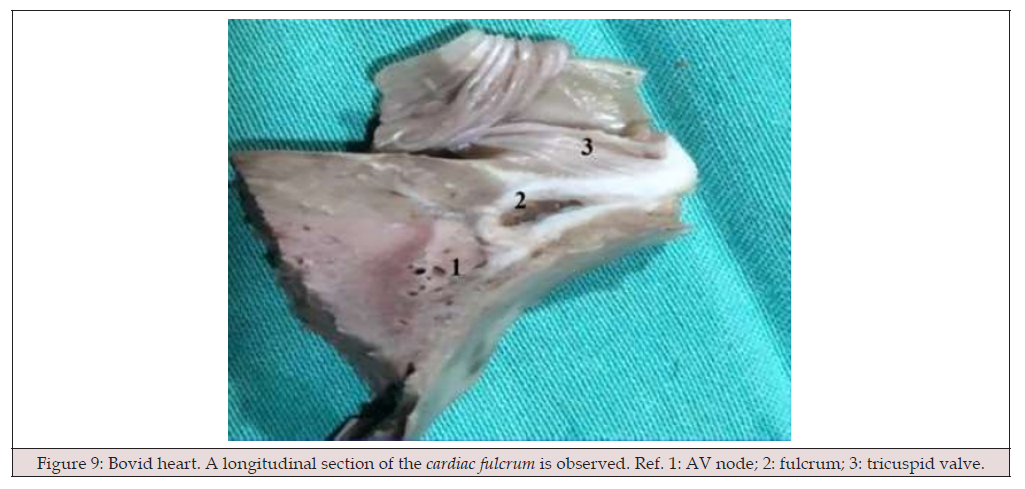
Figure 9:Bovid heart. A longitudinal section of the cardiac fulcrum is observed. Ref. 1: AV node; 2: fulcrum; 3: tricuspid valve.
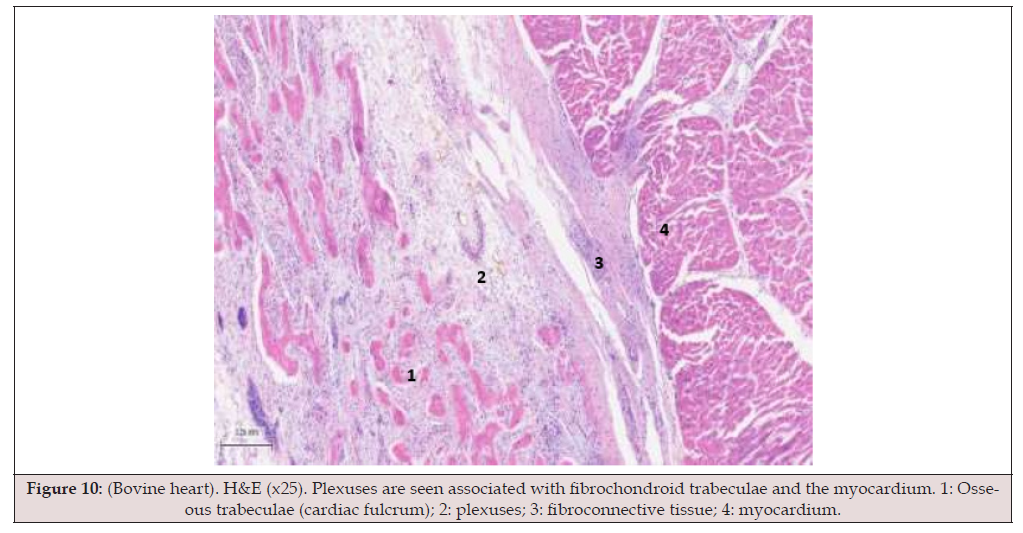
Figure 10:(Bovine heart). H&E (x25). Plexuses are seen associated with fibrochondroid trabeculae and the myocardium. 1: Osseous trabeculae (cardiac fulcrum); 2: plexuses; 3: fibroconnective tissue; 4: myocardium.
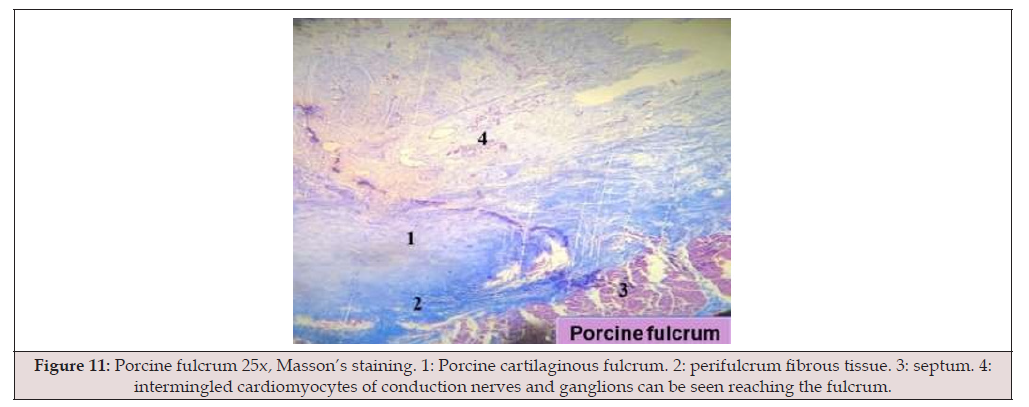
Figure 11:Porcine fulcrum 25x, Masson’s staining. 1: Porcine cartilaginous fulcrum. 2: perifulcrum fibrous tissue. 3: septum. 4: intermingled cardiomyocytes of conduction nerves and ganglions can be seen reaching the fulcrum.
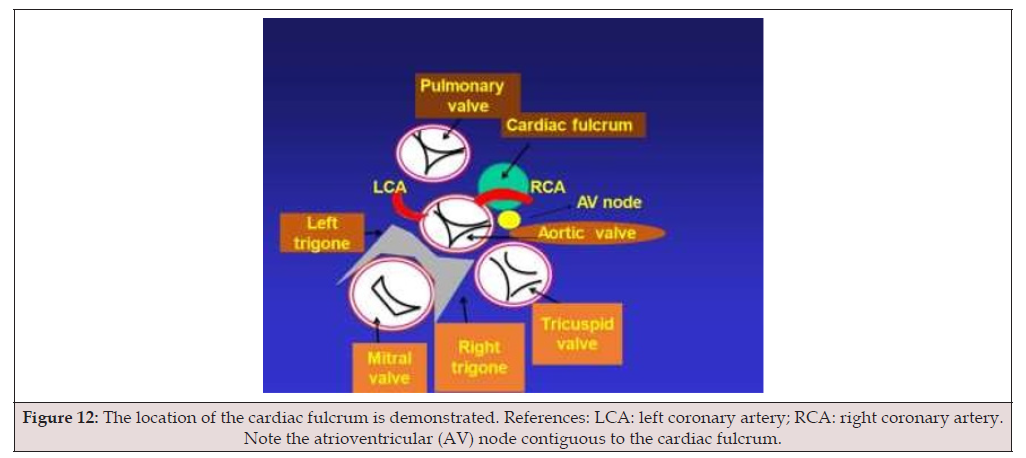
Figure 12:The location of the cardiac fulcrum is demonstrated. References: LCA: left coronary artery; RCA: right coronary artery. Note the atrioventricular (AV) node contiguous to the cardiac fulcrum.
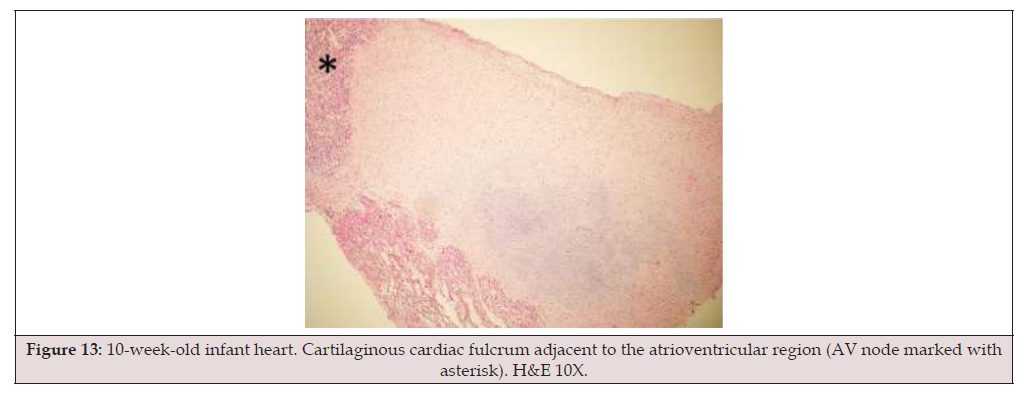
Figure 13:10-week-old infant heart. Cartilaginous cardiac fulcrum adjacent to the atrioventricular region (AV node marked with asterisk). H&E 10X.
The AV node occupies the apex of Koch’s triangle (Figure 2). Its anterior border is defined by the septal leaflet of the tricuspid valve, and its posterior border by the fibrous tendon of Todaro. The AV node also has a compact portion and a marginal portion (transitional cells) located between the right atrium and the node, forming its outer layer. The compact portion is continuous with the center of the cardiac fulcrum.
The cardiac conduction system is embryologically nourished by myocardial precursor cells originating from the splanchnic mesocardium, but the innervation of cardiomyocytes via ganglion cells and fibers also comes from the neural crest. This profound interrelationship between both embryological layers demonstrates an anatomical and functional electromechanical unity. Furthermore, from a histological perspective, the cellular transition from the right atrial wall to the AV node is gradual, making its precise onset uncertain, as stated by Rushmer [5-7]. The same occurs at its point of continuity with the bundle of His. Histochemically, the AV node can be divided into two distinct zones: a compact zone (fast conduction) and an inferior nodal zone (slow conduction).
The location of the AV node, adjacent to the cardiac fulcrum, between it and the septal leaflet of the tricuspid valve, is strategic, as it allows for the modulation of stimulation impulses in the continuous myocardium that originates from the fulcrum along its helical course. In this way, both structures constitute the electromechanical unit of the myocardium. Fibroblasts and connective tissue are located within the conduction system and also between it and the working myocardium, acting as an insulating layer. It is also the connective tissue, which forms the fibrous ring and the central fibrocartilaginous portion of the fulcrum, that electrically isolates the atrial and ventricular chambers (Figures 14-16).
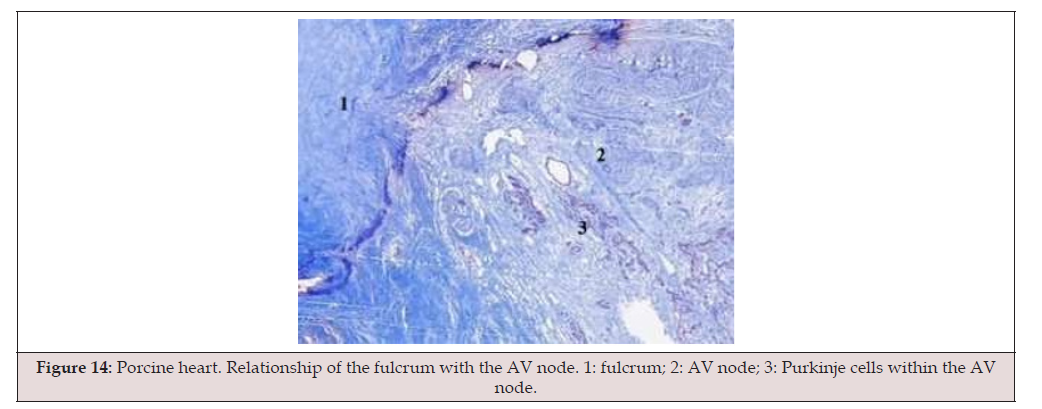
Figure 14:Porcine heart. Relationship of the fulcrum with the AV node. 1: fulcrum; 2: AV node; 3: Purkinje cells within the AV node.
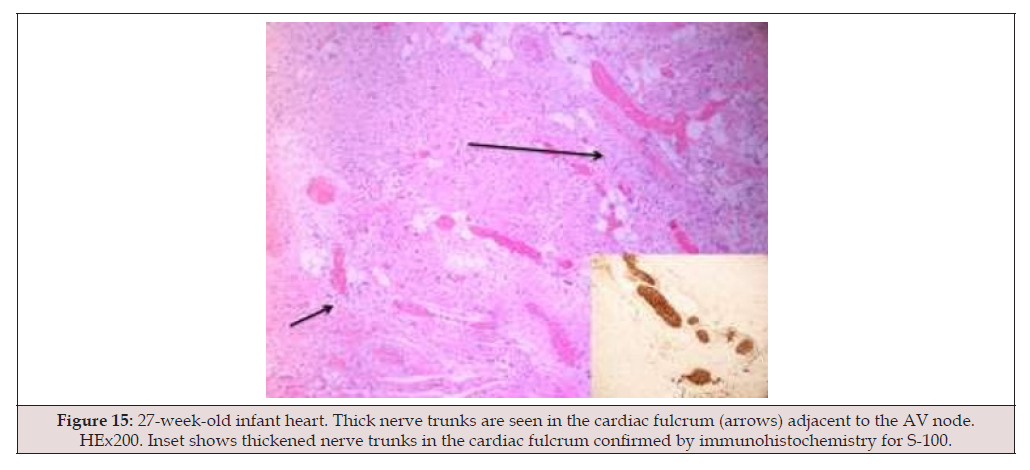
Figure 15:27-week-old infant heart. Thick nerve trunks are seen in the cardiac fulcrum (arrows) adjacent to the AV node. HEx200. Inset shows thickened nerve trunks in the cardiac fulcrum confirmed by immunohistochemistry for S-100.
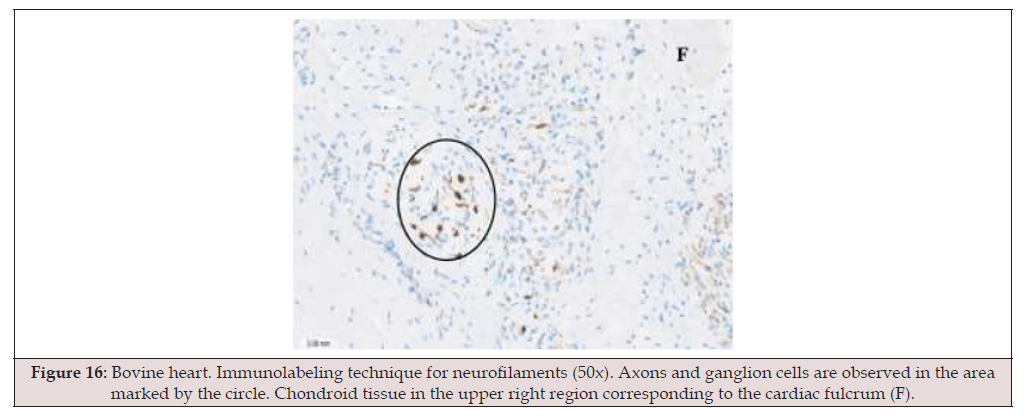
Figure 16:Bovine heart. Immunolabeling technique for neurofilaments (50x). Axons and ganglion cells are observed in the area marked by the circle. Chondroid tissue in the upper right region corresponding to the cardiac fulcrum (F).
Research of Cardiac Electrical Activation with 3D Mapping
Material and Methods
The endo and epicardial electrical activation sequence of the left ventricle (LV) has been studied by means of Three-Dimensional Electroanatomic Mapping (MET) with a Carto navigation and mapping system (Biosense Webster, California, USA) that allows a three-dimensional anatomical representation, with activation maps and electrical propagation. Isochronic and activation sequence maps were generated, correlating them with the surface ECG. Endo and epicardial ventricular activation maps were also produced, obtaining detailed high-density recordings with apical, lateral and basal views. The study was conducted at Presidente Perón Hospital (Buenos Aires, Argentina) including patients who provided their informed consent. The research was previously approved by the Institutional Ethics Committee. All patients were in sinus rhythm, with a normal QRS and did not have evident structural heart disease by Doppler echocardiography and in gamma camera stress and rest studies (Table 1).
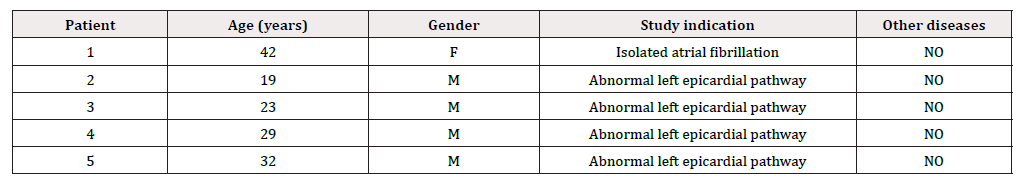
Table 1:Patient characteristics.
The MET mapping was performed during the course of radiofrequency ablation for arrhythmias owing to probable abnormal occult epicardial pathways. Mapping was carried out at the onset of studies, followed by ablation maneuvers. No complications developed. The presence of abnormal pathways did not interfere with mapping, as during the whole procedure baseline sinus rhythm was preserved with normal QRS complexes, both in duration and morphology, without antegrade preexcitation. As the muscular structure of the Left Ventricle (LV) is made up of an endocardial layer (descending segment) and an epicardial layer (left and ascending segments), two approaches were used to carry out mapping. The endocardial access was performed through a conventional atrial transseptal puncture. The epicardial access was obtained by means of a percutaneous approach in the pericardial cavity [14,15] with an ablation catheter. Endo and epicardial mappings were performed consecutively and immediately and were later superimposed, synchronizing them by electrocardiographic timing. Thus, a simultaneous mapping of both surfaces was obtained. In addition, the propagation times of electrical activation through the myocardium were measured in milliseconds (ms).
Until now, the theory of the continuous myocardium lacked an essential investigation, due to the absence of documentation on the electrophysiological mechanism that would support the mechanical activation sequence of the helical anatomical model. The advent of MET managed to overcome this limitation, since it not only allows independent recording of the various ventricular zones, but also those of the endocardium and epicardium, either exclusively or integrated. We mapped the activation of the LV on its endocavitary and epicardial surfaces according to the methodology described. Mapping was performed simultaneously with the surface ECG. This provided a unified temporal frame of reference, allowing on the one hand to correlate both records, and on the other hand to obtain a synchronized view of the simultaneous activation observed in various electro anatomical incidents.
Percutaneous access technique. The Carto system was used for MET to obtain voltage, activation and propagation maps. Epicardial mapping was done in the pericardial cavity through the left paraxiphoid space (Figure 17) [14]. A decapolar catheter in the coronary sinus and a quadripolar catheter in the bundle of His were placed as fluoroscopic reference. Once the epicardial recording of both ventricles was obtained, left ventricular intracavitary mapping was performed. The LV was accessed by transeptal puncture through the right femoral vein using standard technique. In addition, the propagation times of electrical activation through the myocardium were measured in milliseconds (ms).
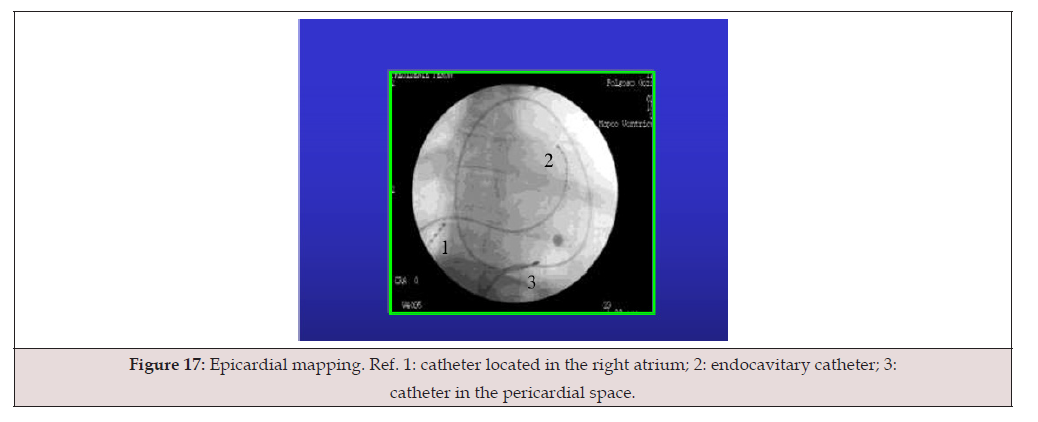
Figure 17:Epicardial mapping. Ref. 1: catheter located in the right atrium; 2: endocavitary catheter; 3: catheter in the pericardial space.
Results
Mapping allowed a detailed activation recording (Figure 18). Although the activation sequence varied in its details, in each case it was similar in its general aspects, forming an endo-epicardial depolarization matrix. As MET corresponded to the LV, the activation wave previously generated in the right ventricle was not obtained.
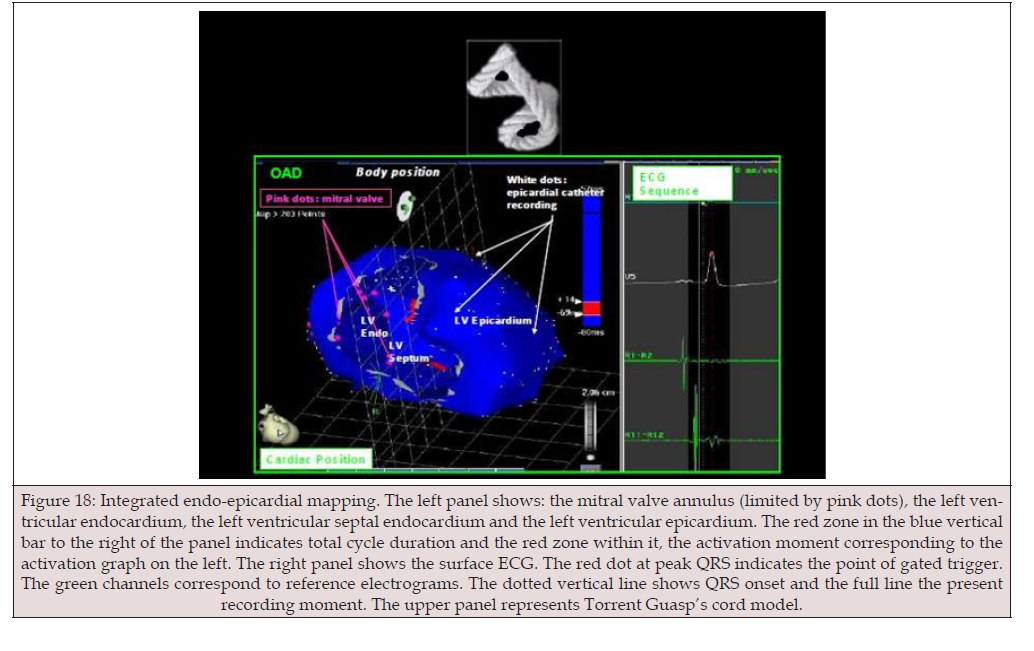
Figure 18:Integrated endo-epicardial mapping. The left panel shows: the mitral valve annulus (limited by pink dots), the left ventricular endocardium, the left ventricular septal endocardium and the left ventricular epicardium. The red zone in the blue vertical bar to the right of the panel indicates total cycle duration and the red zone within it, the activation moment corresponding to the activation graph on the left. The right panel shows the surface ECG. The red dot at peak QRS indicates the point of gated trigger. The green channels correspond to reference electrograms. The dotted vertical line shows QRS onset and the full line the present recording moment. The upper panel represents Torrent Guasp’s cord model.
The MET lasted approximately 20 minutes. There were no complications associated with the procedure or any of the accesses. (Figures 19-21) show the propagation of endocardial an epicardial electrical activation. In all the figures the right projection is observed in the left panel and the simultaneous left anterior oblique projection in the right panel. At each time, the activated zones are detailed in red. The lateral inset represents the activation of the descending and ascending muscle bands that make up the ventricular continuous structure of the myocardium in the cord model, a simplification of the three-dimensional myocardial spatial structure.
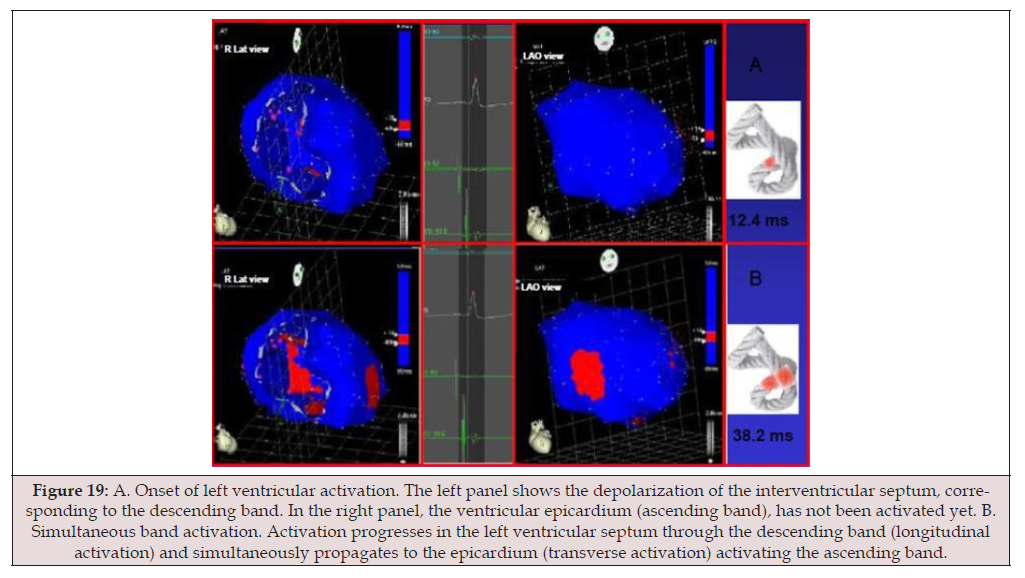
Figure 19:A. Onset of left ventricular activation. The left panel shows the depolarization of the interventricular septum, corresponding to the descending band. In the right panel, the ventricular epicardium (ascending band), has not been activated yet. B. Simultaneous band activation. Activation progresses in the left ventricular septum through the descending band (longitudinal activation) and simultaneously propagates to the epicardium (transverse activation) activating the ascending band.
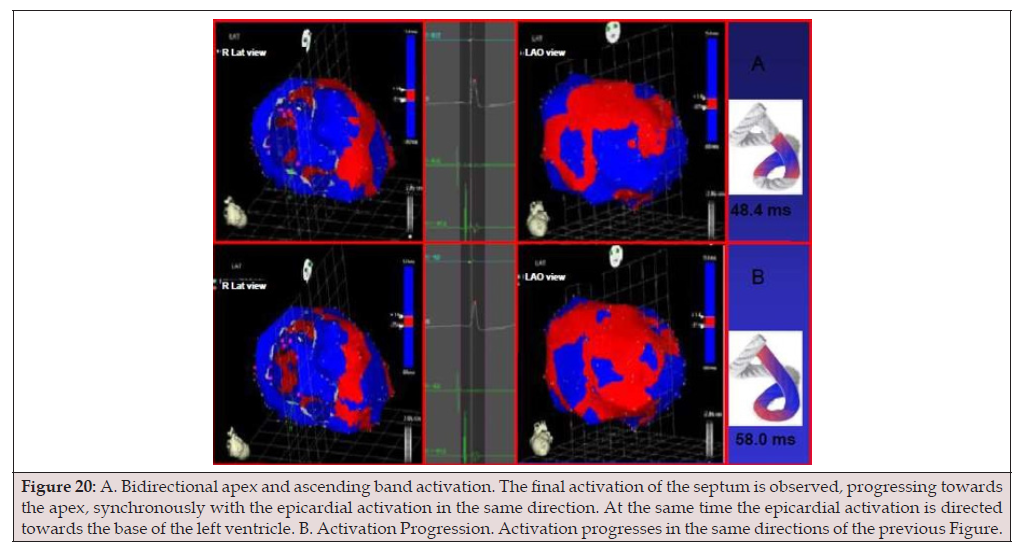
Figure 20:A. Bidirectional apex and ascending band activation. The final activation of the septum is observed, progressing towards the apex, synchronously with the epicardial activation in the same direction. At the same time the epicardial activation is directed towards the base of the left ventricle. B. Activation Progression. Activation progresses in the same directions of the previous Figure.
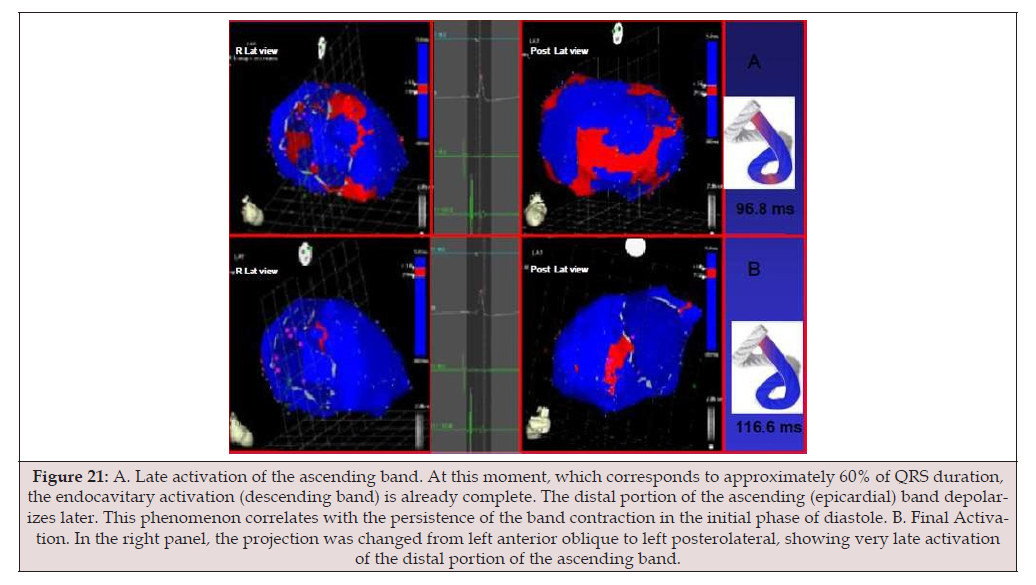
Figure 21:A. Late activation of the ascending band. At this moment, which corresponds to approximately 60% of QRS duration, the endocavitary activation (descending band) is already complete. The distal portion of the ascending (epicardial) band depolarizes later. This phenomenon correlates with the persistence of the band contraction in the initial phase of diastole. B. Final Activation. In the right panel, the projection was changed from left anterior oblique to left posterolateral, showing very late activation of the distal portion of the ascending band.
In all figures, the area depolarized at that time is represented in red and those that were previously activated and are in refractory period are represented in blue. Below the cord model, the average electrical propagation time along the myocardium can be seen measured in milliseconds (ms) at the analyzed site (Tables 2, 3).
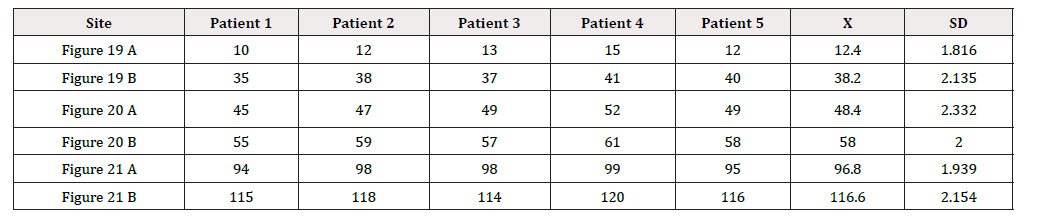
Table 2:Activation times of the different cardiac structures (in ms) (See explanation in the text of the cited Figures). References. ms: milliseconds; X: Mean; SD: Standard deviation.

Table 3:Radial propagation time (in ms). References. ms: milliseconds Pat: patient; X: Mean; SD: Standard deviation.
Left ventricular activation occurs 12.4 ms±1.816 ms after the onset in the interventricular septum (Figure 19 A). This contraction is determined by the bundle of His and its conduction fibers that give origin to the Purkinje network. Based on the anatomy that these fibers occupy, the endocardium is the first area of the LV to receive electromechanical activation. At that moment it also propagates to an epicardial area - ascending band- evidencing a transverse activation at a point we call “band crossover” which is produced 25.8±1.483 ms after septal stimulation (Figure 19 B, Table 3) and at 38.2±2.135 ms from the onset of cardiac activation. This leads to subendocardial shortening and subepicardial lengthening, resulting in opposite rotations between the ventricular base (counterclockwise) and apex (clockwise). In echocardiographic studies verifying stimulation-function at this time of the cardiac cycle, greater systolic torsion was found in the mid-interventricular septum than in the anterior walls. Synchronously, following the anatomical arrangement of the descending band, the activation propagates longitudinally towards the ventricular apex, reaching it at 58±2.0 ms (Figures 20 A and B, Table 2).
From “band crossover” onwards the activation loses its unidirectional character and becomes slightly more complex. Three simultaneous wave fronts are generated: 1) the distal activation of the descending band towards the apical loop, 2) the depolarization of the ascending band from band crossover towards the apex and 3) the activation of this band from the crossover point towards its final portion in its insertion in the cardiac fulcrum, myocardial support. Figures 20 B, 21 A and B show the continuation and completion of this process. Intracavitary activation ends long before QRS termination (Figure 21 A). The rest of the QRS corresponds to the late activation of the distal portion of the ascending band, which justifies the persistence of its contraction during the isovolumic diastolic phase. This contraction constitutes the basis of the ventricular suction mechanism (Figure 21 B), and for this reason, it will be now termed Left Ventricular Protodiastolic Phase of Myocardial Contraction (LVPPMC), as in it there is contraction and no relaxation. A synthesis of the stimulation found in this study is shown with the cord model in (Figure 22) (upper panel).

Figure 22:Cord model. Upper panel: activation sequence (A-F) in the continuous myocardium according to our investigation, with propagation times. The 25.8 milliseconds in B is the stimulation delay to go from the descending band in A to the ascending band in B. References. In red: depolarization; in blue: already activated zones. Lower panel: unidirectional propagation of excitation (in red) in the continuous myocardium according to previous Torrent Guasp’s theory (A-D).
In our research, the right ventricle initiates systolic activity 12.4 ms before the left ventricle. The pulmonic valve opens as soon as its intraventricular pressure rises to 8-10 mm Hg. The inflow region of the right ventricle contracts very early. This right ventricular ejection phase precedes left ventricular systole. Only at an average of 38.2 ms in our research, after the beginning of the cardiac cycle with right ventricular contraction, are the ascending and descending segments stimulated, which would imply left ventricular ejection at that moment, as the aortic valve opens. These 40 ms differences in the earlier opening of the pulmonic valve compared to the aortic valve is logical, since with both ventricles ejecting and filling simultaneously, circulation would be practically interrupted, lacking the necessary continuity and falling to levels even lower than the gradients exhibited by normal circulatory return.
The two synchronized active functions of ejection and suction between both ventricles correspond to circulatory continuity. This raises the question: how is the early opening of the pulmonic valve relative to the aortic valve justified? The ventricles take advantage of the asynchronous impulse of approximately 40 ms, or 5% of the 800 ms duration of the cardiac cycle, so that one of them, the right ventricle, assists the other, the left, during the loading phase, through the complementarity between ejection and suction. This earlier opening of the pulmonic valve relative to the aortic valve, observed in our human studies, has also been seen in fish. Thus, in teleosts (Cretaceous period), which have four cardiac chambers in a line (sinus venosus, atrium, ventricle, and bulbus arteriosus), a similar 40 ms delay in myocardial deflection has been found after the discharge of the electrical spike, between the proximal and distal ventricles at the level of the bulbus, analogous to the right and left ventricles of mammals (Figure 23) (15). This correlation implies an evolutionary biological matrix that transcends species. In this estimated interval of at least 38.2 ms on average in our research, between the opening of the pulmonic and aortic valves, the final phase of left ventricular filling (diastolic period 3) occurs in the left ventricle.
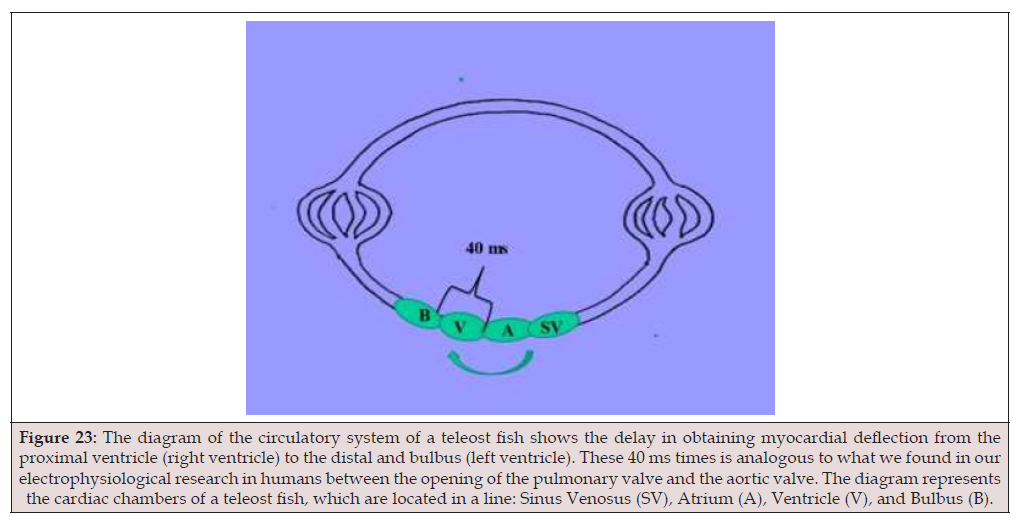
Figure 23:The diagram of the circulatory system of a teleost fish shows the delay in obtaining myocardial deflection from the proximal ventricle (right ventricle) to the distal and bulbus (left ventricle). These 40 ms times is analogous to what we found in our electrophysiological research in humans between the opening of the pulmonary valve and the aortic valve. The diagram represents the cardiac chambers of a teleost fish, which are located in a line: Sinus Venosus (SV), Atrium (A), Ventricle (V), and Bulbus (B).
Discussion
Electromechanical Unit
The helical spatial arrangement of the myocardium forces the muscle to overlap segments in its spatial configuration, which we analyzed and published using the modeling method [3,4] (Figure 24). This anatomical situation is deeply correlated with sequential myocardial movements and with the stimulation that travels through its segments, according to the electrophysiological studies we have performed [16-22]. The interpretation of the anatomical relationships between the Cardiac Fulcrum and the AV Node implies the complementarity of the anatomy with the physiology of the continuous helical myocardium, since their contiguity is found at the site where stimulation begins and ends, the production of which determines the mechanical action of torsion and detorsion in the systolic and suction phases of the ventricles.
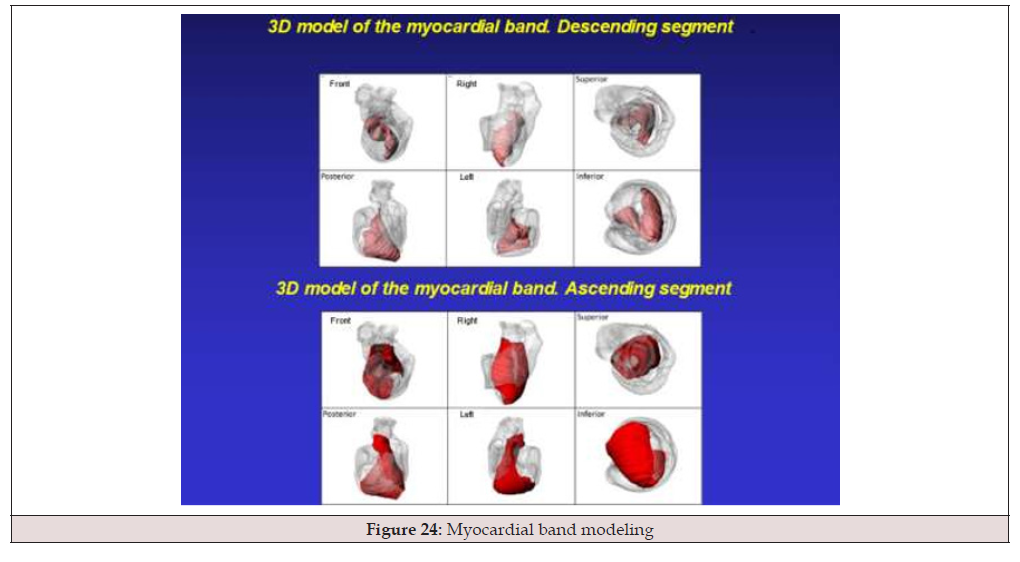
Figure 24:Myocardial band modeling
The cardiac fulcrum, the support and insertion point of the myocardium that acts as a lever during its movements, is located adjacent to the AV node of Aschoff-Tawara (described by Sunao Tawara in 1906). Thus, the two form an electromechanical unit located at the beginning and end of the continuous, helical myocardium. This anatomical and functional arrangement of the myocardium is supported by a rich plexus of specialized filaments located within the cardiac fulcrum that interact with the cardiomyocytes responsible for mechanical work [23].
This interpretation of the findings in the research conducted with human, bovine, and porcine hearts inevitably leads to therapeutic action [24]. What explains the improved synchrony of the pacemakers with the catheter placed near this electromechanical unit? Since the AV node is located at the insertion point of the interventricular septum with the aorta and pulmonary artery, the proximity between the cardiac fulcrum and the beginning of the continuous myocardium along its helical path, in relation to the AV node, demonstrated that stimulation of the right ventricular outflow tract was more effective. In this experience with pacemakers implanted at different points of the right ventricle (apex, parahisian, outflow tract), using standard active fixation catheters, the right ventricular outflow tract achieved better electrical synchrony with the LV [9, 13, 24]. The ideal region for the location of the pacemaker stimulation catheter would be located high in the right ventricular outflow tract, below the pulmonic valve, and preferably over the septum, not on the free wall.
The function of the myocardium provides it with a point of support, as with any skeletal muscle, both at its origin and at its end. If it did not have this spatial anatomical conformation in the helix, but rather an insertion at its ends located at the base of the heart that prevents it from remaining free at the apex, that is, a pendulum in the thorax; and furthermore, if it did not present a stimulation that allowed its torsion and detorsion, it could not fulfill its extraordinary muscular power [24]. The proximity of the cardiac fulcrum to the AV node, surrounded by a rich plexus of neurofilaments (Figures 25 and 26), leads us to consider the anatomical structure of an electromechanical unit involving stimulation energy and muscle mechanics. As previously stated, the effectiveness achieved with the placement of the pacemaker catheter in the vicinity of the right ventricular outflow tract validates the findings of this research.
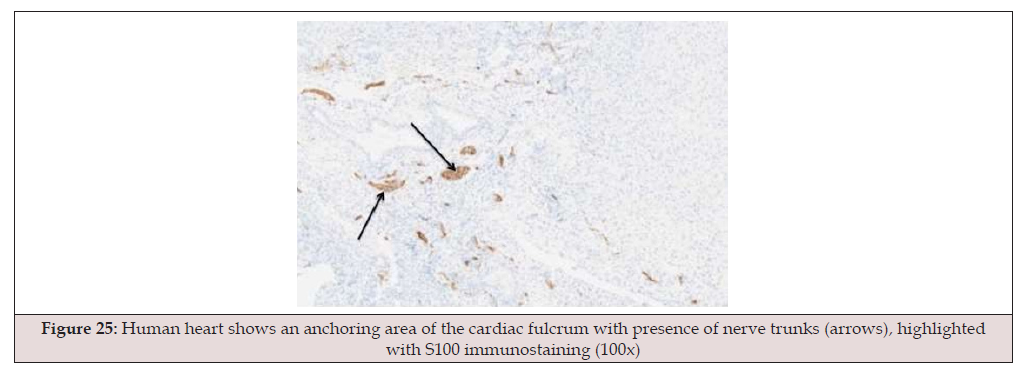
Figure 25:Human heart shows an anchoring area of the cardiac fulcrum with presence of nerve trunks (arrows), highlighted with S100 immunostaining (100x)
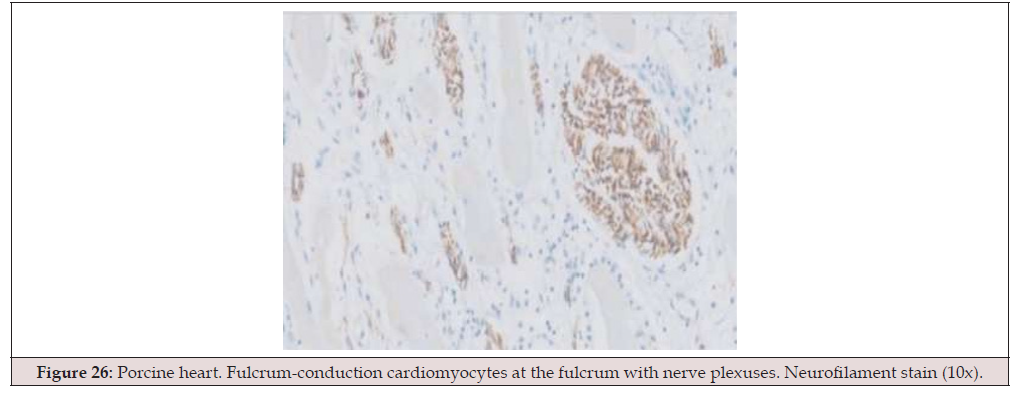
Figure 26:Porcine heart. Fulcrum-conduction cardiomyocytes at the fulcrum with nerve plexuses. Neurofilament stain (10x).
Electrocardiographic Correlation
The onset of the QRS complex correlates with the early endocardial depolarization of the anteroseptal wall of the left ventricle. Epicardial depolarization begins approximately 38.2 ms later, according to our research, after the endocardial segment. Corresponding to approximately the final 40% of the QRS complex, coinciding with the positive peak of dP/dt, there is persistent contraction of the ascending segment of the apical loop, as demonstrated in the endoepicardial electrophysiological mapping recordings we performed after aortic valve closure, during the first 80-100 ms of diastole. We have termed this phase the Protodiastolic Phase of Myocardial Contraction (PPMC) due to its energetic activity. It corresponds to the phase classically known as the isovolumetric diastolic phase, which is erroneously considered inactive. Of course, it should be noted that there are small differences between the start and end times of the QRS complex and of the intracavitary and epicardial potentials similar to those recorded in electrophysiological studies.
Since Harvey and later Einthoven, both the mechanical contraction and electrical activation of the heart have been considered almost linear and homogeneous processes. According to the classical concept, normal ventricular activation should begin in the septum, continue at the apex, and end in the basal region. In this way, contraction would occur en bloc during systole, and relaxation would be almost homogeneous during diastole. Systole is synonymous with cardiac contraction, and diastole with relaxation. These have been the classical foundations. At this stage of our understanding, they must be considered more complex, as they were conceptualized without taking into account the helical structure of the continuous myocardium and its sequential dynamics.
While various aspects of electrical impulse propagation in the ventricles have been known for a long time, the advent of threedimensional navigation systems and electro anatomical mapping have allowed for a much more detailed study of propagation in the human heart under entirely physiological clinical conditions. This has revealed several interesting characteristics:
1) Normal electrical activation, while basically orderly and homogeneous, is very complex, especially in the areas that depolarize later.
2) Endocavitary activation occupies approximately 60% of the initial surface QRS complex. The remainder of the QRS complex corresponds to myocardial and epicardial activation. The beginning of ventricular activation, evidenced by the QRS complex, is therefore exclusively endocardial; during the intermediate phase, both activations coexist, and finally, during suction, activation is exclusively myo-epicardial.
3) The end of contraction of the ascending segment of the apical loop is protodiastolic. It follows that the phase classically called isovolumic relaxation is an active process with energy expenditure. For this reason, we have termed it PPMC (Protodiastolic Phase Myocardial Contraction).
There are some aspects of our research that allow for theorizing:
1. While there is no problem in defining the beginning of
systole as the moment the mitral valve closes and the beginning
of diastole as the moment the aortic valve closes, this in no way
implies that the contraction and relaxation processes begin at those
precise moments. On the contrary, it is obvious that the ventricular
contraction that generates the pressure increase required for mitral
valve closure occurs before that point (i.e., during diastole), and
the relaxation that reduces intraventricular pressure and allows
aortic valve closure begins before that point, i.e., during systole.
It is also logical to infer that not all myocardial fibers contract or
relax simultaneously, given the constitution of the continuous
myocardium in a helix with a sequential movement, but rather that
in certain periods (impossible to quantify in each individual fiber
in its duration) fibers coexist in various stages of contraction and
relaxation, both during systole and during diastole.
2. The final state of contraction achieved (and therefore the geometric configuration of the ventricle in general and its cavity in particular) must depend to some extent, perhaps a very significant one, on the contraction or relaxation state of the adjacent fibers and structures. It would seem logical to assume that the first fibers to contract, surrounded by relaxed fibers, can reach their maximum degree of potential contraction; conversely, if the adjacent fibers are already contracted and “pulling” in the opposite direction, their effective degree of contraction would be less.
3. Electromechanical coupling. Although electrical depolarization triggers mechanical contraction, from that moment on these two processes are distinct and autonomous. Membrane activation can occur without mechanical contraction; evidence of this is neuronal electrical activation, which leads to the release of neurotransmitters but not to contractile activity.
We assume that if, for example, a selective inhibitor of actinmyosin activation existed, we would have normal depolarization without muscle contraction. Furthermore, the temporal relationship between electrical activation and mechanical contraction is not linear. It is well known that there is a latency between electrical and mechanical activation. Thus, the time between electrical activation and contraction (at least maximal contraction) likely varies depending on multiple factors: the type of fiber, its metabolic state, its location within the myocardium, the intracellular calcium level, the contraction or relaxation of neighboring fibers, and so on.
Let’s consider typical situations: the QRS complex norma lly lasts around 100 ms. Systole, plus the PPMC, lasts 400 ms. Therefore, the effect of the QRS complex on total ventricular contraction “lasts” for at least 300 ms after its termination. Fibers activated at the end of the QRS complex contract or maintain their contraction at the beginning of diastole, during the first 100 ms of PPMC. It would not be necessary, therefore, for depolarization potentials to exist within the T wave to justify muscle contractions during diastole (which, as we have already mentioned, is not synonymous with the relaxation of all cardiac fibers).
Given this situation of electromechanical decoupling, there is a crucial point to develop, which is the interrelation between energy (stimulus) and matter (myocardium) with its continuous selforganization process in the production of the sequence of cardiac movements. This is what we have investigated and termed the electromechanical unit. We reiterate that, during this investigation, in both human and bovine hearts, histological study revealed that the fulcrum (beginning and end of the continuous myocardium) is adjacent to the AV node, defining a synergistic space rich in plexuses with neurofilaments. A fundamental and crucial finding is that the neurofilaments also occupy the cardiac fulcrum in their innervation of the myocardial fibers, constituting an electromechanical unit [25-27].
We performed a mapping of left ventricular activation on its endocavitary and epicardial surfaces according to the described methodology. The mapping was performed simultaneously with the surface ECG. This provided a unified temporal frame of reference, allowing us to correlate both recordings and obtain a synchronized view of the simultaneous activation observed in various electro anatomical views. This research found a relationship between myocardial stimulation and its mechanical product. The mechanical consequence in the cardiac structure is the initiation of stimulation in the electromechanical anatomical-functional unit between the AV node and the cardiac fulcrum, and its continuation in myocardial activation up to the zone of simultaneous activation with opposing movements between the descending and ascending segments. This generates ventricular myocardial torsion through opposing rotation between the base and the apex, with simultaneous shortening of both ventricles.
At this point in the discussion, the essential question remains: if the QRS complex normally lasts around 100 ms, why does the mechanical contraction (systole + PPMC) last an additional 300 ms? Therefore, the effect of the QRS complex on the total ventricular contraction “persists” for at least those 300 ms after its termination. Given this situation, we must analyze the AV node’s behavior and its relationship to the fulcrum, the site where the continuous myocardium begins and ends after its helical configuration. It can be conjectured that the cardiac fulcrum-Atrioventricular Node (AVN) complex acts as the electro-mechanical self-organizing unit of the cardiac system. The fulcrum is not merely an inert anchor point. Having a central section that acts as a lever and a pole in contact with the AVN, it involves a signal in the heart’s mechanics (the contraction and torsion of the muscular band) that the fulcrum transforms into a pulsatile tilting movement. This suggests that the fulcrum allows the AVN to “feel” the mechanical tension. To explain this physiology of cardiac mechanics, we will first analyze some concepts to understand the self-organization process, such as: a) thermodynamics of life, b) implexion, and c) entropy.
Thermodynamics of Life: The second law of thermodynamics, which states that in an isolated system the entropy or disorder of the system evolves toward a maximum (Rudolf Clausius, 1865), has played a fundamental role in understanding the new worldview (28-30). Boltzmann explored this relationship between dynamics and kinetics, constructing his microscopic model of entropy. Thus, far from the anxiety that this second law of thermodynamics might instill regarding a final equilibrium, science discovers the creative power of time. The entire cosmos is constantly transforming itself within this perspective of before and after that shapes time. Entropy measures the amount of molecular disorder in a system. To this end, William Thomson, Lord Kelvin (1824-1907), in 1855, established the notion of the heat death of the universe with this word. At this point, Darwin and Boltzmann converge in a dispute. The first establishes that living beings grow and transmit information from the past subject to change, while for Boltzmann, in an infinite number of particles, collisions lead to entropic growth and thermodynamic irreversibility [31-33].
The emergence of life allows for its transmission from one individual to another, from one species to another, and adds complexity to this transformation. It is the realm of the non-linear. This is also true of human behavior. The brief scale of human history in relation to that of the universe helps us understand the instability and fluctuation to which all systems in the universe are subject. This is an anti-entropic world, now well understood by scientific rationality through the evolution of systems far from equilibrium, to which humankind belongs. The events that occur in this self-organization are coherent; they are not random processes, bearing in mind that it imposes a difference between past and future. In these events, there is irreversibility, but also coherence.
Darwin triumphed. Boltzmann acknowledged that he lacked a microscopic interpretation of the irreversibility of his system. It was the age-old debate between Parmenides’ static and predictable world and Heraclitus’ continuous transformation. A system can, over time, return close to its origins, but it will never be the same. There is always change, which we call time. And a purpose that drives birth, growth, reproduction, and death. The heart gives meaning to time, since without it, existence would be impossible if it could not fulfill its cardiac cycles within established timeframes.
We must understand that the relationship established by kinetic theory between dynamics and thermodynamics is what leads to physicochemical processes. New conceptions in the sciences can be traced back to Ludwig von Bertalanffy’s (1901-1972) general systems theory, Norbert Wiener’s (1894-1964) cybernetics, and Claude Shannon’s (1916-2001) information theory [34,35]. Today, they respond to Ilya Prigogine (1917-2003, Premio Nobel de Química, 1977), postulate, based on the concept that systems far from equilibrium are also found in the natural and social sciences [33, 36-38]. The systems that comprise the cosmos in its entirety belong to one of three states:
a) At equilibrium, there are no differences in temperature or
concentration. Inert. The entropy they produce is zero.
b) Near equilibrium, they reach equilibrium when there is no
longer a difference in concentration. They exist with a small
thermodynamic difference.
c) Far from equilibrium (they produce entropy). They exhibit
fluctuations toward the new dynamic regime. They evolve
through periodically indeterminate nonlinear transformations
toward regions increasingly distant from equilibrium. These
are the third-state systems and constitute the main elements
of the general synthesis of evolution.
The sciences cannot be isolated. The interrelation (implexion) between them is fundamental to understanding problems. A convergence of biology and physics is absolutely necessary. Physics, with its profound transformation, has achieved a language for relating the sciences with surprising possibilities. In fact, it has allowed us to understand the evolution of living matter, which, before the physical revolutions of the 20th century, was thought to violate the second law of thermodynamics. Today we know that this is substantially different and that an open system self-organizes through a thermodynamic gradient. Information is accumulated through the system’s interactions with its environment. Ilya Prigogine’s “theory of dissipative structures” demonstrates that human beings and the microcosm share analogous characteristics. According to this theory, parametric requirements drive the evolution of systems.
The thermodynamic view of matter emerged around the mid- 18th century. James Watt (1736-1819) and James Joule (1818-1889) were its precursors, with Hermann von Helmholtz (1821-1894) describing the principle of conservation of energy in all systems. In 1824, Nicholas Léonard Sadi Carnot (1796-1832) established the explanation for the dissipation of mechanical energy. Subsequently, in 1865, Rudolf Clausius (1822-1888) established the laws of thermodynamics.
In summary, the understanding of dissipative structures, nonequilibrium states, particle collisions, fluctuations, instability, and irreversibility is only possible within the framework of modern physics [39]. Living beings are open systems connected to the external environment. Their thermodynamic foundation implies that, by being interconnected with the external world through a flow of matter and energy, they constantly experience a gradient that moves them away from disorder, chaos, inertia, and uniformity, and allows for a continuous process of self-organization [40]. Thermodynamics plays a fundamental role in the functional behavior of the heart. The condition is that it remains at a certain distance from thermodynamic equilibrium through a flow of matter and energy, which determines fluctuations.Living beings are thermodynamic systems that contain heterogeneity composed of more stable and less stable structures, also called systems that are closer to equilibrium, or further from it.
Entropy: Understanding the value of entropy in the organization of scientific disciplines involves referring to the second law of thermodynamics, which states that in any isolated system, organization and structure tend to disappear and be replaced by uniformity and randomness [41]. Systems form a continuum in matter, life, and history. Older levels exhibit strong and consolidated links, in contrast to more recent ones, which are weak and flexible. There is no hierarchical separation in the levels of complexity, but rather complementary integration between them. Complexity allows for the association of structures. Suddenly, this alchemy reaches a level that was previously dissociated [42- 44]. It is fundamental to understand the concept of feedback: in this temporal course that involves reaching maximum disorder, the system’s input of external energy (information) can modify its course, potentially reactivating it, decreasing the level of entropy, and preventing the system from closing and evolving toward its thermal death.
Some systems, when the bond that maintains them in a dynamic state disappears, enter a chaotic state, but other systems, such as chemical ones, are a source of new structural creations [45- 47]. In 1958, Boris Belousov (1893-1970), while mixing chemicals, observed that the solution changed color periodically. The reaction reversed and then advanced again, similar to a chemical clock. This finding was ignored at the time in academic circles. Re-examined by Anatol Zhabotinskii (1938-2008), this phenomenon now bears both their names. The explanation is that the reaction, by remaining far from equilibrium and having a feedback mechanism, influences its own dynamics. This is called autocatalysis and constitutes positive feedback, corresponding to a non-linear equation. Here, irreversibility escapes the lack of entropy and fleeting behavior, evolving toward new evolutionary possibilities. It moves from synthesis to information. Irreversibility and probability are not concepts of our limited knowledge, but rather reflect the existence of a chaotic dynamic system with a time horizon that limits the permanence of any information regarding the future. This explanation of self-organizing processes is a situation that had already been observed in other fields by Hegel, Darwin, Marx, and Engels [48-49]. The continuous transformation, observed in antiquity by the Greeks with the term “trope,” is now known as “entropy.”
An old proverb says that all knowledge is bound to evolve, otherwise it regresses. The evolutionary progress of a discipline, if it remains temporary and without implexity (interconnection) with other disciplines, ends up isolating itself (its entropy increases). It needs to decrease this entropy (negentropy) by remaining open through genuine growth in connection with elements close to its system. In a way, we are using the concept of complexity, that is, the possibility of complementarity to evolve, preventing it from falling into a state of equilibrium (inactivity).
In short, the universe is change, and therefore, so is the knowledge we gain from it. It is subject to fluctuations and random processes in its transmission from the past to the future. The word entropy implies something different from the original term used by the Greeks to signify the transformation to which they referred. In this sense, as understood in current physics, systems move towards a maximum possible state.
Biological systems, like social, economic, and physical systems, are composed of a large number of components, which translate into random behavior that invalidates the classical scientific method. In the 19th century, the social field offered a solution to this obstacle in scientific methodology when Adolphe Quetelet (1796- 1874) developed the feasibility of probability or statistics in 1820. However, this political arithmetic applied to populations succumbs to the randomness of a singular and unique system such as each human being. The knowledge of quantum mechanics has helped us understand the randomness and uncertainty inherent in systems.
Implexion: Modern physics has described the universe using the concept of implexion, from the Greek “emplexis”, which has the capacity to relate the human mind to the entire universe not only as intertwined entities, but as constituents of the whole. And this is notmerely the transfer of information between physical particles; it also implies the superposition of states. The friar Gregor Mendel (1822-1884), from the Austro-Hungarian Empire, working with peas, established the laws of genetics, which summarized what the Greek philosopher Plotinus had already stated in the 3rd century with this concept: “Everything is everywhere. Each one is the All and the All is each one” [50]. The concept of the holoverse must be seen in the depth of Mendel’s work. The subsequent development of electrodynamic theory by Michael Faraday (1791-1867) and James Maxwell (1831-1879) in the 19th century marked the beginning of the collapse of the old physics. The transcendent step they achieved with the concept of a field-the potential to produce a force in spacemarked the beginning of subsequent scientific revolutions. In the following century, the theories of relativity, quantum mechanics, chaos theory, and the concept of dissipative structures would be successively linked [51].
The behavior of the non-biological has been conceptualized and recorded within statistics, a situation that cannot be applied with evidentiary force to living beings. Perhaps we should understand that the interaction from elementary particles to planets is not the same measure to which human emotions are subjected. This concept implies understanding that the behavior of human beings is unique and their qualitative responses cannot be definitively determined with a purely quantitative tool [52-54]. Ilya Prigogine, for his part, considers that the guiding principles operate throughout the universe, from atoms to human beings [55-59].
nterpretation of Myocardial Activation in Relation to the AV Node, Cardiac Fulcrum, and the Torsion Mechanism
We were able to begin this path of analyzing the selforganization of the helical myocardium with the knowledge of the morphological, histological, and functional relationship between the AV node and the cardiac fulcrum, the latter being the site where the myocardium originates and terminates after its helical course [3,4]. For a proper understanding of the heart as a participant in the quantum concepts of current science, it seems appropriate to first explain the interpretation of myocardial activation in relation to the cardiac fulcrum and the torsion mechanism (Figure 1). In this sense, the words of León Rosenfeld are relevant: “a theory is understood through its limits” [33]. The complexity of biological phenomena implies dynamism, progression, and the simultaneous coexistence of diverse stages and different structures within an organizational unit. The same occurs in the heart from the perspective of electrical, mechanical, and electromechanical phenomena, including myocardial activation, contraction, and relaxation during systole, suction, and diastole.
There is always an instance in nature where it is possible to integrate higher-level functions with the components that make up a system [34,35]. This is the case of the “center of the pulse.” The heart has historically been studied in terms of its individual components, exhibiting a global and homogeneous contraction, simultaneous throughout its muscular structure; but not with a clear understanding that the movements in its different phases occur sequentially and overlappingly, contributing to its complex function in an infinitesimal time of less than one second per cycle and 110,000 cycles per day. The heart has been studied only partially, undoubtedly because attributing the complexity of its function to the duration of its cycle implies the difficulty of observing the reality that unfolds within it. Due to the rapidity of cardiac movement, Girolamo Fracastoro (Verona, 1478-1553) had expressed the impossibility of understanding its mechanism [60]. It is understandable to consider that the integrity proposed by the general systems theory will remain relegated as long as adherence to purely analytical models continue, as the whole is reduced to the sole study of its parts.
Through the development of technology applied to morphology, a comprehensive biological perspective adapted to functional requirements was achieved [3,7,11,61]. This view of the cardiac organ and its function, which we have investigated, is consistent with the general systems theory [62-64], a situation we consider throughout the research.
Our previous publications concerning the cardiac fulcrum as a support for the myocardium, its relationship with the Aschoff- Tawara node, and the sequential activation of the heart in a clear organizational arrangement to achieve torsional movement [3- 4], led us to analyze these structures in terms of their potential and functional aspects [12]. Thus, we arrived at the concept that the heart acts through three fundamental units: activation, electromechanical unit, and myocardial torsion, which are interrelated in their anatomy and organization to act in accordance with a highly efficient system (Figure 1).
In summary, the research results reveal the key reference points that define the organizational pattern of cardiac function. These are: the anatomical contiguity between the AV node and the cardiac fulcrum; the continuous presence of the filaments that structure the AV node with the fulcrum-where the myocardium originatesclearly forming an electromechanical unit; and the pathway of activation through the myocardium that enables helical torsion, achieved through the anatomical, anisotropic, and functional spatial arrangement between the descending and ascending segments at the septal level, as confirmed by echocardiographic and electrophysiological studies. At this point, we must analyze how these elements, including structures and circuits of energy and mechanical transfer, interact.
The analysis is deeply correlated with myocardial movements and the stimulation that travels through its segments, according to the electrophysiological studies we have carried out [3,4]. The interpretation of the anatomical relationships between the cardiac fulcrum and the AV node implies the complementarity of the anatomy with the physiology of the continuous helical myocardium, since their contiguity is found at the site where stimulation begins and ends, with the production of the mechanical action of torsion and detorsion in the systolic and suction phases of the ventricles as the different segments of the myocardium are activated.
Myocardial torsion
Although various aspects of the propagation of the electrical stimulus through the ventricles have been known for a long time, the advent of three-dimensional navigation systems and electro anatomical mapping have allowed a much more detailed study of it in the human heart in totally physiological clinical situations.
As previously mentioned, left ventricular activation begins in the descending endocardial segment, which depolarizes longitudinally and transversely with a 12.4 ms delay relative to the baseline loop (right and left segments). At the point of contact with the ascending segment, activation propagates from the endocardium to the epicardium (transverse propagation), that is, from the descending to the ascending segment, with a 25.4 ms delay, thus totaling 38.2 ms from the start of cardiac stimulation. From this point, the ascending segment depolarizes in both directions: toward the apex and toward the base, while the descending segment completes its activation toward the apex (Figure 20). Thus, as we have analyzed, two primary phenomena occur:
1. The apical loop, upon depolarization from the crossing
of the segments, with two simultaneous wavefronts (from the
descending and ascending segments), generates a synchronized
contraction of both.
2. Activation of the ascending segment occurs from
the crossing in two opposing directions: toward the apex and
toward the base. The resulting mechanical contraction will also
have an opposing direction, giving rise to clockwise (apex) and
counterclockwise (base) rotations.
The helical spatial arrangement of the myocardium forces the muscle to overlap segments in its spatial configuration. This situation is clearly observed in the modeling achieved in previous research that we have presented [65].
In a cardiac cross-section (Figure 27) below the atrioventricular valves, we can observe that the descending segment is located internally, surrounded by the ascending segment on the free wall of the left ventricle [4]. The ascending and descending segments move in opposite directions, both during systole and diastole, to achieve ventricular ejection and suction, generating friction between their surfaces. This topic has been addressed in other publications, where we found abundant amounts of hyaluronic acid, a lubricating substance, in both the myocardium and the Thebesian vessels in studies conducted on anurans, cattle, and humans (Figures 28- 30) [66, 67]. The histology in the inset of (Figure 27) clearly shows the different orientation of the fibers of the descending segment in relation to the ascending segment, which explains their opposing movements. The arrangement of myocardial fibers in the epicardium and endocardium, with a 180° change in angle, results in the epicardial fibers being oriented in the opposite direction to the endocardial fibers. Given the different anisotropic orientations of the fibers, this area corresponds to the beginning of the opposing movement that produces myocardial torsion. The structure of the septum, with the contiguity between the descending and ascending segments, allows for continuous activation between them with opposing movements and the consequent myocardial torsion (Figure 31). The interventricular septum plays a predominant role in myocardial function, given its essential position in biventricular interdependence [68].
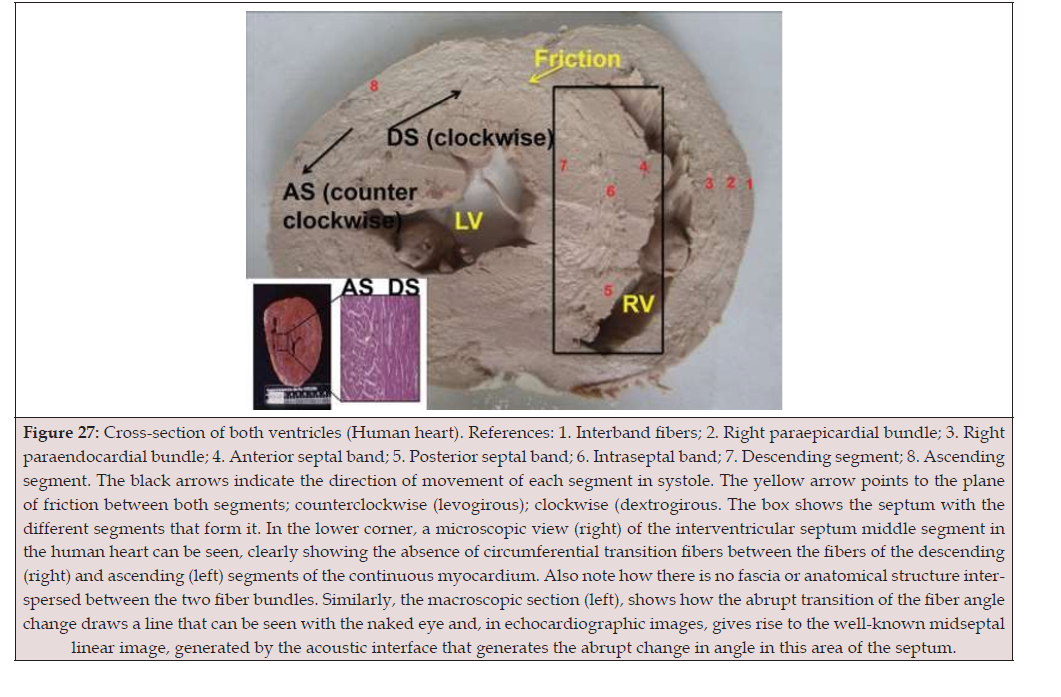
Figure 27:Cross-section of both ventricles (Human heart). References: 1. Interband fibers; 2. Right paraepicardial bundle; 3. Right paraendocardial bundle; 4. Anterior septal band; 5. Posterior septal band; 6. Intraseptal band; 7. Descending segment; 8. Ascending segment. The black arrows indicate the direction of movement of each segment in systole. The yellow arrow points to the plane of friction between both segments; counterclockwise (levogirous); clockwise (dextrogirous. The box shows the septum with the different segments that form it. In the lower corner, a microscopic view (right) of the interventricular septum middle segment in the human heart can be seen, clearly showing the absence of circumferential transition fibers between the fibers of the descending (right) and ascending (left) segments of the continuous myocardium. Also note how there is no fascia or anatomical structure interspersed between the two fiber bundles. Similarly, the macroscopic section (left), shows how the abrupt transition of the fiber angle change draws a line that can be seen with the naked eye and, in echocardiographic img, gives rise to the well-known midseptal linear image, generated by the acoustic interface that generates the abrupt change in angle in this area of the septum.
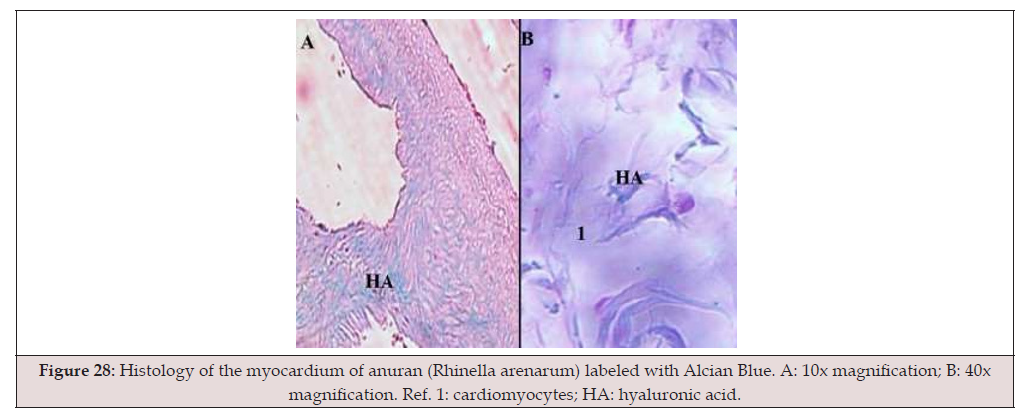
Figure 28:Histology of the myocardium of anuran (Rhinella arenarum) labeled with Alcian Blue. A: 10x magnification; B: 40x magnification. Ref. 1: cardiomyocytes; HA: hyaluronic acid.
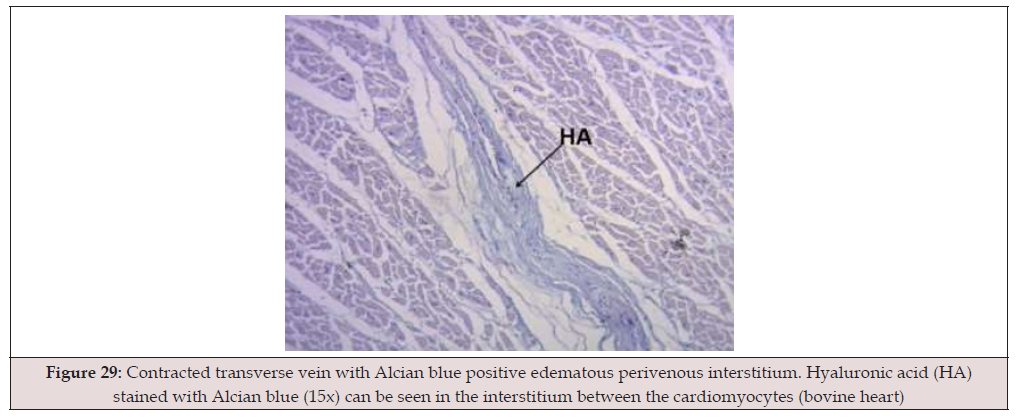
Figure 29:Contracted transverse vein with Alcian blue positive edematous perivenous interstitium. Hyaluronic acid (HA) stained with Alcian blue (15x) can be seen in the interstitium between the cardiomyocytes (bovine heart)
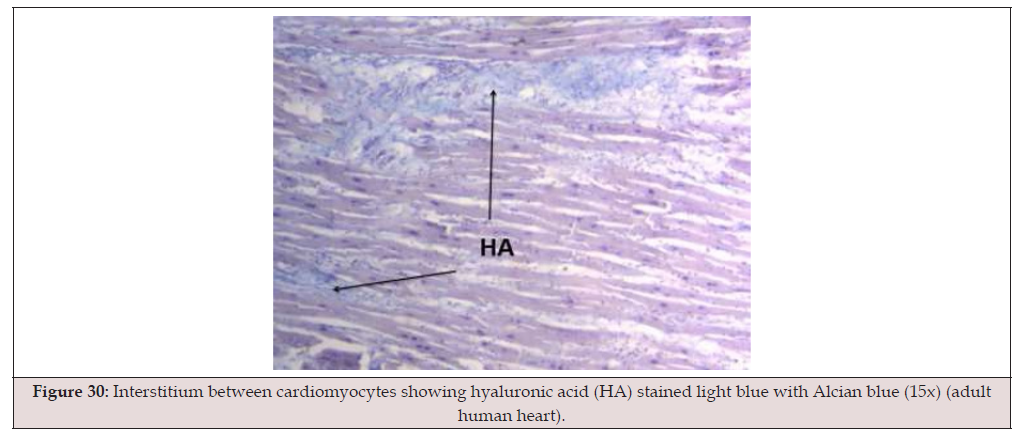
Figure 30:Interstitium between cardiomyocytes showing hyaluronic acid (HA) stained light blue with Alcian blue (15x) (adult human heart).
An important detail derived from fractographic img is their correspondence with the angulation changes observed in the two-dimensional sections published by Streeter or with the rough arrangement of the band bundles in the anatomical sections of dissected hearts, highlighting the abrupt change of angulation present in the interventricular septum, due to the absence of transition of fibers with circumferential course, since the septum is a structure that results fundamentally from the apposition of the descending and ascending segments of the continuous myocardium (Figure 31) [3].
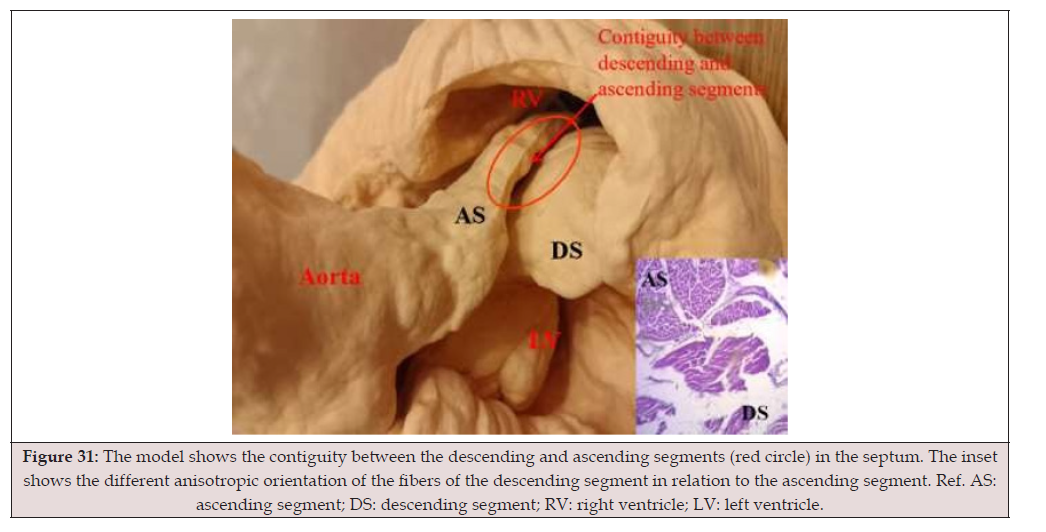
Figure 31:The model shows the contiguity between the descending and ascending segments (red circle) in the septum. The inset shows the different anisotropic orientation of the fibers of the descending segment in relation to the ascending segment. Ref. AS: ascending segment; DS: descending segment; RV: right ventricle; LV: left ventricle.
The research on the stimulation sequence allowed for the determination of electrophysiological propagation in the continuous myocardium and also led to deductions regarding ventricular torsion and the suction effect in PPMCLV [69]. The orientation of the fibers in the continuous myocardium and their activation involve a concatenation of muscle movements in cardiac mechanics. These movements occur in four phases: constriction, shortening-torsion, lengthening-detorsion, and widening, which allows it to perform its functions of systole, suction, and diastole. The fundamental movements in which the different segments of the continuous myocardium participate during systole and suction are shown in (Table 4).
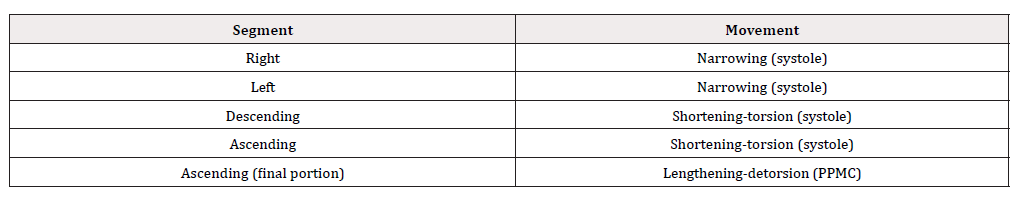
Table 4:Segment function Reference. PPMC: Protodiastolic Phase Miocardial Contraction.
This sequential activation correlates with well-established fundamental phenomena, such as the opposing clockwise and counterclockwise torsion of the apex and base of the left ventricle, responsible for its mechanical efficiency. In order to attempt to explain the mechanism of this muscular torsion, this research aimed to analyze the sequence of ventricular electrical activation using simultaneous endo-epicardial band MET of the segments from their origin at the anatomical and functional contiguity between the AV node and the cardiac fulcrum.
During the narrowing phase, there is a sequential contraction of the right (free wall of the right ventricle) and left (edge of the mitral orifice) segments, which together form the basal loop. According to Armour (1970) [70], this contraction forms an external covering within which the apical loop will contract. In reality, the crescent shaped free wall of the right ventricle is located laterally to the rest of the ventricular mass (septum and left ventricle), since the left segment forms part of the posterior epicardial wall of the left ventricle in its superior portion, encircling the mitral annulus, while the remainder is covered externally by the ascending segment.
In this layer (basal loop), stimulation progresses from the subepicardium to the subendocardium. This stimulation then extends to the descending segment, and at an average of 25.8 ms in our study, the ascending segment is activated. The termination of stimulation in the myocardium occurs at the terminal portion of the ascending segment, near its insertion into the cardiac fulcrum, during the first 80-100 ms of diastole, in the period traditionally known as the diastolic isovoluMETric phase, which we have more accurately termed PPMC [4].
Extensive knowledge of the helical myocardium explains that cardiac movements are sequential [71]. Similarly, cellular stimulation is illustrated in the diagram in (Figure 32). In the myocardium, actin and myosin are fundamental structural and contractile proteins in muscles, organized into sarcomeres to produce movement. Myosin (thick filament) uses energy from ATP to bind to and slide along actin (thin filament), causing muscle contraction and shortening the sarcomere. Tropomyosin and troponin are key regulatory proteins in the thin filaments of skeletal and cardiac muscle. Together they control contraction: tropomyosin blocks myosin from binding to actin at rest, while troponin, by binding to calcium, displaces tropomyosin to allow muscle contraction.
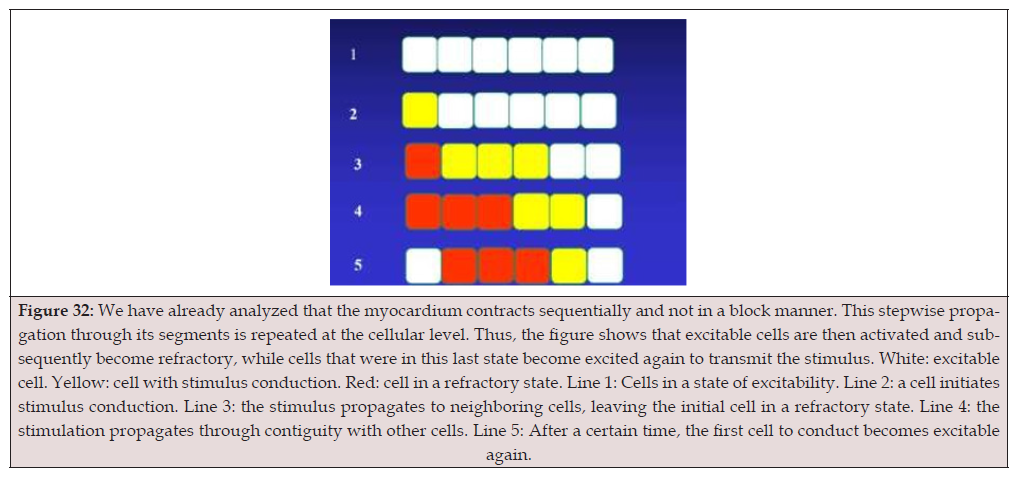
Figure 32:We have already analyzed that the myocardium contracts sequentially and not in a block manner. This stepwise propagation through its segments is repeated at the cellular level. Thus, the figure shows that excitable cells are then activated and subsequently become refractory, while cells that were in this last state become excited again to transmit the stimulus. White: excitable cell. Yellow: cell with stimulus conduction. Red: cell in a refractory state. Line 1: Cells in a state of excitability. Line 2: a cell initiates stimulus conduction. Line 3: the stimulus propagates to neighboring cells, leaving the initial cell in a refractory state. Line 4: the stimulation propagates through contiguity with other cells. Line 5: After a certain time, the first cell to conduct becomes excitable again.
This research clarifies the activation sequence of contractile areas and their integration into cardiac dynamics in relation to the path of the excitation wave, following a coordinated pattern according to the helical structure of the continuous myocardium. The MET study explains the torsional phase of the heart, defined as the opposing rotational movement of the base and apex. Activation, at the point where the descending and ascending segments cross, propagates from the endocardium to the epicardium (transverse propagation), that is, from the descending to the ascending segment. The study of impulse transmission through the myocardium led to the research presented here, which correlates the continuous and helical structure of the myocardium with the propagation of stimulation. Our analysis implies that diffusion occurs simultaneously longitudinally and transversely between the descending and ascending segments. We must find a relationship between the activation action and its mechanical product. The explanation lies in the simultaneous longitudinal and transverse conduction pathways of the electrical impulse.
The ventricular narrowing phase (isovolumetric systolic) at the beginning of systole is caused by the contraction of the right and left segments of the basal loop. The superimposed shortening phase is due to the descent of the base, coinciding with myocardial torsion. This originates longitudinally as the annulus contracts before the apex. The apex’s immobility is due to the mechanism of the base descending during systole and ascending during diastole. The pressure that generates the ejection of blood at the beginning of ejection, in a span that occupies only 20% of the systolic phase, is made possible by the ventricular torsion mechanism.
While there is a progression of electrical conduction along the continuous myocardium, this isolated activation does not explain the generation of a force capable of ejecting ventricular contents at a speed of 200 cm/s with low energy expenditure. This research found that transverse propagation from the descending to the ascending segment plays a fundamental role in ventricular torsion, allowing opposing forces on its longitudinal axis to generate the intraventricular pressure necessary for the abrupt expulsion of blood. This would produce a torsion mechanism similar to “wringing out a towel,” as described by Giovanni Borelli and Richard Lower [4].
Cardiac Self-Organization
At this stage of the research, we understood that the threedimensional spatial helix of the heart, in relation to a fourth dimension-the time of its cycle-implied that the relationship of the cardiac fulcrum with stimulation and the consequent myocardial torsion played an organizing role, as energy returns to that site after completing an 800 ms cycle that is repeated 110,000 times daily. During this journey through the myocardium, stimulation not only provides energy that is transformed into work and heat, but also accumulates information (negentropy). In this respect, entropy, not energy, is what allows us to evaluate the cost of functional existence. This recurrent journey to the electromechanical unit allows it to accumulate information to reconfigure the next cycle, given the interrelationship between the cardiac fulcrum and the AV node. This situation allows it to optimize data and deliver to the electromechanical unit the information and energy required for the efficiency of the next pulse [71-73]. In this regard, it is necessary to correlate the nature of the cardiac fulcrum- acting as an anatomical and functional attractor during the continuity of myocardial contraction (specifically, following aortic valve closure during the phase of pre-ejection myocardial contraction)- with the potential to accumulate information for the subsequent cycle.
The sensory organs in mammals filter an enormous amount of information from the outside world, which implies an organizational reality provided by the nervous system. This represents a mass of information that serves daily life. It also constitutes a factor of selective pressure [74] on biological behavior and also on human thought.
A fundamental point in this analysis is the interconnection between the AV node and the cardiac fulcrum. The latter acts as an attractor of the stimulus, which travels along the same myocardial circuit, originating and terminating in the myocardial fibers that insert into the fulcrum, the electromechanical unit. This concept is based on Henri Poincaré’s (1854-1912) recurrence theorem, which states that every dynamic system will eventually return to its initial state. This characteristic is found in stable systems, as it is invalid in unstable ones. The attractor is a point in the helical myocardium with minimal entropy production. It is worth asking whether this periodicity transmits information that originates and returns to the heart in variables such as amplitude, voltage, and frequency. The pulse width defines the energy transmitted to the muscle fiber. The wider the pulse, the more energy. This is called Pulse Width Modulation.
A logical question-consistent with current physics- is whether information is thus preserved for the process of continuous selforganization. This is known as the principle of unitarity, understood as the reversibility of the natural evolution of physical processes. Cardiac conduction can be represented as a self-generating dynamic system, since cardiac automaticity is the heart’s intrinsic capacity to produce rhythmic electrical impulses, but it also operates in a regime open to external influences and undergoes a process of self-organization. Information theory is useful here, as it is characterized by quantifying the information content of a sequence of biomolecules.
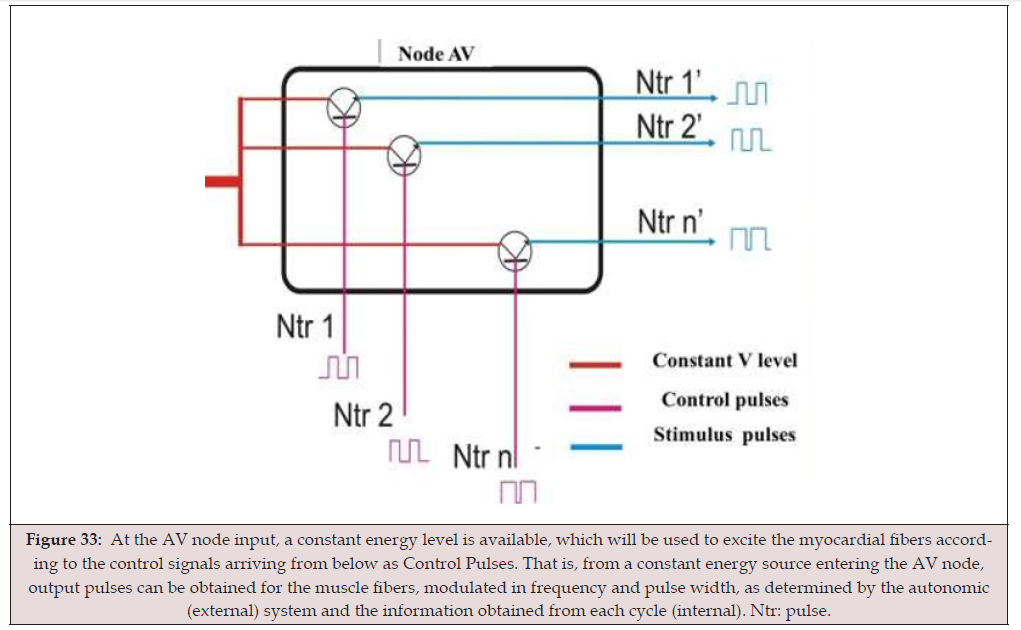
Figure 33:At the AV node input, a constant energy level is available, which will be used to excite the myocardial fibers according to the control signals arriving from below as Control Pulses. That is, from a constant energy source entering the AV node, output pulses can be obtained for the muscle fibers, modulated in frequency and pulse width, as determined by the autonomic (external) system and the information obtained from each cycle (internal). Ntr: pulse.
AV Node
The AV node receives the energy destined to stimulate the myocardial muscle fibers, as well as the control signals derived from this energy. The AV node receives a constant level of energy, which is used to excite the muscle fibers via neurotransmitters. To generate the output impulses from the AV node that reach the muscle fibers, control pulses are required, which respond to the Central Autonomic Nervous System (Figure 33). Each subsystem owns its own process and can modify it, positively impacting it and thus reducing the disorder inherent in any activity or process. Shannon’s information theory (2) is applicable here (Figure 33):
S = k (Pa Log2 (1/Pa) + Pb Log2 (1/Pb) + Pc Log2 (1/Pc) + Pd Log2 (1/Pd))
Where Pa, Pb, Pc, and Pd are the probabilities of occurrence of events with decreasing qualities, with “a” being the optimal quality and “d” the inferior one. If the standard allows for the existence of all four probabilities, the resulting S1 will be greater than the S2 that would result from eliminating the worst qualities, leaving only “a”.
In the case of the heart’s self-organization, the local subsystem (AV node) appears to be both cause and effect, a situation ensured by the cyclical feedback that allows it to reorganize and improve its management according to the body’s needs. This process incorporates information and energy (negentropy). In other words, from a constant energy source entering the AV node, output pulses can be generated to the muscle fibers, modulated in frequency and pulse width, as determined by the autonomic nervous system (external) and the information obtained from each cardiac cycle (internal). In myocardial stimulation, there is a sequential property of the myocardium, which is repetitive. This creates a link between this property of excitation, frequency, and energy, resulting in the continuous events of cardiac cycle stimulation. In complex organisms, there is the possibility of information selection [75]. This concept implies what would be a considerable challenge: verifying the energy (or voltage) levels that reach the AV node. It also involves verifying the control pulse trains and, consequently, the stimulus pulse trains.
The electromechanical unit would function by controlling the current flow between its terminals (emitter, base, and collector) in a manner analogous to a transistor (an invention of physicists John Bardeen, Walter Brattain, and William Shockley at Bell Laboratories in december 1947). In this way, the electromechanical unit would have a programming plan for the next cardiac cycle, receiving information from external sources (the nervous system) as well as from its own myocardial function (voltage, amplitude, and frequency) in a self-organizing process. This concept would explain the fundamental question posed earlier in this article: if the QRS complex normally lasts around 100 ms, why does the mechanical contraction of the myocardium reach 400 ms? The AV node would have an organizing pattern for the next cycle, which would be modified by receiving information from outside the heart, but also derived from its own functioning through a self-organizing process. Recall that the cardiac coil returns with its stimulation to the same electromechanical unit from which it originated. This would explain the different duration of the electrocardiographic QRS in relation to the mechanical contraction.
The physiology of myocardial stimulation, with its consequent torsion-detorsion, implies recognizing the AV node and fulcrum as subject to negentropy, which is the process of creating and maintaining order within a system, acting as the opposite of entropy, the natural tendency toward disorder. It manifests as the capacity of systems (natural, living, or even social and economic) to organize, innovate, and self-regulate, using energy or information from the outside to maintain stability and complexity.
The AV node, interconnected with the cardiac fulcrum, acts as a subsystem receiving information from the central nervous system (external) and from the myocardium itself (internal). This information allows for negentropy, maintaining the organizational system of cardiac stimulation from equilibrium and preventing it from reaching a final equilibrium. This anti-entropic state, or negentropy, is fueled by external input, that is, by the exchange with the environment, and by the information produced by the temporal pathway of the stimulus through the continuous myocardium. This pathway, when directed to an attractor (electromechanical unit), allows for the reorganization of the system. It is important to remember that the intrinsic activity of the system is the determining factor in its relationship with the environment.
Faraday and Maxwell potentials are important in these fields. In the heart, there are energy fields resulting from vortical electrical flows, which are coupled to information fields [24]. Studies have confirmed the interrelationship between ECG patterns and the brain (Rein’s resonance hypothesis). The heart generates energy as described by Russek and Schwartz (1996). This energy is coupled to the information field. In this way, the heart and brain process information [76, 77]. It is essential to understand a key phrase uttered by Erwin Schrödinger (1887-1961): “We must go to the small”. These words summarize the essence of the contribution of quantum mechanics. Schrödinger understood that to comprehend the true nature of matter, it is not enough to observe the macroscopic world; it is necessary to delve into the behavior of atoms and subatomic particles. The metabolism of living beings involves the simultaneous construction of biological molecules and the breakdown of other molecules.
These concepts are consistent with that of syntropy, investigated by Luigi Fantappiè, understood as a measure of the degree of internal organization of any system composed of interacting components. In this concept, he details that phenomena produced by past causes adhere to the second law of thermodynamics. Therefore, energy dissipates, order is lost, and structures are destroyed, while future phenomena (syntropy) tend toward the reorganization of the system. Syntropy was referred to in 1974 as “negative entropy” (negentropy) by Albert Szent- Györgyi. According to these developments, the heart appears to have the property of connecting the organism to itself and to its environment. In 1959, Léon Brillouin combined Shannon’s informational entropy with Boltzmann’s statistical entropy, stating that information is negentropic and can cancel entropy. This has applications in molecular biology and thermodynamic processes.
In the cardiac cycle, adaptation to physiological needs, through a continuously monitored program, allows for the surveillance and function of the system. To clarify: with a cycle duration of less than one second, without this predictable pattern of behavior through the QRS complex, the system would be subject to instability given its frequency of 110,000 cycles/day with a duration of 800 ms. This frequency data indicates that it lacks the time available to readjust its program. The nervous system influences the activity of various organs (digestive system, skin, etc.), but unlike other systems, such as the nervous system, which can have a prolonged pause before mounting the necessary response, the heart, with its limited time frame, would place the organism at risk of death if it did not have a rapid response. Each heartbeat is an event, and in this event, time is the driving force. Thus, we can speak of the equation: myocardial activation (three-dimensional)–time (understood as a fourth dimension). This equation gives relevance to the event of our present.
This situation was noted by William Harvey (1578-1657), who recounts the difficulties in proving his theory of blood circulation: “I came to think, [he says] with Fracastoro, [Renaissance epidemiologist], that the movement of the heart could only be known by God” [60].
Given this high frequency and energy output [78-88], the cardiac system constantly receives feedback, modifying its precontraction program through the electromechanical unit (Cardiac Fulcrum + AV Node). This unit gathers information from its operating circuit, originating and terminating there, and also receives the influence of other bodily systems. The evolution of biology through its significant stages have determined the need for continuous information processing by organisms. This continuous adaptation throughout the life of the cardiac system to fulfill its function explains the difference in duration between the QRS complex (100 ms), the system’s program, and the myocardial contraction, its consequence, systole + PPMC, lasting 400 ms, as well as the activation-time equation.
The ultimate goal of medical knowledge is to understand disease processes. In this respect, and in relation to the research presented here, Takotsubo cardiomyopathy is a condition that highlights the relationship between emotions and cardiac function. It is also known as “stress cardiomyopathy,” “transient apical dysfunction,” or “broken heart syndrome.” It is usually triggered after an episode of intense and unexpected emotional stress, which causes an excessive release of catecholamines (adrenaline, noradrenaline, and dopamine) and leads to an acute coronary syndrome with STsegment elevation, but without evidence of obstructive coronary lesions or coronary artery spasm. Transthoracic echocardiography reveals apical akinesis of the left ventricle with basal hypercontractility (apical ballooning). These transient regional alterations in ventricular wall motion completely resolve within a few days. Cardiac catheterization confirms the absence of coronary artery disease. The explanation for this syndrome is based on the role of catecholamines produced by unexpected stress or trauma. These catecholamines play a role in the interaction between the brain’s cognitive centers and the hypothalamic-pituitary-adrenal axis in the stress response.
The main effects of their increase include elevated heart rate, hypertension, and increased cardiac output due to the effects of epinephrine and norepinephrine, greater blood flow to vital organs, increased release of glucose and fatty acids for rapid energy, increased muscle strength, and enhanced mental acuity. This type of response is a physiological response to physical or emotional stress that produces a kind of “fight or flight” response. Although sympathetic stimulation appears to be the cause of excess catecholamines, the mechanism by which myocardial muscle dysfunction occurs is not fully understood [89,90]. Ultimately, the aim is to make the nature of this response understandable. The question this synopsis raises are: what role does the electromechanical unit play in this condition of emotional origin?
Conclusions
The interaction between the cardiac fulcrum and the AV node (electromechanical unit) in relation to the double-helix muscular circuit of the myocardium, which begins and ends at this fulcrum [89], is likened to a system composed of basic elements with an organization based on the reception, feedback, and transmission of information. Allegorically, we can say: stimulation tells the myocardium how to twist, and the myocardium informs the stimulation how to form the next pulse. This collected information has the capacity for negentropic regulation, since it reduces the amount of uncertainty and degradation (entropy), allowing the system to self-organize in making decisions for the next cycle. This is because different alternatives may arise due to physiological needs, understanding that entropy is the price of the material development of the universe [91-93].
It is necessary to incorporate the advances of current quantum physics into the study of living beings. This step should not be seen as esoteric or mystical, but rather as the use of information held by other sciences in order to achieve negentropy, thus advancing biological knowledge. The path of depolarization energy in our research leads to the understanding that the stimulation circuit is completed at its origin, in the electromechanical unit. We believe that these contributions, based on the electromechanical unit, design it as an attractor of the helical convolution that establishes the path of the myocardium. The myocardium, being the only muscle that originates and terminates at the same point (the cardiac fulcrum), analogous to a Möbius strip, combined with the understanding of the QRS complex as a continuous information pattern for achieving sequential cardiac mechanics through the negentropic effect, and the evidence of the time factor as a fundamental element in a four-dimensional myocardium, are essential for understanding cardiac physiology. Without this adherence to the timing factor in each cardiac cycle, life would not be possible, this characteristic being unique in its brevity within the organs of the human body. Undoubtedly, the heart is subject to the rigor of time as a fundamental element of its continuous function, since any delay in its cycle carries the possibility of imminent death.
The myocardium is an integrable system, consistent with electromagnetic resonance, in a continuous feedback loop within a time limit for successive phases of contraction and expansion. There is a stimulation plan to achieve myocardial activation. It’s important to remember that in humans, a programmed cell begins its beat at three weeks of gestation, giving rise to the cardiac mantle. Similarly, in cardiac arrest due to surgery with cardiopulmonary bypass or accidentally, an external electrical shock restarts it. This programming would have as its epicenter the electromechanical unit (AV node + cardiac fulcrum) with a continuous development of muscular contraction in the myocardium, which, with the information gathered (frequency, voltage, amplitude), allows for the next pulse. This characteristic explains the different duration between the QRS complex (100 ms) and the myocardial contraction (systole + PPMC, 400 ms). Without this self-organization, the cardiac cycle would be subject to instability given the short duration of the cardiac cycle of 800 ms. In this way, the heart would not only be subject to external fluctuations in connection with the central nervous system, but also to an internal organizing process that provides it with information management that does not deviate from the required homeostasis.
During this research, in both human and other species’ hearts, histological studies revealed that the fulcrum (the beginning and end of the continuous myocardium) is adjacent to the AV node, creating a space rich in plexuses with interconnected neurofilaments between the two structures. The crucial finding of this research is that these neurofilaments invade the myocardium originating at the cardiac fulcrum, thus forming an electromechanical unit.
We performed a mapping of left ventricular activation on its endocavitary and epicardial surfaces according to the described methodology. The mapping was performed simultaneously with the surface ECG. This provided a unified temporal frame of reference, allowing us to correlate both recordings and obtain a synchronized view of the simultaneous activation observed in various electro anatomical views.
This research established the structural relationship between myocardial stimulation and its mechanical product, based on the assumption that this electromechanical unit is undergoing a continuous process of self-organization. The mechanical consequence of the initiation of stimulation in the anatomical and functional unit between the AV node and the cardiac fulcrum, and the continuity of myocardial activation to the anisotropic zone at the contiguity between the descending and ascending segments, is what generates, through sequential opposition of movements, the torsion of the left ventricular myocardium by opposing rotation between the base and the apex with simultaneous shortening of both ventricles.
In summary, cardiac movements follow three units (Figure 1):
1) Energy unit. Composed of the AV node.
2) Electromechanical unit. Located at the cardiac fulcrum where
the neurofilaments interact with the myocardium.
3) Torsion/detorsion unit. Occurs at the level where energy is
transferred from the descending to the ascending segment,
achieving myocardial torsion (systole) and subsequent
detorsion that allows ventricular suction.
Ultimately, given the interconnectedness of the four fundamental cardiac subsystems — anatomy, stimulation, energy (glucose and fatty acid metabolism), and mechanics- cardiac function constitutes a unified whole. This state is not merely the sum of the four constituent subsystems; rather, this interconnectedness means that cardiac function inevitably relates to the system as a whole, implying that the subsystems are intertwined and subject to continuous reorganization.
Acknowledgements
None.
Conflict of Interest
None.
References
- Medawar PB (1973) The Hopo of Progress. Doubleday, New York.
- Trainini JC (2023) El Compromiso Médico con el factor Humano. Biblos Ed, Buenos Aires.
- Trainini J, Lowenstein J, Beraudo M, Mora Llabata V, Carreras Costa F, et al. (2022) “El corazón helicoidal. Fulcro y Torsion”. UNDAV Ed, Buenos Aires. Argentina.
- Trainini J, Lowenstein J, Beraudo M, Valle Cabezas J, Wernicke M, et al. (2023) “Anatomy and organization of the helical heart”. UNDAV Ed Buenos Aires.
- Rushmer RF, Crystal DK, Wagner C (1953) The functional anatomy of ventricular contraction. Circ Res 1(2): 162-170.
- Rushmer RF (1964) Initial ventricular impulse. A potential key to cardiac evaluation. Circulation 29: 268-283.
- Rushmer RF (1972) Structure and Function of the Cardiovascular System. Philadelphia.
- Trainini J, Beraudo M, Wernicke M, Trainini A (2026) “The Cardiac Fulcrum”. E-book, Editorial Biblos, Buenos Aires.
- Trainini J, Beraudo M, Wernicke M, Trainini A (2026) “The Cardiac Fulcrum”. The Journal of Anatomy. February 15(1).
- Karamchandani JR, Nielsen TO, van de Rijn M, West RB (2012) Sox10 and S100 in the diagnosis of soft-tissue neoplasms. Appl Immunohistochem Mol Morphol 20(5): 445-450.
- Trainini J, Beraudo M, Wernicke M, Trainini A, Lowenstein J, et al. (2021) Myocardial Torsion and Cardiac Fulcrum. J Morphol Anat S1: 001.
- Trainini JC, Beraudo M, Wernicke M, Carreras Costa F, Trainini AM, et al. (2022) Evidence that the myocardium is a continuous helical muscle with one insertion. REC: CardioClinics 57: 194-202.
- Ortega D, Logarzo E, Barja L, Paolucci A, Mangani N, et al. (2020) Novel implant technique for septal pacing. A noninvasive approach to nonselective his bundle pacing. Journal of Electrocardiology 63: 35-40.
- Sosa E, Scanavacca M, D’Avila A, Pilleggi F (1996) “A new technique to perform epicardial mapping in the electrophysiology laboratory”. J Cardiovasc Electrophysiol 7: 531-536.
- Trainini JC, Herreros J (2019) “El explorador del corazón: biografía de Francisco Torrent Guasp”. Biblos, Buenos Aires.
- Trainini JC, Elencwajg B, López Cabanillas N, Herreros J, Lago N, et al. (2015) Electrical Propagation in the Mechanisms of Torsion and Suction in a Three-phase. Rev Argent Cardiol 83(5): 416-428.
- Trainini JC, Elencwajg B, López Cabanillas N, Herreros J, Lago N, et al. (2015) Stimuli popagation, muscle torsión and cardiac suction effect through electrophysiological research. In “Basis of the New Cardiac Mechanics. The Suction Pump” Trainini JC and col. Lumen, Bs. As, 39-61.
- Trainini JC, Elencwajg B, López-Cabanillas N, Herreros J, Lago N. Lowenstein JA (2015) Propagación eléctrica en los mecanismos de torsión y succión en un corazón de tres tiempos. Rev Argent Cardiol 83(5): 420-428.
- Trainini JC, Herreros J, Elencwajg B, López Cabanillas N, Lago N, et al. (2015) “Fundamentos de la Nueva Mecánica Cardí La Bomba de Succión”. Ed UCAM; Murcia, España.
- Trainini JC, Elencwajg B, López Cabanillas N, Herreros J, Lago N (2015) Electrophysiological Basis of Torsión and Suction in the Continuous Cardiac Band Model. Anat Physiol 5: S4-001.
- Trainini JC, Elencwajg B, López Cabanillas N, Herreros J, Lago N (2015) Ventricular torsion and cardiac suction effect. The electrophysiological analysis of the cardiac muscle. J Clin Exp Cardiolog 6:10.
- Trainini JC, Elencwajg B, López Cabanillas N, Herreros J, Lago N, et al. (2016) Activación electrofisiológica y tiempos de propagación en la banda muscular ventricular. Primer estudio mundial en seres humanos. Rev Arg Cardiol 84: 475-478.
- James TN, Sherf L (1971) Specialized tissue and preferential conduction in the atria of the heart. Am J Cardiol 28(4). 414-427.
- Trainini J, Beraudo M, Wernicke M, Trainini A, Lowenstein J, et al. (2025) “El Fulcro Cardíaco en la Fisiología del Corazón Helicoidal”. Editorial Biblos, Buenos Aires.
- Trainini J, Beraudo M, Wernicke M, Trainini A, Elencwajg B, et al. (2025) The Three Electromechanical Units of the Myocardium. Am J Biomed Sci Res 29(1): 61-75.
- Trainini J, Lopez Santoro R, Wernicke M, Beraudo M, Trainini A, et al. (2025) “Hypothesis on the self-organizing process in the function of the helical myocardium”. Am J Biomed Sci Res 29 (3): 476-489.
- Trainini J, Wernicke M, Beraudo M, Trainini A, Hernández López MP, et al. (2026) Clinical and Experimental Research on Negative Intraventricular Pressure. Contributions to the Pathophysiology of Heart Failure with Preserved Ejection Fraction. Am J Biomed Sci Res 30(1).
- Prigogine I (1984) “Order out of chaos: man´s new dialogue with nature”. Bantam, New York.
- Eddington AS (1957) “The mathematics theory of relativity”. Cambridge University Press, Cambridge.
- Trainini JC (2003) Hacia la necesidad de un nuevo paradigma mé Rev Argent Cardiol 71: 439-445.
- Carli A (2017) “Dialéctica de la salud y la enfermedad”. Ed. Biblos, Buenos Aires.
- Sánchez Guillén J (2009) “L.E. Boltzmann”. Prensas Universitarias de Zaragoza, Españ
- Prigogine I, Stengers I (1991) Entre el tiempo y la eternidad. Buenos Aires, Alianza Ed.
- Bertalanffy von L (1978) Teoría general de los sistemas. Alianza, Buenos Aires.
- Bateson G (1979) Mind and nature: a necessary unity. Dutton, New York.
- Satemband MJ (1994) “Entre el orden y el caos. La complejidad”. Buenos Aires, Fondo de Cultura Econó
- Morris R (1987) “Las flechas del tiempo”. Biblioteca Científica Salvat, Barcelona.
- Capra F (1992) “El tao de la física”. Luis Cárcamo Ed, Madrid.
- Trainini JC (2004) Modelo termodinámico en la regeneración cardiaca. Rev Conarec 74: 59-64.
- Eigen M, Schuster P (1979) “The hypercicle: a principle of natural self-organization”. Nueva York.
- Calzetta E (2009) “Entropía”. Ministerio de Educación de la Nación, Buenos Aires.
- Hoyle F (1970) “Frontiers of astronomy”. Heinemann, Londres.
- Trainini JC, Biscioni C, Romanelli L, Needleman C, Carli A, et al. (2008) Medicina Basada en la Complejidad. Estudio Sigma, Buenos Aires.
- Ordoñez J (1986) “Boltzmann. Escritos de mecánica y termodiná Alianza Editorial, Madrid.
- Nicolis G, Prigogine I (1977) Self-organization in non-equilibrium systems. Whiley Interscience, Nueva York.
- Schrödinger E (1955) The interpretation of quantum mechanics: Dublin Seminars (1949-1955) and other unpublished essays. Ox Box Press, Woodbridge.
- Bohm D (1951) Teoría cuá Prentille-Hall, New York.
- Wheeler J A, Mehra J (1973) The physicist’s conception of nature. Holanda.
- Morin E (2011) Los siete saberes necesarios para la educación del futuro. Nueva Visión, Buenos Aires.
- Dossey L (1986) Tiempo, espacio y medicina. Ed. Kairós, Barcelona.
- Simpson PK (1990) Artificial neural systems.Pergamon Press, New York.
- Einstein A, Podolsky B, Rose N (1935) Can quantum mechanical description of reality be considered complete. Physical Review 47: 777-778.
- Stapp HS (1971) Correlation experiments and the nonvalidity of ordinary ideas about the physical world. Physical Review: D3 1303.
- Engel GL (1977) The need for a new medical model: a challenge for biomedicine. Science 196(4286): 129-136.
- Trainini JC (2020) Humanización en la práctica mé Educ Med 21(2): 65-66.
- Bohr N (1958) Atomic physics and human knowledge. Nueva York.
- Trainini J (2019) Ser y humanismo. Editorial Biblos, Buenos Aires.
- Schrödinger E (1955) The interpretation of quantum mechanics: Dublin Seminars (1949-1955) and other unpublished essays. Ox Box Press, Woodbridge.
- Martinez Fernández J (2005) El concepto de lenguaje universal. Quaderns de filosofia i ciéncia 35: 7-18.
- Trainini J, Trainini A (2025) “La Circulación de la Sangre”. Ed. Biblos, Buenos Aires.
- Torrent Guasp F (1998) Estructura y función del corazó Rev Esp Cardiol 51: 91-102.
- Best A, Egerbacher M, Swaine S, Pérez W, Alibhai A, Rutland P, et al. (2022) Anatomy, histology, development and functions of Ossa cordis: A review. Anat Histol Embryol 51(6): 1-13.
- Buckberg GD, Coghlan HC, Torrent Guasp F (2001) The structure and function of the helical heart and its buttress wrapping. V. Anatomic and physiologic considerations in the healthy and failing heart. Sem Thorac Cardiovasc Surg 13(4): 358-385.
- Cosín Aguilar J, Hernándiz Martínez A, Tuzón Segarra MT, Agüero Ramón Llin J, et al. (2009) Estudio experimental de la llamada fase de relajación isovolumétrica del ventrículo izquierdo. Rev Esp Cardiol 62: 392-399.
- Valle J, Herreros J, Trainini J, García Jimenez E, Talents M (2017) Three-dimensional definition of Torrent Guasps ventricular muscle band and its correlation with electric activation of the left ventricle (abstract). XXIII Congreso SEIQ, Madrid, España BJS.
- Trainini JC, Wernicke M, Beraudo M, Lowenstein J, Trainini A, et al. (2021) Hyaluronic acid in the heart. J Trends Biomedical Research 4(1).
- Trainini J, Beraudo M, Wernicke M, Carreras Costa F, Trainini A, et al. (2022) The hyaluronic acid in intramyocardial sliding. REC: CardioClinics.
- Rodríguez Padilla J, Petras A, Magat J, Bayer J, Bihan Poudec Y, et al. (2022) Impact of intraventricular septal fiber orientation on cardiac electromechanical function. Am J Physiol Heart Circ Physiol 322(6): H936-H952.
- Trainini JC, Lowenstein J, Beraudo M, Trainini A, Mora Llabata V (2019) Ed Biblos, Buenos Aires; Argentina.
- Armour JA, Randall WC (1970) Structural basis for cardiac function. Am J Physiol 218(6): 1517-1523.
- Trainini J, Wernicke M, Beraudo M, Cohen M, Trainini A, et al. (2023) Cardiac Fulcrum, its Relationship with the Atrioventricular Node. Rev Argent Cardiol 91: 429-435.
- Trainini J, Beraudo M, Wernicke M, Trainini A, Lowenstein J, et al. (2024) Fundamental Conclusions on Research into the Anatomy and Organization of the Helical Heart. Am J Biomed Sci Res 23(5).
- Trainini J, Beraudo M, Wernicke M, Trainini A, Cohen M, et al. (2024) Relationship of the cardiac fulcrum and the AV node with ventricular torsion. Am J Biomed Sci Res 24(2).
- Jerison HJ (1973) Evolution of the Brain and Intelligence. Academic Press, Nueva York.
- Mayr E (1964) The Evolution of Living Systems. Proc Nat Acad Sci 51(5): 934-941.
- Trainini J (2024) En busca del fulcro cardí El hallazgo del soporte del corazón. Ed. Biblos, Buenos Aires, Argentina.
- Ballester-Rodés M, Carreras F, Narula J, Oschman JL (2016) A New Look at the T Wave. Fluid Mech Open Acc 3: 128.
- Arvidsson M, Töger J, Carlsson M, Steding Ehrenborg K, Pedrizzetti G, et al. (2017) Left and right ventricular hemodynamic forces in healthy volunteers and elite athletes assessed with 4D flow magnetic resonance imaging. Am J Physiol Heart Circ Physiol 312(2): H314-H328.
- Carreras F, Ballester M, Pujadas S, Leta R, Pons Lladó G (2006) Morphological and functional evidences of the helical heart from non-invasive cardiac imaging. Eur J Cardiothoracic Surg 29(Suppl 1): S50-S55.
- Henson RE, Song SK, Pastorek JS, Ackerman JH, Lorenz CH (2000) Left ventricular torsion is equal mice and humans. Am J Physiol Heart Circu Physiol 278: H1117-H1123.
- Maksuti E, Carlsson M, Arheden H, Kovács S, Broomé M, et al. (2017) Hydraulic forces contribute to left ventricular diastolic filling. Scientif reports 7: 43505.
- Pedrizzetti G, Arvidsson PM, Töger J, Borgquist R, Domenichini F, et al. (2017) On estimating intraventricular hemodymamic forces from endocardial dynamics: A comparative study with 4D flow MRI. J Biomech 60: 203-210.
- Poveda F, Gil D, Martí E, Andaluz A, Ballester M (2013) Estudio tractográfico de la anatomía helicoidal del miocardio ventricular mediante resonancia magnética por tensor de difusió Rev Esp Cardiol 66: 782-790.
- Trainini JC, Trainini A, Valle Cabezas J, Cabo J (2019) Left Ventricular Suction in Right Ventricular Dysfunction. EC Cardiology 6: 572-577.
- Ballester M, Ferreira A, Carreras F (2008) The myocardial band. Heart Fail Clin 4(3): 261-272.
- Mora V, Roldán I. Romero E, Saurí A, Romero D, et al. (2018) Myocardial contraction during the diastolic isovolumetric period: analysis of longitudinal strain by means of speckle tracking echocardiography. J Cardiovasc Dev Dis 5(3): 41.
- Mora V, Roldán I, Bertolín J, Faga V, Pérez-Gil M, et al. (2021) Influence of ventricular wringing in the preservation of left ventricle ejection fraction in cardiac amyloidosis. J Am Soc Echocardiog 34(4): 767-774.
- Torrent Guasp F, Buckberg G, Carmine C, Cox J, Coghlan H, et al. (2001) The structure and function of the helical heart and its buttress wrapping .IV. The normal macroscopic structure of the heart. Seminars in Thorac and Cardiovasc Surg 13: 301-319.
- Oschman JL, Oschman NH (2015) The Heart as a Bi-directional Scalar Field Antenna. J Vortex Sci Technol 2: 121.
- Zazueta Armenta V, González Orozco JA, Ornelas Aguirre JM, Félix Córdova JA (2023) Características clínicas del síndrome de Takotsubo: una serie de casos. Arch Cardiol Mex 93(2): 203-211.
- Thomas L (1979) The Medusa and the Snail. The Viking Press, Nueva York.
- Basilico F (2025) El corazón y el campo cuantico. Ed del autor, Buenos Aires.
- Herrero E, Trainini J, Hernández López MP, Lowenstein J (2026) Cardiac Fulcrum: Its Relationship with Two-dimensional Echocardiography. Rev Argent Cardiol 94: 195-202.




 We use cookies to ensure you get the best experience on our website.