
Review Article 
 Creative Commons, CC-BY
Characterization of Non-Tuberculous Mycobacteria Pathogenic Species in Mali Using Genotype Mycobacterium Cm/As and 16s Sequencing during Tuberculosis Diagnosis or Treatment Follow-Up
*Corresponding author:Aissata Boubakar Cisse, Laboratory and Biomedical Research Department, National Institute of Public Health, Bamako, Mali.
Received:July 03, 2025; Published:July 14, 2025
DOI: 10.34297/AJBSR.2025.27.003600
Abstract
Introduction: Non-Tuberculous Mycobacteria (NTM) are environmental mycobacteria, some of which can cause pulmonary or extrapulmonary
disease. We aimed to characterize species identified in our laboratory from suspected samples between 2009 and
2023.
Methods: We conducted a cross-sectional study between 2009 and 2023 at the National Institute of Public Health in Mali using clinical
specimens positive for Acid-Fast Bacilli (AFB) in microscopy and negative by Xpert MTB/RIF and positive culture which were
negative to MPT64 protein. The 16S nested PCR, was performed at the Institute of Tropical Medicine (ITM) in Antwerp, Belgium
followed by Sanger sequencing at BaseClear (BE Leiden, The Netherlands) for 16S-positive amplicons. The Line Probe Assays (LPAs)
GenoType Mycobacterium CM and AS VER 2.0 were realized from liquid or solid cultures at the National Reference Laboratory at the
National Institute of Public Health in Mali.
Results: Clinical samples from 155 patients suspected of TB or drug resistance TB naive of treatment or during monitoring including
80 clinical samples and 75 positive cultures. Of these, 122 were NTM-positive results of which 47 were clinical samples and 75
cultures. 16S-PCR was positive for 47 (59%) of the 80 clinical samples and 71 (98,6%) of the 72 cultures. Sequencing was performed
on 118 positive amplicons and LPA on 51 cultures. M. Avium Complex (MAC) was detected in nearly half (47%; 57/122), followed by
M. simiae (13.1%), M. fortuitum (7.4%) and M. abscessus (4.9%).
Conclusion: A significant proportion of NTM identified in our patients, during TB diagnosis or treatment monitoring were potentially
pathogenic species. The introduction and use of molecular platforms enabling differential detection of mycobacterial species will
provide an opportunity for better management of TB and NTM diseases.
Keywords:GeneXpert, LPA, NTM, TB, Sequencing, 16S gene
Introduction
Non-Tuberculous Mycobacteria (NTM), also named atypical mycobacteria or mycobacteria other than Mycobacterium Tuberculosis Complex (MTBC) and Mycobacterium leprae, are environmental mycobacteria that can infect humans and animals [1]. Despite being ubiquitous, some of them are officially recognized as responsible for pulmonary or extrapulmonary diseases [2]. Although NTM and MTBC are different species, they all appear as Acid-Fast Bacilli (AFB) on microscopy. This property can lead to misdiagnosis, particularly in countries with limited resources where rapid molecular diagnostic tests or culture are not routinely available for all patients. In a previous study in our laboratory, 8.6% of AFB-positive patients were negative to Xpert MTB/RIF and 3.4% were carrying an NTM [3]. Unlike tuberculosis, there is no standardized treatment regimen against NTM diseases. They are treated with commonly used antibiotics combined with some antibiotics used against tuberculosis [1]. Before initiating treatment, the disease must be established based on clinical, radiological and microbiological criteria, including identification of the species to establish its pathogenicity [2]. The use of molecular methods, which are more specific than microscopy and faster than culture, has improved the rate of detection and identification of mycobacteria species. The 16S ribosomal RNA gene, present in all micro-organisms, is highly conserved and evolves slowly, making it a unique target that is widely used for phylogenetic studies of prokaryotes [4]. The 23S gene is also used to characterize mycobacteria, for example in LPAs [5]. Currently, more than 200 NTM species are officially recognized [6], with only a few, identified as pathogenic for humans [2]. Mycobacterium Avium Complex (MAC) sub-species are the most frequently detected across various geographic areas [7-16] and along with the generally non-pathogenic M. terrae complex are the best-studied NTM species [17]. Other important species of NTM are M. abscessus, M. celatum, M. fortuitum, M. kansasii, M. marinum, M. simiae and M. smegmatis [17]. In this study, we characterized the NTM species detected from 2009 to 2023 at the National Reference Laboratory for Tuberculosis (NRL) in Bamako, Mali, using the GenoType Mycobacterium CM/AS and Sanger sequencing of the 16S gene.
Materials and Methods
Study Design
A cross-sectional study was designed to characterize NTM species detected at the NRL from samples collected between 2009 and 2023. We included patients of any age who were referred by TB diagnostic and treatment centres across the country for TB diagnosis, or suspicion of drug-resistant TB during TB treatment monitoring. Socio-demographic and clinical data were collected from the laboratory registers and medical records. Species were identified from clinical specimens (sputum, gastric fluid, pleural fluid, and pus), or from liquid or solid culture, either freshly isolated (n=45) or retrieved from the laboratory’s strain bank at -80°C (n=30). For this study, we selected clinical specimens that were positive at microscopy and negative for GeneXpert MTB/RIF, and cultures that were negative by the MPT64 (75) assay
Identification by Sanger Sequencing Method
The nested 16S-PCR, was performed at the Institute of Tropical Medicine (ITM) in Antwerp, Belgium, using the primers depicted in table 1, for the 72 out of 75 cultures and all the 80 clinical specimens (microscopy+/Xpert negative) collected during the first round of the national drug resistance TB survey (Table 1).
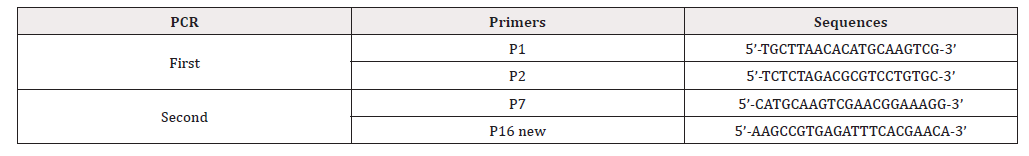
Table 1:Primers for 16S nested PCR to detect NTM.
Sanger sequencing was performed at BaseClear (BE Leiden, The Netherlands), using the 16S- positive amplicons. The obtained sequences were uploaded in the Basic Local Alignment Search Tool (BLAST) of the National Centre for Biotechnology Information (NCBI) for comparison to reference strain sequences.
LPA Identification
The GenoType Mycobacterium CM/AS VER 2.0 was performed at the NRL using liquid or solid cultures according to the manufacturer’s recommendations [18]. Prior to the amplification, DNA was extracted from colonies by heat shock (95°C for 20 minutes, followed by 10 minutes in an ice bath). When the species could not be identified with the GenoType CM kit, we repeated the hybridization with the GenoType Mycobacterium AS [19].
Data Analysis
The data was recorded in Excel (Version 2020) and the percentages were calculated by crosstab, while p-values and odds ratios with 95% confidence intervals were generated using analysis in IBM SPSS Statistics.
Ethical Issues
Information on the patient’s name and address was removed from the data and each patient was identified by a unique identification number. Informed consent was not required from patients seen routinely in the laboratory outside studies, yet patients were informed that other tests, in addition to those requested by the prescriber, would be performed to identify the detected bacilli. The study was approved by the Ethics committee of the National Institute of Research in Public Health under the number N° 08/2018/ CE-INRSP.
Results
Detection and Characterization of NTM Species
In total, sample of 155 different patients were tested including 80 clinical samples and 75 positive cultures including 30 from laboratory biobank. Of these, 125 were AFB positive and Xpert/MTB not detected and in which, NTM species were detected in 92 (73,6%) (Figure 1). A total of 122 patients were carriers of NTM species, 47 from clinical samples including 2 extrapulmonary (pus and pleural fluid) and 120 pulmonary (117 sputum and 3 gastric fluids), 45 from fresh cultures and 30 from laboratory biobank. Among these patients, 54 (44.3%) were previously treated for TB and 68 (55.7%) were newly diagnosed patients.
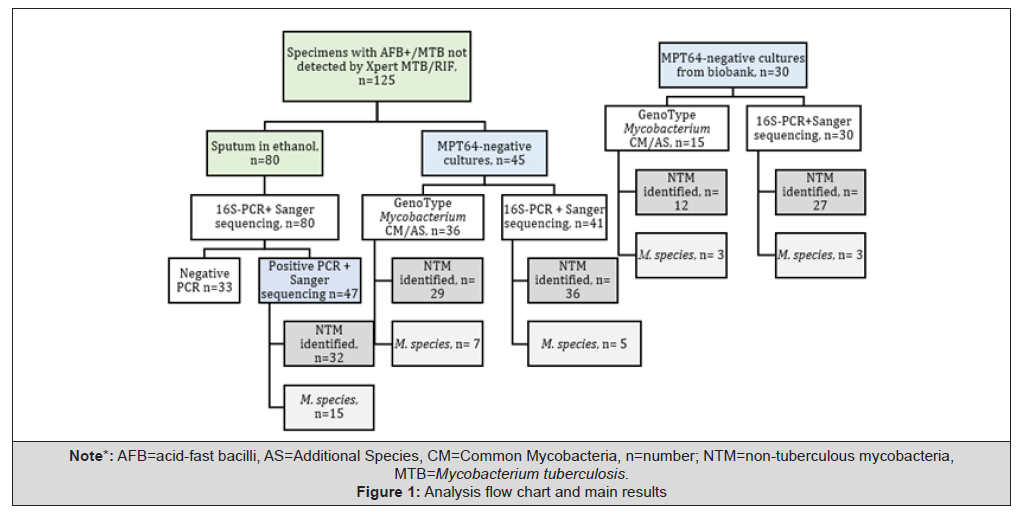
Note*:AFB=acid-fast bacilli, AS=Additional Species, CM=Common Mycobacteria, n=number; NTM=non-tuberculous mycobacteria, MTB=Mycobacterium tuberculosis.
Figure 1:Analysis flow chart and main results
Male patients were predominant with 63.1% and the average age was 50±15,2 years with extremes of 21 and 86 (Table 2). The over-50 years age group represented 51.6% of patients. Sputum samples represented 95.9% of the treated specimens. HIV status was known for 64 patients of which 15.6% were positive.
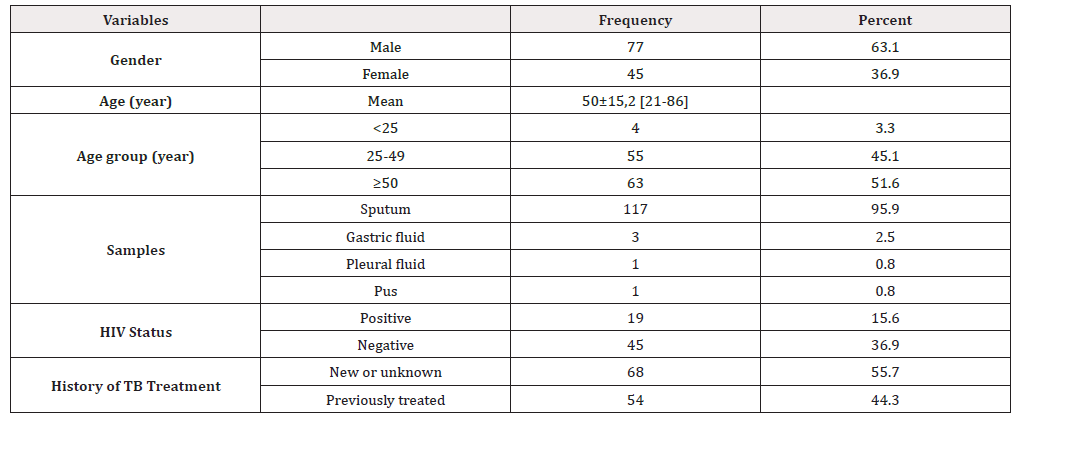
Table 2:Demographic and clinical variables of patients with NTM species.
Nested 16S PCR prior to sequencing was performed, for 151 of 155 patients included in study, from 80 clinical specimens and 71 colonies. The test was negative on 33 clinical samples and positive on 118 samples including 47 clinical samples and all 71 cultures (Table 3). Sequencing was performed on sample with clearly positive amplicons, characterizing a specie or a specie group for 95 or 80.5%. For 23 (19.5%), a specific species or specific group of NTM was not able to be characterized (Table 3).
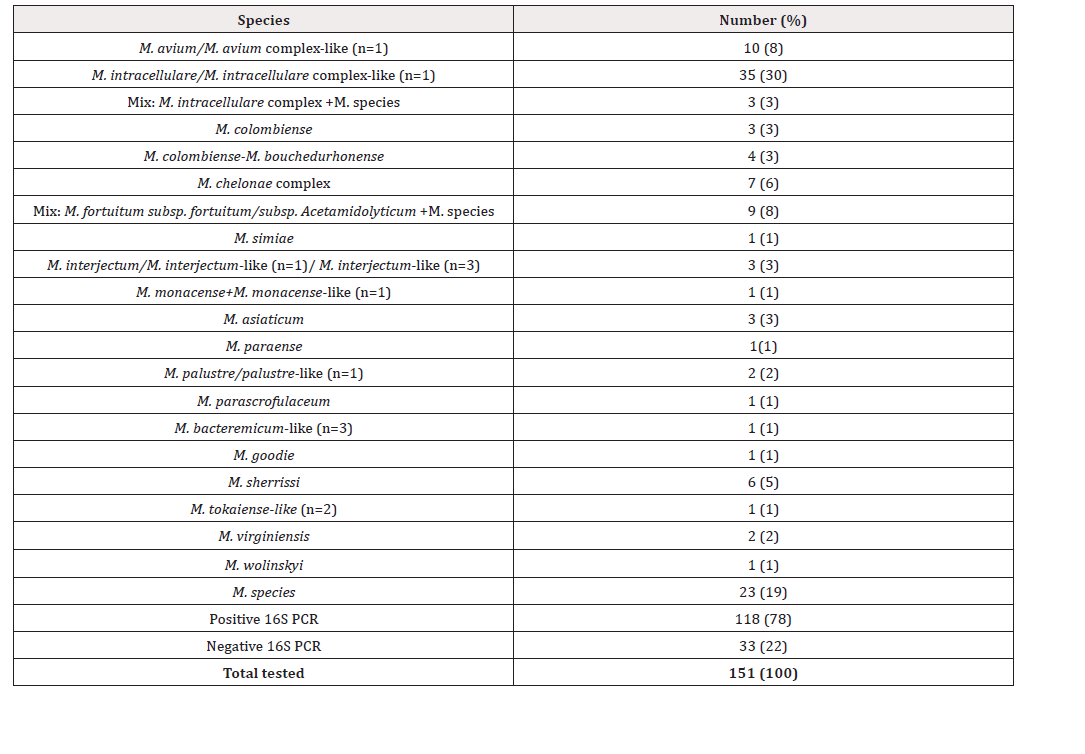
Table 3:NTM Species identified by sequencing.
Characterization of NTM Species by Line Probe Assay GenoType CM/AS
The LPA was performed on 51 strains and species were characterized for 43 (84.3%). The species could not be characterized for 8 patients (15.7%) (Figure 1). MAC was predominant with 25 cases (49%) including 4 species of M. avium and 21 M. intracellulare, respectively 8% and 41% (Figure 2).
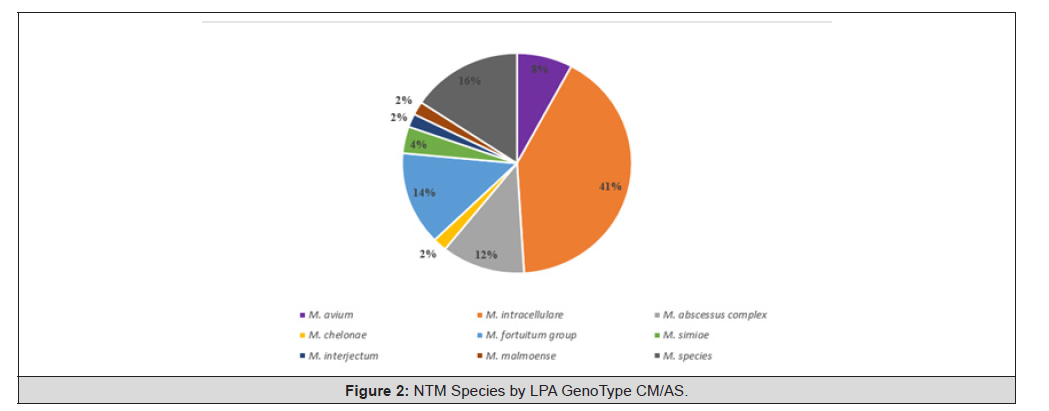
Figure 2:NTM Species by LPA GenoType CM/AS.
Comparison Between Sanger Sequencing and LPA
Among the 47 patients who benefited the 2 methods of identification, 32 results had similar patterns. Identification of species with the 2 methods was not possible for 3 patients. Six samples have shown some differences between 2 methods (Table 4), 4 samples (NTM-09-0130, NTM-21-0489, NTM-21-0962, NTM-21-1269), were M. chelonae by sequencing and M. abscessus by LPA CM. One sample (NTM-20-0908) was M. palustre-like by sequencing and M. malmoense by LPA and one (NTM-21-0499) was M. sherrisii by sequencing and M. simiae by LPA. The samples NTM-20-1973 and NTM-22-1804 were identified as M. colombiense by sequencing and M. intracellulare by hybridization (Table 4 & Figure 3).
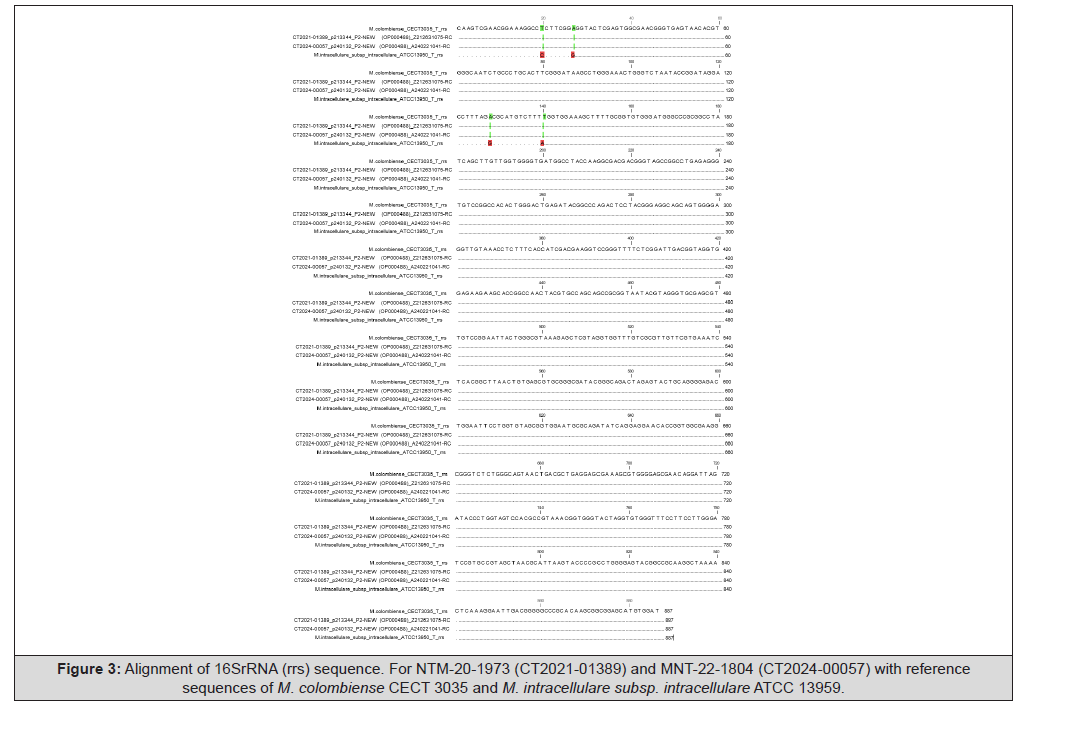
Figure 3:Alignment of 16SrRNA (rrs) sequence. For NTM-20-1973 (CT2021-01389) and MNT-22-1804 (CT2024-00057) with reference sequences of M. colombiense CECT 3035 and M. intracellulare subsp. intracellulare ATCC 13959.
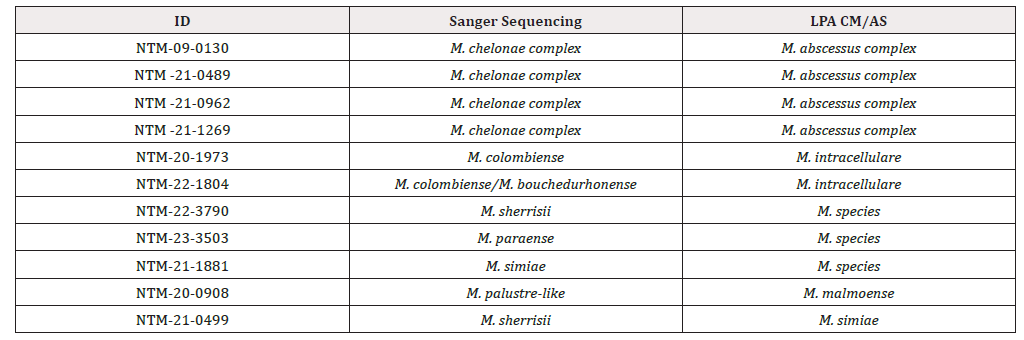
Table 4:Discordant results between LPA CM/AS and Sanger sequencing.
Note*: NTM=non-tuberculous mycobacteria.
Frequency of Species Identified by the 2 Methods of Identification
MAC was more frequent with 47% (57/122), followed by M. simiae 16 (13.1%), M. fortuitum 9 (7.4%) and M. abscessus 6 (4.9%) (Figure 4). The exact NTM species present could not be identified in 21 patients (17.2%) (Figure 4).
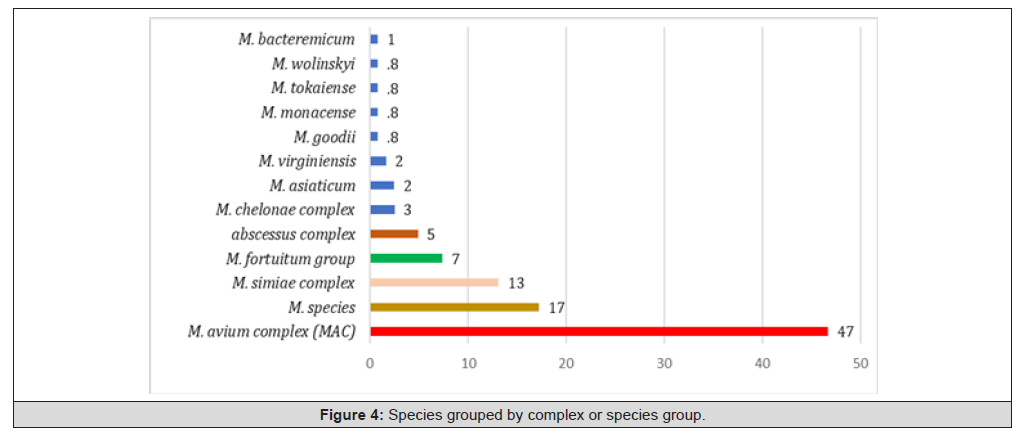
Figure 4:Species grouped by complex or species group.
Discussion
We characterized NTM species detected in our laboratory in patients referred from different health centres in the country. Male sex with 63.1% represented more than half of our patients which is similar to the world tuberculosis report that found 67% of men and 33% of women. (World Health Organization, 2024a). However, female patients were frequently represented with increasing age in several studies [20-22]. The mean age of patients in our study is similar to those reported in other studies [23-26]. The high percentage of clinical samples negative at nested PCR in our study can be explained by a loss of DNA during the multiple stages of sample processing, especially for samples with a low bacillary load. This loss of DNA has been previously reported in some studies [27,28]. The proportion of NTM detected in patients with positive microscopy and MTB not detected by Xpert in our study is slightly lower than that found in other studies [21,29] but higher than that reported in a study in Pakistan [30]. These differences could be explained by the bacillary load of the samples and the techniques used for detection.
Two samples classified as M. species by LPA were identified as M. sherrisii and M. paraense by sequencing. According to the literature, these species cannot be identified by LPA [18,19]. Differential identification of the two closely identic species absessus and chelonae, previously grouped together as M. chelonae-abscessus complex [31] was possible with LPA and not with Sanger sequencing [32,33]. Although this differentiation was possible using hybridization, confusion has been reported with this method [34]. The identification of the 2 species of NTM, M. colombiense by sequencing and M. intracellulare by hybridization in our study, could be explained by nucleotide substitutions in the 16S gene sequence compared with the reference strain ATCC 13950 of M. intracellular subs-intracellulare, and as the target gene for the hybridization test is the 23S gene, the M. colombiense species would not be identifiable. The identification of species such as M. malmoense by the hybridization test and M. palustre by sequencing can be explained by the sharing of the same bands by these 2 species for the GenoType CM kit. In fact, these 2 species are closely identical and are grouped together in the M. simiae complex [35]. In our study, MAC species were more frequent, as in other studies in Mali, Africa and elsewhere [8-16]. Species from M. simiae complex were the most detected after MAC species. Species of these 2 groups are recognized as pathogenic for humans [2].
Conclusion
Species of MAC were the most identified in our study. Molecular methods for TB diagnostic algorithms should also include methods for the detection of cases of NTM. Molecular platforms enabling differential detection of mycobacterial species, could be an opportunity for better management of tuberculosis and mycobacterial diseases.
Acknowledgement
None.
Conflict of Interest
None.
References
- Daley CL, Iaccarino JM, Lange C, Cambau E, Wallace RJ, et al. (2020) Treatment of nontuberculous mycobacterial pulmonary disease: An official ats/ers/escmid/idsa clinical practice guideline. Clin Infect Dis 71(4): e1-e36.
- Griffith DE, Aksamit T, Brown-Elliott BA, Catanzaro A, Daley C, et al. (2007) An official ATS/IDSA statement: Diagnosis, treatment, and prevention of nontuberculous mycobacterial diseases. Am J Respir Crit Care Med 175(4): 367-416.
- Cisse AB, Dean AS, Van Deun A, Keysers J, De Rijk W-B, et al. (2024) Prevalence of non-tuberculous mycobacteria among people with acid-fast positive presumptive tuberculosis in Mali. PLoS One. 19(12): e0301731.
- Hanifa Y, Fielding KL, Chihota VN, Adonis L, Charalambous S, et al. (2018) The utility of repeat Xpert MTB/RIF testing to diagnose tuberculosis in HIV-positive adults with initial negative result. Gates Open Res 2: 22.
- Singh K, Kumari R, Tripathi R, Gupta A, Anupurba S (2019) Mutation in MPT64 gene influencing diagnostic accuracy of SD Bioline assay (capilia). BMC Infect Dis. 19(1): 1048.
- Pascapurnama DN, Zavitri NG, Koesoemadinata RC, Cahyadi AI, Chaidir L (2023) Identification of Significant Pathogenic Nontuberculous Mycobacteria Species from Presumptive TB Patients Using Partial hsp65 Gene Sequencing. Infect Drug Resist 16: 6923-6930.
- Maiga M, Siddiqui S, Diallo S, Diarra B, Traoré B, et al. (2012) Failure to recognize nontuberculous mycobacteria leads to misdiagnosis of chronic pulmonary tuberculosis. PLoS One. 7(5): e36902.
- Aliyu G, El-Kamary SS, Abimiku A, Brown C, Tracy K, et al. (2013) Prevalence of Non-Tuberculous Mycobacterial Infections among Tuberculosis Suspects in Nigeria. PLoS One. 8(5): e63170.
- Agizew T, Basotli J, Alexander H, Boyd R, Letsibogo G, et al. (2017) Higher-than-expected prevalence of nontuberculous mycobacteria in HIV setting in Botswana: Implications for diagnostic algorithms using Xpert MTB/RIF assay. PLoS One 12(12): e0189981.
- Okoi C, Anderson STB, Antonio M, Mulwa SN, Gehre F, et al. (2017) Non-tuberculous Mycobacteria isolated from Pulmonary samples in sub-Saharan Africa - A Systematic Review and Meta Analyses. Sci Rep 7(1): 12002.
- Farnia P, Farnia P, Ghanavi J, Velayati AA (2019) Epidemiological Distribution of Nontuberculous Mycobacteria Using Geographical Information System. In: Nontuberculous Mycobacteria (NTM): Microbiological, Clinical and Geographical Distribution. 191-321.
- Yeong C, Byrne AL, Cho JG, Sintchenko V, Crighton T, et al. (2020) Use of GeneXpert MTB/RIF on a single pooled sputum specimen to exclude pulmonary tuberculosis among hospital inpatients placed in respiratory isolation. Int J Infect Dis 92: 175-180.
- Sun Q, Yan J, Liao X, Wang C, Jiang G, et al. (2022) Trends and Species Diversity of Non-tuberculous Mycobacteria Isolated from Respiratory Samples in Northern China, 2014-2021. Front Public Heal 10: 923968.
- Ochayo A, Wamalwa R, Barasa E, Zablon J, Sowayi G, et al. (2023) Prevalence of Non-Tuberculosis Mycobacterium Pulmonary Disease in HIV-1 Patients with Presumptive Pulmonary Tuberculosis in Western Kenya. Ethiop J Health Sci 33(5): 735-742.
- Ojo OT, Odeyemi AO (2023) Non-Mycobacteria Tuberculosis in Africa: A Literature Review. Ethiop j health sci 33(5): 913-918.
- Kone B, Sarro YS, Maiga M, Sanogo M, Somboro AM, et al. (2018) Clinical characteristics of non-tuberculous mycobacterial pulmonary infections in Bamako, Mali. Epidemiol Infect 146(3): 354-358.
- Fedrizzi T, Meehan CJ, Grottola A, Giacobazzi E, Fregni Serpini G, et al. (2017) Genomic characterization of Nontuberculous Mycobacteria. Sci Rep 7: 45258.
- (2016) Hain Lifescience. GenoType Mycobacterium CM VER 2.0 Instructions for Use. Germany.
- (2016) Hain Lifescience. GenoType Mycobacterium AS VER 1.0 Instructions for Use. Germany.
- Kennedy TP, Weber DJ (1994) Nontuberculous mycobacteria. An underappreciated cause of geriatric lung disease. Am J Respir Crit Care Med 149(6): 1654-1668.
- Kong L, Xie B, Liu Q, Hua L, Bhusal A, et al. (2021) Application of acid-fast staining combined with GeneXpert MTB/RIF in the diagnosis of non-tuberculous mycobacteria pulmonary disease. Int J Infect Dis 104: 711-717.
- Limo JJ, Nyerere A, Bii C (2016) Prevalence, Species Characterization and factors associated with Non tuberculous mycobacteria among tuberculosis retreatment patients submitting samples to the National Tuberculosis Reference Laboratory, Kenya. Vol. 7, Jomo Kenyatta University of Agriculture and Technology. 2016.
- Donkeng Donfack VF, Fokou TAZ, Wadje LEN, Le Grand Napa Tchuedji Y, Djieugoue YJ, et al. (2024) Profile of non-tuberculous mycobacteria amongst tuberculosis presumptive people in Cameroon. BMC Microbiol 24(1): 100.
- Kamau G, Mwangi Z, Bargul J, owiny M, Mukiri N, et al. (2023) Non-Tuberculous mycobacterium isolations from tuberculosis presumptive cases at the National Tuberculosis Reference Laboratory Kenya, 2018-2019. F1000 Research 12: 1104.
- Ndanga MED, Abdul JBPAA, Edoa JR, Ibinda GARM, Adegbite BR, et al. (2023) Species identification and drug susceptibility testing of non-tuberculous mycobacteria by Line Probe Assay in Lambaréné, Gabon-a cross-sectional study. BMC Infect Dis 23(1): 651.
- Varghese B, Memish Z, Abuljadayel N, Al-Hakeem R, Alrabiah F, et al. (2013) Emergence of Clinically Relevant Non-Tuberculous Mycobacterial Infections in Saudi Arabia. PLoS Negl Trop Dis 7(5): e2234.
- Fang Y, Wu WH, Pepper JL, Larsen JL, Marras SAE, et al. (2002) Comparison of real-time, quantitative PCR with molecular beacons to nested PCR and culture methods for detection of Mycobacterium avium subsp. paratuberculosis in bovine fecal samples. J Clin Microbiol 40(1): 287-291.
- Seo AN, Park HJ, Lee HS, Park JO, Chang HE, et al. (2014) Performance characteristics of nested polymerase chain reaction vs real-time polymerase chain reaction methods for detecting mycobacterium tuberculosis complex in paraffin-embedded human tissues. Am J Clin Pathol 142(3): 384-390.
- Mnyambwa NP, Ngadaya ES, Kimaro G, Kim DJ, Kazwala R, et al. (2017) Assessment of sputum smear-positive but culture-negative results among newly diagnosed pulmonary tuberculosis patients in Tanzania. Int J Gen Med 10: 199-205.
- Tahseen S, Qadeer E, Khanzada FM, Rizvi AH, Dean A, et al. (2016) Use of Xpert® MTB/RIF assay in the first national antituberculosis drug resistance survey in Pakistan. Int J Tuberc Lung Dis 20(4): 448-455.
- Yu X, Jiang W (2021) Mycobacterium colombiense and mycobacterium avium complex causing severe pneumonia in a patient with hiv identified by a novel molecular-based method. Infect Drug Resist 14: 11-16.
- Kusunoki S, Ezaki T (1992) Proposal of Mycobacterium peregrinum sp. nov., nom. rev., and elevation of Mycobacterium chelonae subsp. abscessus (Kubica et al.) to species status: Mycobacterium abscessus comb. nov. Int J Syst Bacteriol 42(2): 240-245.
- Church DL, Cerutti L, Gürtler A, Griener T, Zelazny A, et al. (2020) Performance and application of 16S rRNA gene cycle sequencing for routine identification of bacteria in the clinical microbiology laboratory. Clin Microbiol Rev 33(4): e00053-19
- Lee AS, Jelfs P, Sintchenko V, Gilbert GL (2009) Identification of non-tuberculous mycobacteria: Utility of the GenoType Mycobacterium CM/AS assay compared with HPLC and 16S rRNA gene sequencing. J Med Microbiol 58(7).
- Wetzstein N, Diricks M, Andres S, Kuhns M, Marschall L, et al. (2024) Genomic diversity and clinical relevance of Mycobacterium simiae. ERJ Open Res 10(2): 00773-2023.




 We use cookies to ensure you get the best experience on our website.